
Mental Health
Signs of Postpartum Depression in New Dads (And Why It’s So Easy to Miss)

The content on this website – including articles, event announcements, personal experiences, and recommendations – is for informational and educational purposes only and is not medical advice. Always consult a qualified healthcare professional before making any changes to your diet, exercise, supplements, sleep habits, or wellness routines, especially if you are pregnant, nursing, on medication, or have any medical condition.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Paternal postpartum depression is a clinical condition that requires professional assessment. If you recognise yourself or a loved one in this article, use it as a starting point for a conversation with a qualified healthcare professional — not as a conclusion.
When people talk about postpartum depression, the image that typically comes to mind is a new mother — tearful, overwhelmed, struggling to bond with her baby. What that picture leaves out entirely is the father sitting next to her who has barely spoken in three weeks, who snaps at the smallest inconvenience, and who wonders why he feels nothing when he holds his newborn.
Paternal postpartum depression is real, it is common, and it looks almost nothing like the maternal version most of us learned to recognize.
Research published in JAMA — a landmark meta-analysis by James Paulson and Sharnail Bazemore reviewing data from nearly 28,000 fathers — found that roughly 1 in 10 new fathers experiences significant depression in the first year after their baby is born. That rate is approximately twice the background depression rate for men in the general population. Among fathers whose partners are also experiencing postpartum depression, the number climbs to roughly 1 in 4.
Those are not small numbers. They represent millions of men every year who are struggling in silence — and whose struggles rarely get named, screened for, or treated.
Key Takeaways
- 1 in 10 new fathers develops postpartum depression in the first year after birth — roughly twice the background depression rate for men in the general population (Paulson & Bazemore, JAMA).
- If your partner has PPD, your risk rises to roughly 1 in 4. A partner’s postpartum depression is the single strongest predictor of paternal PPD.
- Paternal PPD does not look like maternal PPD. Fathers are more likely to show externalising symptoms — irritability, anger, emotional withdrawal, increased alcohol use, throwing themselves into work — rather than the sadness and tearfulness most people associate with depression.
- It is not a separate DSM-5 diagnosis. Clinically, it maps onto Major Depressive Disorder (MDD) or adjustment disorder — the same categories used for depression in any other context.
- Hormones play a role. Testosterone decreases in actively involved fathers, and some research links a sharper testosterone drop to greater depression risk.
- It almost always goes unrecognised. There are no universal screening guidelines for new fathers, the most common screening tool (the EPDS) was designed for women, and cultural expectations push men to stay silent.
- The impact extends to children. Untreated paternal PPD is independently associated with behavioural difficulties, language delays, and emotional dysregulation in early childhood.
- It is treatable. CBT, interpersonal therapy, and antidepressant medication all show effectiveness — the same approaches that work for other forms of depression work here too.
- Only 3.2% of new fathers with depression actually seek help. If you recognise these signs in yourself or your partner, naming it is the first step.
What Is Paternal Postpartum Depression?
Paternal postpartum depression (sometimes abbreviated PPPD) is not a separate, distinct diagnosis in the DSM-5-TR. Clinically, it maps onto Major Depressive Disorder (MDD) or, in milder cases, adjustment disorder — the same diagnostic categories used for anyone experiencing a significant depressive episode.
The “postpartum” part simply reflects timing: symptoms that emerge during a partner’s pregnancy or in the months following birth, tied to the enormous physical, emotional, relational, and financial disruption that becoming a parent creates.
That lack of a standalone DSM-5 category has real-world consequences. It means there are no universal screening guidelines for fathers at postnatal or pediatric visits, no standard protocol that asks new dads how they are actually doing, and no clinical consensus on exactly which assessment tool to use. Most existing screening instruments — including the widely used Edinburgh Postnatal Depression Scale (EPDS) — were originally designed and validated for mothers, and adapted versions for fathers are still making their way into routine practice.
Why It Looks Different in Dads
This is the piece most online articles miss entirely, and it is the most important thing to understand.
Depression in men and women frequently presents differently — and nowhere is that gap wider than in the postpartum period. Maternal postpartum depression tends toward internalizing symptoms: sadness, tearfulness, hopelessness, difficulty bonding, withdrawal into quietness. It fits the cultural image of depression well enough that it gets recognized.
Paternal postpartum depression tends toward externalizing symptoms: irritability, anger, restlessness, throwing oneself into work, increased alcohol or substance use, emotional detachment, and risky behaviors. These don’t look like depression to most people — including to the fathers experiencing them. They look like stress, like personality, like being a workaholic, like “that’s just how he handles things.”
According to research published in Frontiers in Psychology (2024), men may also underreport or mask depressive symptoms on standard self-report measures — meaning even when screened, paternal depression is likely being undercounted.
The clinical language for this distinction is useful: fathers are more likely to show externalizing presentations while mothers more commonly show internalizing presentations. Both are depression. Only one gets recognized as such.
Signs of Postpartum Depression in New Dads

The following signs, particularly when they cluster together or represent a clear change from the father’s usual baseline, warrant attention.
Irritability and Anger Out of Proportion
One of the most consistently reported signs. The baby crying becomes intolerable. A minor household disagreement escalates. A partner’s casual comment lands like a criticism. This isn’t a temper problem — it’s an emotional regulation problem driven by an underlying depressive state. In men, irritability is frequently the surface expression of the sadness that goes unreported.
Emotional Numbness or Detachment from the Baby
Many fathers with postpartum depression describe feeling “nothing” when they hold their newborn — no surge of love, no fierce protectiveness, no joy. They expected to feel overwhelmed with warmth. Instead, they feel like they are holding a stranger. This absence of expected feeling is deeply distressing and rarely talked about because admitting it feels like a confession of bad fatherhood.
This kind of detachment is not a reflection of character or love. It is a symptom, and it responds to treatment.
Withdrawing from the Family
Spending longer hours at work. More time in front of screens. Disappearing into hobbies, the garage, the gym — anywhere that isn’t the shared domestic space where the pressure concentrates. This withdrawal can look like avoidance of responsibility, but it often reflects an inability to tolerate the emotional overwhelm of the home environment when the nervous system is already at its limit.
Increased Alcohol or Substance Use
Self-medication is a common but often invisible coping strategy. A few beers each evening that gradually became six. Smoking more. Relying on cannabis to feel calm. These patterns frequently emerge in the postpartum period among fathers and rarely get connected to the depression driving them.
Physical Complaints Without a Clear Cause
Depression in men frequently manifests somatically. New fathers with PPPD commonly report persistent fatigue (beyond ordinary sleep deprivation), headaches, digestive problems, back and muscle tension, and a general physical flatness. When a man visits a doctor about these symptoms, the underlying depression may not come up at all.
Loss of Interest in Things That Used to Matter
The sport he followed obsessively, the music he played, the friends he kept up with — all of it feels distant and hollow. This anhedonia (the clinical term for loss of pleasure in previously enjoyable activities) is one of the core diagnostic criteria for MDD, and it’s just as present in paternal depression as in any other form.
Sleep Problems Unrelated to Infant Waking
Sleep deprivation with a newborn is universal. But fathers with PPPD often describe an inability to sleep even when the baby is not waking them — lying awake with looping, anxious thoughts, or waking hours too early with a sense of dread. This goes beyond ordinary new-parent exhaustion and reflects a disrupted sleep architecture characteristic of clinical depression.
Anxiety, Hypervigilance, or Obsessive Worry
Some fathers experience the postpartum period primarily through anxiety: constant catastrophizing about the baby’s health, obsessive checking behaviors, terror about something going wrong, or a vague, unshakeable sense of impending disaster. This anxious presentation often co-occurs with depression and is frequently missed because it reads as “concerned parenting” rather than a clinical anxiety-depression picture.
Relationship Conflict and Emotional Distance from Partner
PPPD consistently correlates with increased marital stress. The father pulls away emotionally. Arguments become more frequent or more intense. Intimacy disappears — not just physically but in the small moments of connection that hold relationships together. Partners often describe feeling like they are parenting alone even when he is physically present.
The Hormonal Piece
Postpartum hormonal shifts are not only a maternal story. Research shows that testosterone levels decrease in actively involved fathers, particularly those who take on hands-on caregiving. While this hormonal shift appears to support pair bonding and parental investment, some studies — including work published in Frontiers in Psychology — suggest that men who experience a sharper testosterone drop may be more vulnerable to depressive symptoms.
Oxytocin, the bonding hormone, also changes in new fathers, and how those changes unfold appears to interact with depression risk. The hormonal picture in paternal postpartum depression is still being mapped — but the idea that fathers are biologically unaffected by the arrival of a new baby is simply wrong.
Risk Factors: Who Is Most Vulnerable
No single risk factor predicts paternal postpartum depression, but several raise the probability significantly.
Partner’s postpartum depression is the strongest predictor in the research literature. A father whose partner is experiencing PPD has roughly a 50% chance of developing depression himself — more than twice the baseline risk. This bidirectional relationship means that failing to identify and treat PPPD in either parent puts both at greater risk.
Other well-established risk factors include:
- Prior history of depression or anxiety — the strongest individual-level predictor
- Sleep deprivation — not just from infant care but disrupted, non-restorative sleep
- Financial stress — the economic pressure of a growing family, particularly if income has changed
- Relationship conflict — poor partner communication before or during the postpartum period
- Feeling excluded from the infant-mother bond — a specific and underacknowledged source of distress for fathers
- Lack of social support — social isolation amplifies all other risk factors
- Unplanned or complicated pregnancy — additional stressors during the perinatal period
- Limited involvement in infant care — counterintuitively, fathers with less hands-on engagement may lose a key buffer against depression
Why It Goes Unrecognized
The gap between how many fathers experience postpartum depression and how few receive help is striking. Research cited in Psychology Today found that only about 3.2% of new fathers actually use mental health services in the postpartum period — a number that reflects systemic failures, not a low prevalence.
Several forces converge to keep paternal PPD invisible:
Cultural scripts about fatherhood and masculinity. Men are expected to be steady, functional, and supportive — the strong one when the mother is struggling. Admitting depression can feel like a betrayal of that role. Many fathers describe feeling they have “no right” to their distress when it is the mother who just went through pregnancy and birth.
Symptom mismatch. The cultural image of depression — sadness, crying, visible suffering — does not match the irritability, numbness, and withdrawal that characterize PPPD. Many fathers genuinely do not recognize their experience as depression.
No formal screening. Mothers receive Edinburgh Postnatal Depression Scale screening at obstetric and pediatric visits. Fathers are rarely in those rooms, and when they are, the screening almost never extends to them.
The baby’s needs absorb all attention. In the blur of early parenthood, everyone — including the father himself — tends to focus on the infant and the mother. A father who is quietly struggling often remains invisible until the family is in crisis.
The Impact on Children
Paternal postpartum depression is not only a father’s problem. Research consistently shows that PPPD affects children’s outcomes independently of maternal PPD. Fathers with untreated depression show less warm, responsive, and engaged parenting — and early paternal engagement is a significant predictor of cognitive and emotional development. Children whose fathers experienced postpartum depression show elevated rates of behavioral problems, language delays, and emotional dysregulation in early childhood.
This is not about blame. It is about the stakes — and about why identifying and treating PPPD matters for the whole family.
When to Seek Help

If you recognize several of these signs in yourself — or in your partner — treat it the same way you would treat any other medical concern: with directness, without waiting for a crisis.
If symptoms have persisted for two weeks or more, if they are getting in the way of work, relationships, or daily function, or if you are having thoughts of harming yourself or someone else, those are clear signals to reach out now. A GP or primary care physician is a reasonable first contact; they can screen formally, rule out any physical contributors (thyroid function, for instance), and make a referral to a mental health professional.
Paternal postpartum depression responds well to the same treatments that work for other forms of depression: cognitive behavioral therapy (CBT), interpersonal therapy (IPT), and in some cases antidepressant medication. Peer support groups — including those specifically for new fathers — also show promising outcomes, particularly because they work around the barrier of one-to-one clinical settings that many men avoid.
A father who recognizes himself in any of the signs above and finds himself wondering if this is more than ordinary stress might find it useful to read about high-functioning depression — the form of depression that allows a person to appear fully operational while privately struggling — because that masked quality is precisely how paternal PPD often presents.
If the picture feels more acute — if it has crossed from persistent low mood into something that feels like a breaking point — the post on signs of a nervous breakdown covers the specific threshold markers that should prompt immediate professional contact.
And if the dominant experience is less about mood and more about total depletion — running on nothing, unable to recover no matter how much you sleep — it may be worth reading about emotional exhaustion vs. burnout to understand whether what you’re experiencing is burnout layered on top of depression, which is common in the postpartum period.
Frequently Asked Questions
How long does paternal postpartum depression last?
Without treatment, paternal postpartum depression can persist for months or even years. Research suggests symptoms often peak between three and six months after birth, but untreated depression does not reliably resolve on its own. With appropriate treatment — therapy, medication, or a combination — most men see significant improvement within weeks to months.
Can fathers get postpartum depression even if they weren’t present at the birth?
Yes. Paternal postpartum depression is driven by the cumulative stress, sleep deprivation, relational disruption, hormonal changes, and identity upheaval of new parenthood — not by the birth experience itself. Fathers who were absent at birth, adoptive fathers, and fathers in same-sex partnerships where no partner was pregnant have all been documented to experience postpartum depression.
What is the difference between paternal postpartum depression and baby blues in dads?
Baby blues — a brief period of tearfulness, emotional reactivity, and mood fluctuation in the first week or two after birth — are common in both mothers and fathers and typically resolve on their own within two weeks. Paternal postpartum depression is distinguished by duration (two weeks or more), functional impairment, and the cluster of clinical symptoms described above. If the low mood, irritability, or withdrawal persists past the two-week mark and is affecting daily life, that is no longer baby blues.
Is there a screening test for paternal postpartum depression?
The Edinburgh Postnatal Depression Scale (EPDS), originally designed for mothers, is the most widely used tool and has adapted versions validated for use with fathers. Some researchers advocate for the Paternal Postnatal Depression Questionnaire (PPDQ) or the Beck Depression Inventory (BDI-II) as complementary tools. However, no universal, standardized screening protocol currently exists for fathers in most clinical settings — which is one of the main reasons PPPD goes undetected.
Does paternal postpartum depression affect the baby?
Research consistently shows that untreated paternal postpartum depression affects children’s development independently of maternal PPD. Children of depressed fathers show elevated rates of behavioral difficulties, language delays, and emotional regulation problems in early childhood. Early identification and treatment of PPPD protects not only the father’s wellbeing but the long-term outcomes of the whole family.
The Bottom Line
Postpartum depression does not check whether you are the parent who gave birth. It affects roughly 1 in 10 new fathers — showing up not as the sadness and crying that most people picture, but as irritability, emotional numbness, withdrawal, and a quiet inability to feel the joy that everyone else seems to be expecting.
The silence around paternal postpartum depression costs families enormously. It costs fathers their wellbeing, partners their support, and children a present, engaged dad during a period of development that shapes them for life.
If this sounds like something you — or someone you know — might be going through, the most useful next step is also the simplest one: name it, without minimizing it, and talk to someone. The same clinical tools that treat depression in every other context work here too. You don’t have to wait until it gets worse.
Sources:
- Paulson JF, Bazemore SD. Prenatal and postpartum depression in fathers and its association with maternal depression: a meta-analysis. JAMA. 2010;303(19):1961–1969. https://jamanetwork.com/journals/jama/fullarticle/185844
- Kotov A, Corpuz M. Paternal postpartum depression: risk factors and relationship to maternal postpartum depression. Frontiers in Psychology. 2024;15:1348031. https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2024.1348031/full
- National Institutes of Health / PMC. Paternal perinatal depression — PMC11453120. https://pmc.ncbi.nlm.nih.gov/articles/PMC11453120/
- Anderson S. Can Fathers Suffer From Postpartum Depression? Psychology Today. April 2024. https://www.psychologytoday.com/ca/blog/preparing-for-parenthood/202404/can-fathers-suffer-from-postpartum-depression
- American Psychological Association. Paternal postpartum depression. https://www.apa.org/monitor/2019/07-08/paternal-depression
- National Institute of Mental Health (NIMH). Depression. https://www.nimh.nih.gov/health/topics/depression
- Postpartum Depression. org. Depression in New Fathers. https://www.postpartumdepression.org/postpartum-depression/depression-in-fathers/














Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you are experiencing unexplained or severe physical symptoms, please consult a qualified healthcare professional to rule out other conditions.
The headache that won’t lift. The knot in your stomach before a difficult conversation. The way your heart races when your inbox fills up. These aren’t coincidences — and they’re not weakness. They are the predictable, well-documented result of biological systems doing exactly what they were designed to do, just in a context those systems weren’t designed for.
According to the American Psychological Association’s research on stress and the body, stress affects every major organ system — cardiovascular, respiratory, musculoskeletal, gastrointestinal, endocrine, reproductive, and immune. The APA reports that approximately 75% of Americans experience physical or emotional symptoms they associate with stress. Gallup’s 2023 Global Emotions Report puts daily significant stress at around 49% of US adults.
These are not trivial numbers. And the symptoms they produce are not trivial either.
This article covers what stress and anxiety actually do to your body, system by system, with the physiological mechanisms explained — because understanding why something is happening is often the first step toward addressing it.
The Two-System Response: What’s Actually Happening
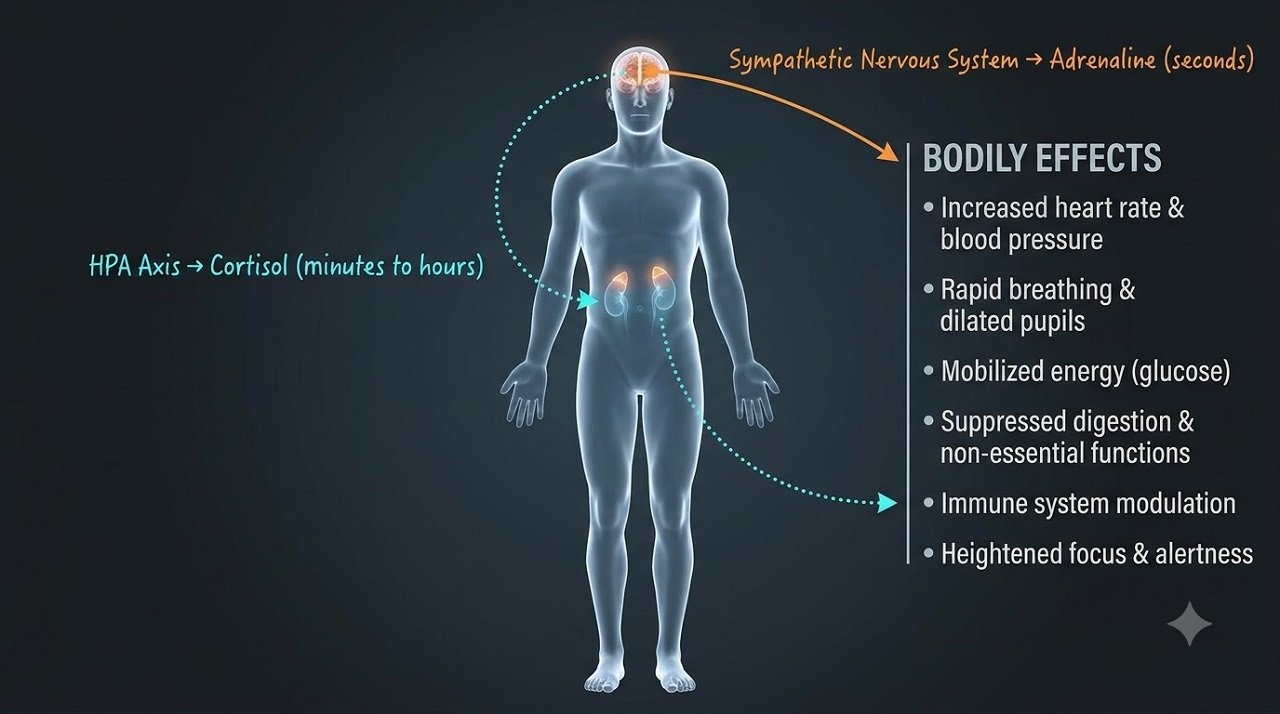
Before diving into symptoms by body system, it helps to understand the two biological systems driving them.
The sympathetic nervous system (SNS) — the fast response. When you perceive a threat — a deadline, a confrontation, a frightening piece of news — your brain’s amygdala fires an alarm signal. Your hypothalamus activates the sympathetic nervous system within milliseconds, flooding your body with adrenaline (epinephrine) and noradrenaline. Heart rate accelerates. Blood is diverted away from non-essential systems (digestion, reproduction, immune activity) toward the muscles and lungs. Your pupils dilate. Your liver dumps glucose into your bloodstream. This is the fight-or-flight response, and it is fast, powerful, and non-discriminating — it cannot tell the difference between a tiger and an unread email.
The HPA axis — the sustained response. Seconds later, the hypothalamic-pituitary-adrenal (HPA) axis activates. Your hypothalamus signals the pituitary gland, which signals the adrenal glands to release cortisol — the primary stress hormone. Unlike adrenaline, which spikes and fades, cortisol lingers. Its job is to sustain the stress response and mobilise energy over a longer period. According to the APA, cortisol normally drops once the stressor resolves. In chronic stress, it does not — and this sustained cortisol elevation is where most of the long-term physical damage originates.
Anxiety operates through the same systems. The difference is that anxiety is often triggered by perceived or anticipated threats rather than immediate ones — which means the stress response can fire repeatedly in the absence of a concrete danger, and the body pays the same physiological price regardless.
Cardiovascular System: Heart, Blood Pressure, Circulation

Acute response: During the immediate stress response, your heart beats faster and harder. Blood pressure rises. Blood is redirected to large muscles to support physical action.
Chronic impact: When the stress response activates frequently and stays activated, the cardiovascular system bears a disproportionate share of the cost. According to the APA, chronic stress is associated with higher risk of hypertension, inflammation in the coronary arteries, heart attack, and stroke. The mechanism involves sustained SNS activation increasing arterial pressure, while elevated cortisol promotes inflammatory processes that can contribute to arterial plaque.
Anxiety adds another layer. The palpitations, racing heart, and chest tightness that accompany acute anxiety — which are covered in detail in our article on what an anxiety attack feels like physically — activate the same cardiovascular pathways. When anxiety is persistent, those pathways stay activated.
What you may notice:
- Racing or irregular heartbeat (palpitations)
- Chest tightness or pressure
- A pounding sensation in the chest, neck, or temples
- Elevated resting heart rate
- Cold hands and feet (blood diverted from extremities)
- Elevated blood pressure readings
Musculoskeletal System: Tension, Pain, Headaches
Muscle tension is one of the most immediate and universal physical responses to stress. According to the APA, the body’s protective reflex under threat is to tighten muscles — a preparation for impact or physical action. In a genuinely physical emergency, this makes sense. Sustained under chronic stress, it produces a state of near-constant guarding that most people don’t consciously register until it produces pain.
The APA notes that job-related stress in particular is linked to tension-type headaches and low back and upper limb pain. The pathway is direct: sustained contraction of the neck, scalp, and shoulder muscles restricts blood flow and irritates surrounding tissue, producing the characteristic band-like pressure of a tension headache. Jaw clenching and teeth grinding (bruxism) — often occurring unconsciously during sleep — are closely associated with chronic stress and anxiety and can cause jaw pain, dental damage, and morning headaches.
What you may notice:
- Tension headaches — a band of pressure across the forehead or around the skull
- Neck and shoulder stiffness or aching
- Jaw soreness, especially in the morning
- Upper or lower back pain without a clear physical cause
- A general feeling of physical heaviness or fatigue
Respiratory System: Breathing, Chest, Asthma
Stress and anxiety constrict the airways. According to the APA, this constriction can cause shortness of breath and rapid breathing, and can trigger or worsen asthma and COPD in people who have those conditions.
For people with anxiety specifically, respiratory symptoms are a core physical feature — and they operate in a loop. Rapid shallow breathing (hyperventilation) reduces carbon dioxide levels in the blood, which produces tingling, dizziness, and a sense of unreality. This heightened bodily awareness then feeds back into anxiety, intensifying the breath-focused symptoms. The APA notes that stress-driven hyperventilation can trigger panic attacks in people who are prone to them.
What you may notice:
- Shortness of breath at rest or with mild exertion
- A feeling of not being able to get a full breath
- Rapid, shallow breathing
- Chest tightness
- Sighing frequently
- Dizziness or light-headedness
- Tingling in the hands, feet, or face
Gastrointestinal System: The Gut-Brain Axis

This is the body system where stress and anxiety produce the broadest range of symptoms — and the one where the physiological mechanism is most underappreciated.
The gut contains more nerve endings than the spinal cord and is sometimes called the “second brain” because of its dense neural network (the enteric nervous system). The gut and brain are in continuous, bidirectional communication via the vagus nerve — a direct highway connecting the two. This connection is why anxiety produces stomach symptoms before a presentation, and why gastrointestinal disease often worsens mental health.
According to the APA, stress can intensify pain, bloating, and nausea; change appetite; worsen heartburn and acid reflux; cause diarrhoea or constipation; produce bowel spasms; and weaken the intestinal barrier. The APA explicitly notes that stress does not cause stomach ulcers — those are caused by bacterial infection — but it can make ulcers more painful and harder to heal.
Irritable bowel syndrome (IBS) is particularly closely linked to stress and anxiety. Research in Nutrients and multiple PMC reviews confirms that the HPA axis dysregulation seen in chronic stress directly disrupts gut motility, alters the gut microbiome, and increases intestinal permeability — all of which can trigger or worsen IBS symptoms. The University of Michigan’s Digestive Health program notes that the gut-brain connection is bidirectional: stress worsens gut symptoms, and gut symptoms in turn worsen stress and anxiety.
What you may notice:
- Nausea or stomach cramps before or during stressful events
- Appetite changes — eating much more or much less than usual
- Constipation, diarrhoea, or alternating patterns
- Heartburn or acid reflux flares
- Bloating or gas
- IBS flares with no obvious dietary trigger
Immune System: Illness, Inflammation, Slow Healing
Cortisol is both an anti-inflammatory and an immune suppressant. In the short term, this is adaptive — it prevents the immune system from over-responding to the immediate stressor. Over the long term, chronically elevated cortisol impairs the immune system’s ability to respond normally to threats.
According to the APA, impaired HPA axis communication — a hallmark of chronic stress — has been linked to more frequent illness, chronic fatigue, metabolic disorders including diabetes and obesity, and immune disorders. Research published in JAMA Psychiatry found that prolonged high stress doubled the likelihood of developing metabolic syndrome. The cumulative biological cost of chronic stress on the body’s regulatory systems is sometimes described as allostatic load — a concept developed by neuroscientist Bruce McEwen at Rockefeller University to quantify the wear and tear chronic stress places on the body’s regulatory systems.
Wound healing is also impaired under stress. The PMC review published in 2026 on stress and skin conditions found that stress reduces collagen production and delays tissue repair, and that preoperative fear and anxiety are associated with impaired wound recovery.
What you may notice:
- Getting sick more often — colds, infections, minor illnesses
- Taking longer to recover from illness
- Feeling run-down even when not actively unwell
- Slow healing of minor cuts or skin irritation
- Chronic low-grade inflammation
Skin: The Visible Signal of Internal Stress
Skin is one of the most responsive organs to stress, because it has its own local HPA-like system that mirrors the systemic stress response. The 2026 PMC narrative review on psychological stress and skin conditions confirms that the HPA axis elevation seen under stress increases cortisol at both systemic and local levels, which reduces skin hydration, impairs the skin barrier, promotes inflammatory skin responses, and raises ACTH — which increases melanin production and can cause hyperpigmentation.
Specific dermatological conditions strongly linked to stress include psoriasis, atopic dermatitis (eczema), acne, alopecia areata (patchy hair loss), urticaria (hives), and seborrheic dermatitis. The review also documents a separate mechanism — catecholamines and neuropeptides released by nerve fibres near the skin triggering mast cell activation and neurogenic inflammation, which drives itch, redness, and barrier changes.
Telogen effluvium — diffuse hair shedding typically occurring two to three months after an acute stressor — is also well documented. It is caused by the stress response prematurely pushing hair follicles from the growth phase into the resting phase.
What you may notice:
- Acne flares not obviously linked to diet or hormones
- Eczema or psoriasis worsening during stressful periods
- Hives or unexplained skin redness
- Increased skin sensitivity
- Hair thinning or shedding two to three months after an intense stressor
- Slow healing of skin conditions
Sleep: Cortisol’s Most Disruptive Effect

Cortisol and sleep are on opposite schedules in a healthy system. Cortisol peaks in the morning to prepare you for the day and falls through the evening to allow sleep to occur. Chronic stress disrupts this rhythm — keeping cortisol elevated into the evening, which delays sleep onset, reduces deep sleep, and can cause early-morning waking (the body’s misread attempt to mobilise for a day that hasn’t started).
According to Henry Ford Health’s 2026 overview of stress and the body, trouble sleeping is one of the most common chronic stress symptoms, alongside headaches, digestive problems, high blood pressure, and hives.
Anxiety adds its own sleep disruption: racing thoughts, physical tension, and hypervigilance around sleep itself (the anxious monitoring of whether sleep is coming) can create a feedback loop where anxiety causes poor sleep, and poor sleep worsens anxiety.
What you may notice:
- Difficulty falling asleep despite feeling tired
- Waking in the early hours and being unable to return to sleep
- Unrefreshing sleep — waking more tired than when you went to bed
- Vivid or disturbing dreams
- Racing thoughts at bedtime
Endocrine and Metabolic System: The Long-Term Cost
The HPA axis is the body’s central stress management system, but it does not operate in isolation. Prolonged HPA activation disrupts blood sugar regulation (cortisol raises blood glucose to fuel the fight-or-flight response), thyroid function, and the balance of reproductive hormones.
The APA notes that chronic HPA dysregulation has been linked to metabolic disorders including type 2 diabetes and obesity — consistent with the JAMA Psychiatry finding that prolonged high stress doubled the likelihood of metabolic syndrome. The mechanism involves sustained cortisol elevation promoting insulin resistance and visceral fat accumulation over time.
Reproductive System
In men: According to the APA, chronic stress can reduce testosterone production, lowering libido and potentially causing erectile dysfunction. One cited study found that men who experienced two or more stressful life events in the past year had lower sperm motility and a lower percentage of normal-morphology sperm than men who had not.
In women: The APA reports that stress may cause absent or irregular menstrual cycles, more painful periods, and changes in cycle length. It can reduce sexual desire, affect fertility, and worsen premenstrual symptoms and menopausal hot flashes. Conditions such as PCOS may also be worsened by chronic stress-related hormonal dysregulation.
The Anxiety Symptom Loop
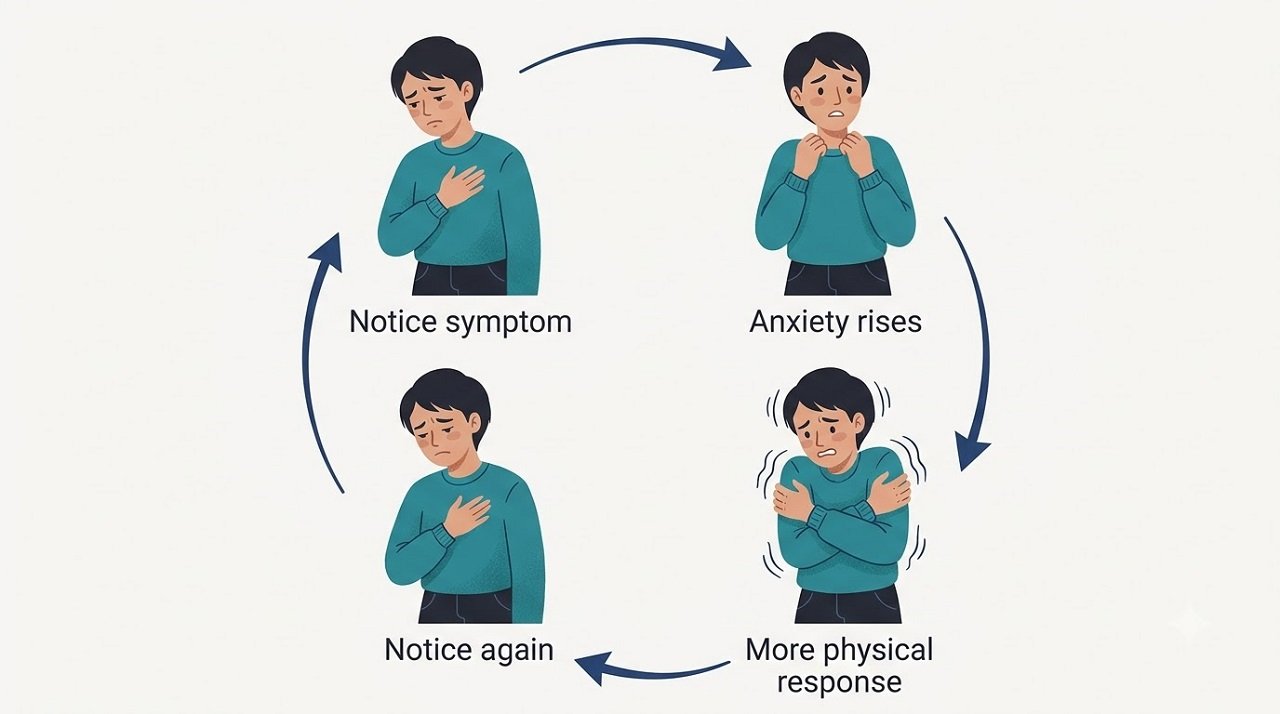
One feature of anxiety-related physical symptoms that sets them apart from stress symptoms is a feedback mechanism — sometimes called interoceptive amplification — where the physical symptom itself becomes a new source of anxiety.
You notice your heart beating harder. That noticing activates the threat-detection system, which increases the heart rate further. You notice the increased heart rate, which increases anxiety, which increases heart rate. The same loop can run with breathing, with dizziness, with gut symptoms. This is why anxiety physical symptoms can feel as though they escalate from nowhere — because the body’s own monitoring of its symptoms becomes the stressor.
Understanding this loop is important because it changes the intervention. Trying to suppress the symptom directly often makes the loop worse. Evidence-based approaches to anxiety — particularly CBT and exposure-based therapy — work in part by reducing the threat value of the bodily sensation rather than eliminating the sensation itself.
This connection between physical stress symptoms and trauma responses is also worth understanding. The fight/flight/freeze physiology that underlies trauma responses uses the same HPA and ANS pathways, and the physical symptoms can be nearly identical.
When Physical Stress Symptoms Become Chronic: Allostatic Load
Most stress responses are designed to be temporary. The body activates, the stressor resolves, and the system returns to baseline. The problem in modern life is that many stressors — work pressure, financial strain, relationship conflict, ongoing health concerns — do not resolve quickly. The stress response activates repeatedly, and the recovery periods become shorter.
This accumulation of physiological wear is what neuroscientist Bruce McEwen called allostatic load — the cumulative cost on the body’s regulatory systems from repeated or chronic stress. High allostatic load is associated with earlier onset of cardiovascular disease, metabolic disorders, immune dysfunction, and cognitive decline.
Our article on what emotional exhaustion and burnout actually are covers how this chronic activation plays out in the context of sustained life demands — it is worth reading alongside this one.
When to See a Doctor

Most physical symptoms of stress and anxiety are real — not imagined, not invented, not “just in your head” — and many resolve or significantly improve when the underlying stress is addressed. However, because stress and anxiety symptoms overlap with symptoms of conditions that need medical attention, certain presentations warrant a medical evaluation:
- Chest pain, particularly with shortness of breath, pain radiating to the arm or jaw, or sweating — these require urgent evaluation to rule out cardiac causes
- Heart palpitations that are irregular, sustained, or accompanied by dizziness or fainting
- Unexplained weight loss alongside other symptoms
- GI symptoms that are new, persistent, include blood, or cause significant weight loss
- Skin changes that don’t improve or appear to be worsening
- Severe or new headache unlike previous headaches
- Neurological symptoms — persistent numbness, vision changes, weakness in a limb
A GP or healthcare provider can assess whether symptoms are stress-related or require further investigation, and can also refer to mental health support if appropriate.
Frequently Asked Questions
Can stress and anxiety cause real physical symptoms?
Yes — completely. Physical symptoms of stress and anxiety have well-documented physiological mechanisms. They are produced by the same nervous system and hormonal pathways (HPA axis, sympathetic nervous system, cortisol) that evolved to handle physical threats. According to the APA, stress affects every major organ system in the body — cardiovascular, respiratory, gastrointestinal, musculoskeletal, endocrine, immune, and reproductive.
What are the most common physical symptoms of stress?
According to the APA and clinical literature, the most commonly reported physical symptoms of stress include headaches (particularly tension headaches), muscle tension (especially neck and shoulders), fatigue, GI problems (nausea, stomach aches, changes in bowel habits), sleep disturbance, and cardiovascular symptoms including elevated heart rate and blood pressure. Skin conditions including acne and eczema flares are also well documented.
Why does stress cause stomach problems?
The gut and brain are connected by the vagus nerve through the gut-brain axis. The gut contains its own dense neural network (the enteric nervous system), and stress activates the HPA axis, which directly disrupts gut motility, alters the intestinal barrier, and changes gut microbiome composition. The result is GI symptoms including nausea, cramping, bloating, diarrhoea, or constipation — even without any gastrointestinal disease present.
Can stress cause hair loss?
Yes. Telogen effluvium — diffuse hair shedding — is a well-documented response to significant acute stress. It occurs because stress hormones push hair follicles prematurely from the growth (anagen) phase into the resting (telogen) phase. The shedding typically appears two to three months after the stressful event, which is why the connection is often not made. In most cases, once the stressor resolves and is managed, hair regrowth follows.
How do I know if my physical symptoms are from stress or something else?
Physical symptoms that appear or worsen during stressful periods and improve when stress reduces are likely stress-related. However, because stress symptoms overlap with symptoms of several conditions requiring medical attention (heart disease, thyroid disorders, GI conditions, etc.), symptoms that are new, severe, persistent, or accompanied by red flags like chest pain with shortness of breath, unexplained weight loss, or blood in stool warrant medical evaluation. A GP can help determine the cause and, if appropriate, refer to mental health support alongside any medical treatment.
Sources & References
- American Psychological Association. “Stress Effects on the Body.” APA Help Center. apa.org/topics/stress/body
- Henry Ford Health. “How Stress Shows Up in the Body.” July 2026. henryford.com/blog/2026/07/how-stress-shows-up-in-the-body
- American Institute of Stress / Gallup. “What the Latest Reports Say About Stress in America.” Stress.org. stress.org/news/what-the-latest-reports-say-about-stress-in-america
- Gallup. 2023 Global Emotions Report. gallup.com/analytics/349280/gallup-global-emotions-report.aspx
- JAMA Psychiatry. “Prolonged High Stress and Metabolic Syndrome Risk.” 2022. jamanetwork.com/journals/jamapsychiatry
- Teo JX, et al. “Psychological Stress and Skin Conditions: A Comprehensive Narrative Review.” PMC, 2026. pmc.ncbi.nlm.nih.gov/articles/PMC12681996
- University of Michigan Digestive Health. “Gut-Brain Axis and IBS.” med.umich.edu/pdf/digestive/Gut-Brain-Axis-and-IBS.pdf
- National Institute of Mental Health (NIMH). “I’m So Stressed Out! Fact Sheet.” nimh.nih.gov/health/publications/so-stressed-out-fact-sheet
- McEwen BS. “Allostasis and Allostatic Load: Implications for Neuropsychopharmacology.” Neuropsychopharmacology, 2000. Rockefeller University. doi.org/10.1016/S0893-133X(99)00129-3
- Orlando Health. “Five Health Risks of Stress.” orlandohealth.com/content-hub/five-health-risks-of-stress
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to replace consultation with a qualified healthcare or mental health professional. If you are experiencing physical symptoms that concern you, please speak with a doctor.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you or someone you know is experiencing a mental health crisis, please contact a qualified healthcare professional or a crisis helpline immediately.
“Nervous breakdown” is one of the most searched mental health terms on the internet — and one of the least clearly defined. Women search it more than men, at a rate consistent with the fact that women are significantly more vulnerable to the conditions it describes. But what most search results offer in response is a symptom list without a clinical anchor. That isn’t enough — because the right response to what people call a nervous breakdown depends entirely on what is actually happening underneath.
This post provides both: a clear explanation of what a nervous breakdown actually is clinically, and a detailed, research-grounded account of how it presents specifically in women — including the hormonal, social, and biological factors that make women disproportionately vulnerable to reaching the point of crisis.
What Is a Nervous Breakdown? The Clinical Reality
A nervous breakdown is not a clinical diagnosis. It does not appear in the DSM-5, the APA’s Diagnostic and Statistical Manual of Mental Disorders, or in the ICD-11, the WHO’s International Classification of Diseases. There is no diagnostic code for it, no formal clinical criteria, and no agreed medical definition.
What the term describes — colloquially but accurately — is a point at which a person’s psychological resources have been depleted to the degree that they can no longer function normally. They stop being able to manage daily responsibilities: work, parenting, relationships, basic self-care. The internal experience feels like a total collapse.
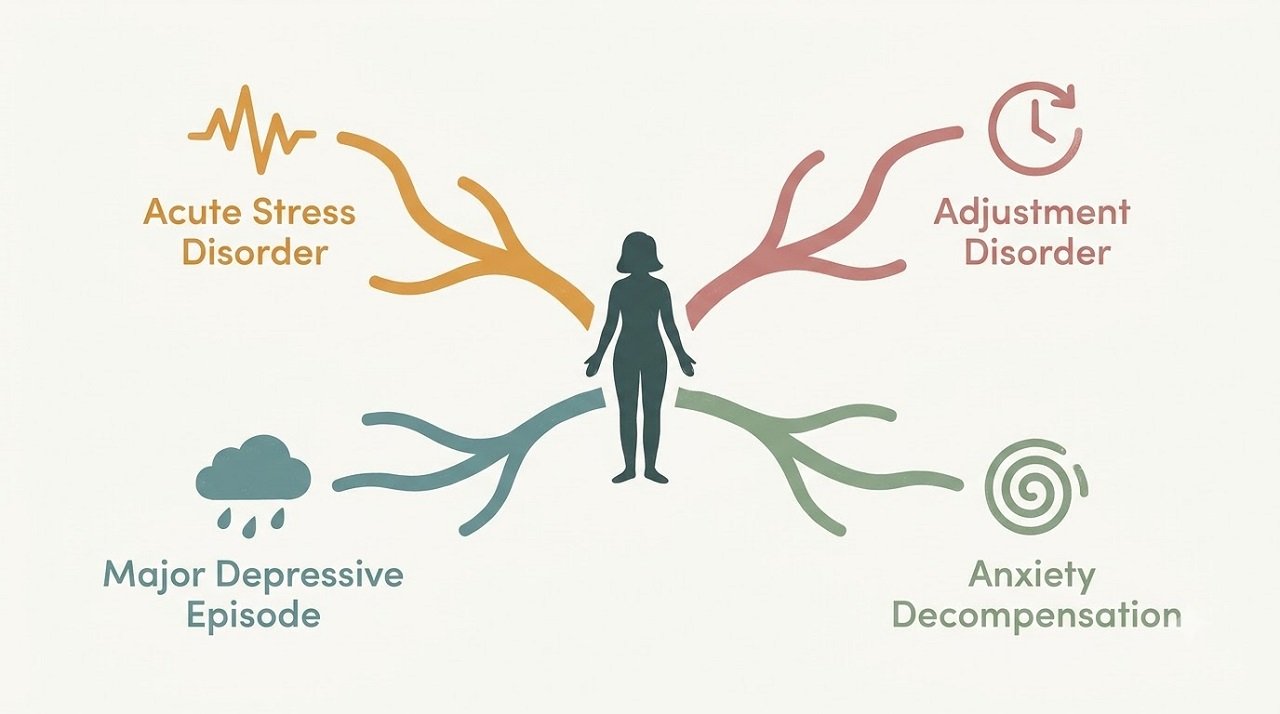
Clinically, what people are describing when they use this term maps onto one or more of the following formal diagnoses, depending on the presentation:
Acute Stress Disorder (DSM-5 code 308.3): A cluster of symptoms — re-experiencing, avoidance, dissociation, hyperarousal — occurring three days to one month after a traumatic event. According to ScienceDirect’s clinical overview, acute stress disorder was added to DSM-4 in 1994 and continued in DSM-5. If symptoms persist beyond one month, the diagnosis transitions to PTSD.
Adjustment Disorder (DSM-5 code 309.x): Also called stress response syndrome, adjustment disorder is characterized by emotional or behavioral symptoms developing within three months of an identifiable stressor, with the response exceeding what would typically be expected. According to Cleveland Clinic, adjustment disorder is the closest formal diagnosis to what most people mean by a nervous breakdown — a reaction to life stress that goes beyond normal coping and impairs functioning.
Major Depressive Episode with functional collapse: Some people reaching breaking point are experiencing a full major depressive episode in which the severity has progressed to the point where daily functioning is no longer possible. This is distinct from chronic depression — it represents an acute, severe deterioration.
Panic disorder or severe anxiety with acute decompensation: When anxiety has been building for weeks or months without adequate intervention, the nervous system can reach a point of acute decompensation — a sudden loss of the compensatory mechanisms that were keeping the person functional.
Understanding which of these is actually happening matters enormously, because the recovery path for each is different. A colloquial label is useful for describing the experience. A clinical assessment is necessary for addressing it.
Why Women Are Disproportionately Vulnerable

Before examining the signs, it’s important to understand the landscape. Women don’t simply experience nervous breakdowns at higher rates by coincidence. The disparity is structural, biological, and social simultaneously.
According to a 2025 review published in European Psychiatry by Thibaut, women are twice as likely as men to suffer from depression, generalized anxiety disorder, and PTSD — and the reasons are multifactorial. The review identifies societal expectations, gender stereotypes, work-life imbalance, and structural inequalities as drivers alongside biological factors.
According to the American Psychiatric Association’s Mental Health Facts for Women, each year, one in five women in the United States experiences a mental health problem such as depression, PTSD, or an anxiety disorder. According to NIMH data cited by mhstats.org (2026), 24.5% of adult women had an anxiety disorder in the past year — representing approximately 31.2 million women.
Women working full-time are almost twice as likely to face mental health problems as men, according to 2024 data from South Denver Therapy’s review of epidemiological statistics. Women also accounted for 71% of all mental health-related workplace absences in early 2024.
The reasons are not simply biological. Research consistently identifies the invisible mental load — the cognitive and emotional labour of managing households, relationships, and caregiving responsibilities that continues alongside formal employment — as a significant structural risk factor. Women are more likely to live in poverty, more likely to take time off for caregiving, more likely to work in lower-paying industries, and more likely to carry the emotional management of their family system. This is the context in which nervous breakdowns in women most commonly occur: not a sudden dramatic event, but the accumulated weight of sustained demands that have finally exceeded the system’s capacity to hold them.
The Hormone Factor: Why Timing Matters
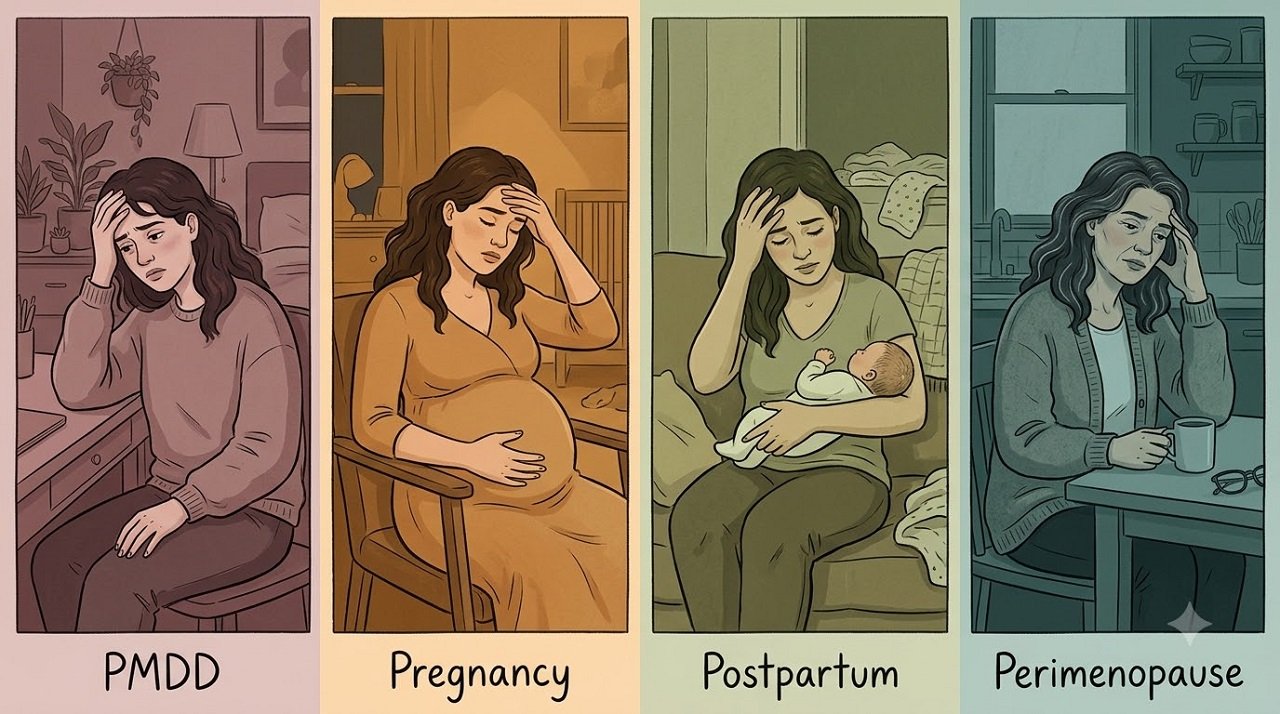
This is the dimension of nervous breakdowns in women that most content on this keyword omits entirely — and it is essential for understanding why certain life stages represent specific vulnerability windows.
Premenstrual Dysphoric Disorder (PMDD) and the menstrual cycle: Women with PMDD have a clinically documented exaggerated response to normal hormonal fluctuations across the menstrual cycle. Research cited by Mission Connection Healthcare notes that PMDD involves an abnormal sensitivity to the hormonal shifts of the luteal phase (the week or two before menstruation), producing mood instability, anxiety, and depressive symptoms intense enough to mimic major depressive disorder in some cases. For women already under sustained stress, this monthly hormonal disruption can repeatedly push the nervous system past its regulatory capacity.
Pregnancy and postpartum: According to a 2025 editorial published in Frontiers in Psychiatry by Reisel and colleagues, postpartum depression affects up to 17% of women, and severe mental illness carries approximately a 24% chance of major relapse during pregnancy, often linked to medication discontinuation. The early postpartum period — marked by sleep deprivation, hormonal upheaval, identity shifts, and social isolation — represents one of the highest-risk windows for acute mental health crisis in women.
Perimenopause: This is perhaps the most underrecognised trigger. According to a 2024 study published in the British Journal of Psychiatry Open by Reisel, Crockett, Glynne, Kamal, and Newson involving 978 women, the five most prevalent symptoms during perimenopause and menopause were: feeling tired or lacking in energy (96%), memory problems (93%), difficulty concentrating (91%), irritability (90%), and feeling tense or nervous (90%). The same study noted that these psychological symptoms are frequently unrecognised as hormone-related, leading to misdiagnosis with anxiety or depression and prescription of antidepressants rather than hormone replacement therapy.
According to Harvard Medical School’s HMS Magazine, prevalence estimates for perimenopausal depression alone are as high as 40%, with approximately two million US women beginning perimenopause each year. Yet the mood and cognitive symptoms of perimenopause are so frequently attributed to stress or life circumstances that many women are never told their nervous system is operating in a period of profound hormonal instability — one that creates a specific and measurable vulnerability to mental health crisis.
Signs of a Nervous Breakdown in Women: What to Actually Look For
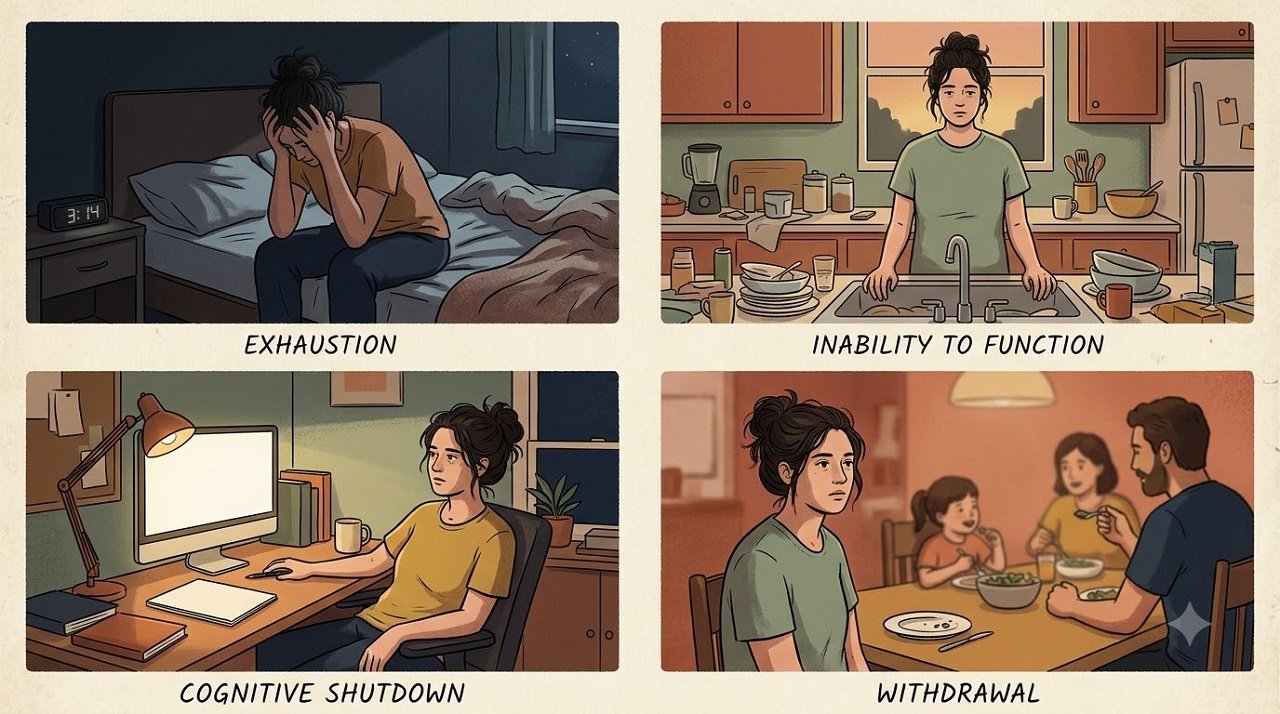
Because “nervous breakdown” covers several clinical presentations, the signs below span the full range of what women experience across those presentations. They are organised by domain rather than by diagnosis, because in the lived experience, symptoms don’t arrive in neatly labelled categories.
Emotional Signs:
You feel overwhelmed in a way that is qualitatively different from ordinary stress — as if the floor of your coping capacity has given way rather than just feeling stretched. Crying unexpectedly, often, or without being able to stop. Swinging between emotional extremes — intense anxiety or panic in one moment, complete emotional numbness in the next. A pervasive sense of dread with no specific object, or a constant state of low-grade panic. Anger or irritability that feels uncharacteristic and disproportionate — directed at people you love over things that wouldn’t normally register. Feeling like you are a burden to the people around you, or that they would be better off without you managing things.
Cognitive Signs:
Difficulty concentrating on even simple tasks that were previously automatic. A sense that your thinking has slowed, fragmented, or become unreliable — what is sometimes described as “brain fog” but with a quality of genuine cognitive impairment rather than tiredness. Difficulty making decisions — even small, everyday ones feel paralysing. Intrusive thoughts that arrive without invitation and are difficult to dismiss. Forgetting appointments, commitments, or conversations you would normally retain easily.
Physical Signs:
Profound exhaustion that sleep does not repair. Physical symptoms with no clear organic cause — headaches, chest tightness, gastrointestinal disturbance, muscle aches, or a persistent sensation of physical unease. According to Mission Connection Healthcare’s clinical coverage of mental breakdowns in women, over 50% of women undergoing mental health crises report disrupted sleep patterns. Changes in appetite — eating significantly less, more, or with a complete absence of genuine hunger or satisfaction. Uncontrollable episodes of shaking, breathlessness, or physical symptoms that resemble — and may be — panic attacks.
Behavioural Signs:
Withdrawal from relationships and social contact — not as a preference but as an inability to manage the additional demand of being around other people. Neglecting responsibilities that you have previously managed reliably: work, household tasks, personal hygiene, commitments to others. Increased reliance on alcohol, food, or other substances as a way of blunting the internal experience. An inability to complete a normal day — not a difficult day, but an ordinary one — without reaching a point of complete inability to continue.
Signs Specific to the Context of Women’s Lives:
Feeling as though you have been holding everything together for everyone else for so long that there is nothing left for yourself — and that acknowledging this feels like failure. A growing resentment toward the people whose needs you have been managing, accompanied by guilt about the resentment. The sense that the role you occupy — as mother, partner, caregiver, employee — has consumed the person you are underneath it. An inability to ask for help that goes beyond preference: the help-seeking itself requires resources you no longer have.
The Breakdown Nobody Sees Coming: The High-Functioning Path
Many women who experience nervous breakdowns were, in the weeks or months preceding it, the person everyone else would have described as the most capable person in the room. They were managing multiple demands, meeting all their obligations, appearing composed under pressure.
This is not coincidental. The same mechanisms described in our post on how to tell if you have high-functioning depression — the productivity-as-coping pattern, the masking of internal distress, the sense of identity tied to capability — are also present in women approaching a breakdown. The breakdown doesn’t happen because they stopped coping. It happens because the coping systems that were running at full capacity for months or years have finally depleted.
The warning signs in the weeks before a crisis often include: increasing difficulty sleeping despite exhaustion, a noticeable reduction in the ability to tolerate small frustrations, withdrawal from social activities that were previously maintained, and a growing internal monologue of dread or hopelessness that the person is working hard to not show externally.
How a Nervous Breakdown Differs From Burnout and Depression
These three experiences share significant symptom overlap and are frequently confused. The distinctions below reflect clinical literature rather than rigid categories, because in practice they often coexist.
Burnout is context-specific and occupational by clinical definition (ICD-11 QD85). Its defining features — cynicism and reduced sense of efficacy — are tethered to the work context. Burnout can be a pathway toward a nervous breakdown if the occupational depletion is sustained long enough, but it is not the same state. As discussed in our post on what is emotional exhaustion vs burnout, burnout improves when the occupational stressor is removed.
Depression — specifically major depressive disorder or persistent depressive disorder — is a clinical condition with its own diagnostic criteria and treatment protocol. A nervous breakdown may include a depressive episode, may trigger one, or may be the presentation of an untreated one that has reached functional collapse. They are not the same thing, but they can overlap.
A nervous breakdown is specifically characterised by acute functional collapse — the person stops being able to manage the basic demands of their daily life. It has a more sudden quality than depression (which typically builds gradually) and a more total quality than burnout (which is context-specific). It represents a system that has not merely been strained, but has given way.
What to Do If You Recognise These Signs

If the signs are present but function is still intact: This is the window in which intervention is most effective and recovery is fastest. Speak with a GP or mental health professional. Reduce nonessential demands immediately. Communicate to the people closest to you that you are not managing — this is not weakness; it is necessary information for the people who can help.
If function has already collapsed: This is a mental health crisis. Contact a GP, a mental health crisis line, or go to an emergency department if you or someone you know is in immediate danger. This is not something to wait out or manage alone.
Specific to the hormonal dimension: If the timing of your symptoms aligns with your menstrual cycle, perimenopause, the postpartum period, or another hormonal transition, bring this specifically to your clinician’s attention. As the research from Reisel et al. (2024) demonstrates, hormonal contributors are consistently underrecognised and frequently misattributed to stress or life circumstances. A clinician who is not explicitly asked about the hormonal dimension may not assess it.
Trauma responses: For women whose breakdown is connected to a history of trauma or prolonged stress, the trauma responses post on this site provides context for understanding the nervous system patterns that may be active in the background.
Frequently Asked Questions
What is a nervous breakdown, exactly?
A nervous breakdown is not a formal medical or psychiatric diagnosis. It is a colloquial term describing a point at which psychological resources have been depleted to the degree that a person can no longer function normally in daily life. Clinically, what people describe as a nervous breakdown typically corresponds to acute stress disorder, adjustment disorder, a severe major depressive episode, or acute anxiety decompensation — depending on the specific presentation and precipitating factors.
Are the signs of a nervous breakdown different in women than in men?
The core symptom profile — exhaustion, inability to function, emotional dysregulation, social withdrawal, physical symptoms — is similar across sexes. What differs in women are the specific precipitating factors: hormonal transitions (perimenopause, postpartum, PMDD), the disproportionate weight of caregiving and invisible mental load, and the higher baseline rates of depression, anxiety, and PTSD that mean women are operating with less systemic reserve before they reach crisis. According to a 2025 review published in European Psychiatry, women are twice as likely as men to experience depression, generalised anxiety disorder, and PTSD.
How long does a nervous breakdown last?
Duration varies widely depending on the underlying clinical condition, the severity of the breakdown, and whether and when appropriate support is sought. Adjustment disorder, one of the closest clinical equivalents, is defined as resolving within six months when the stressor is removed. Acute stress disorder resolves within one month by definition. A breakdown underpinned by a major depressive episode or untreated anxiety disorder requires treatment and follows the course of those conditions. Early intervention substantially shortens recovery time.
Can a nervous breakdown happen without an obvious cause or triggering event?
Yes. While acute stress disorder and adjustment disorder are triggered by identifiable stressors, a breakdown underpinned by accumulated chronic stress — the kind that builds over months or years of sustained demand — may not have a single identifiable trigger. It may feel to the person as though nothing “big” happened. The depletion was gradual; the collapse just became apparent suddenly.
Is it possible to prevent a nervous breakdown?
Early recognition of the warning signs — sustained sleep disruption, progressive difficulty tolerating ordinary stress, intrusive thoughts, withdrawal from relationships — and intervention before functional collapse is the most reliable prevention pathway. For women in high-risk hormonal windows (perimenopause, postpartum), proactive engagement with mental health support reduces risk. The research is consistent that untreated stress accumulation and unaddressed underlying conditions are the primary pathways toward crisis.
Sources & References
- Thibaut F. “Recent progress in women’s mental health research and future priorities.” European Psychiatry, 2025. doi:10.1192/j.eurpsy.2025.146. pmc.ncbi.nlm.nih.gov/articles/PMC12437347
- American Psychiatric Association. “Mental Health Facts for Women.” APA. psychiatry.org/getmedia/aa325a61/Mental-Health-Facts-for-Women.pdf
- National Institute of Mental Health (NIMH). “Any Anxiety Disorder: Women.” U.S. Department of Health and Human Services. nimh.nih.gov/health/statistics/any-anxiety-disorder
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, 5th Edition, Text Revision (DSM-5-TR). APA Publishing, 2022. psychiatry.org
- Cleveland Clinic. “Adjustment Disorders: What They Are, Symptoms and Treatment.” Reviewed 2024. my.clevelandclinic.org/health/diseases/21760-adjustment-disorder
- Reisel D, Crockett C, Glynne S, Kamal A, Newson L. “Prevalence of Cognitive and Mood-Related Symptoms in a Large Cohort of Perimenopausal and Menopausal Women.” BJPsych Open, 2024. doi:10.1192/bjo.2024.497. ncbi.nlm.nih.gov/pmc/articles/PMC11738833
- Harvard Medical School HMS Magazine. “The Mental Health Aspects of Menopause.” magazine.hms.harvard.edu/articles/mental-health-aspects-menopause
- Frontiers in Psychiatry Editorial. “Women with neuropsychiatric disorders: understanding and personalising needs.” 2025. doi:10.3389/fpsyt.2025.1719997. ncbi.nlm.nih.gov/pmc/articles/PMC12704316
- ScienceDirect Topics. “Acute Stress Disorder — clinical overview.” sciencedirect.com/topics/neuroscience/acute-stress-disorder
- Mission Connection Healthcare. “Triggers and Signs of a Mental Breakdown in Women.” missionconnectionhealthcare.com/mental-health/nervous-breakdown/women
- Sleep Disturbance and Perimenopause Narrative Review. MDPI Healthcare, 2025. doi:10.3390/healthcare. ncbi.nlm.nih.gov/pmc/articles/PMC11901009
- mhstats.org. “Anxiety in Women 2026.” Based on NIMH 2024 data. mhstats.org/women/anxiety
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If you are in crisis or experiencing thoughts of self-harm, please contact a mental health crisis helpline or your local emergency services immediately.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you are experiencing persistent physical or emotional symptoms that are significantly affecting your daily life, please consult a qualified healthcare professional.
Both feel like running on empty. Both drain your ability to show up for work, relationships, and yourself. And both are increasingly common in a world where the boundary between productive effort and chronic depletion has become nearly invisible.
But emotional exhaustion and burnout are not the same thing — and that difference matters far more than most articles on this topic acknowledge. Here’s why: the recovery strategies for each are meaningfully different. Approaching burnout with emotional exhaustion strategies, or vice versa, is one of the most common reasons people try to feel better and don’t.
This post draws on the WHO’s official ICD-11 definition of burnout, the Maslach Burnout Inventory — the most widely validated clinical measurement tool for burnout — and current research on emotional exhaustion to explain exactly what each is, how they relate to each other, and how to tell which one you’re actually dealing with.
The Definition Problem Most Articles Skip Entirely
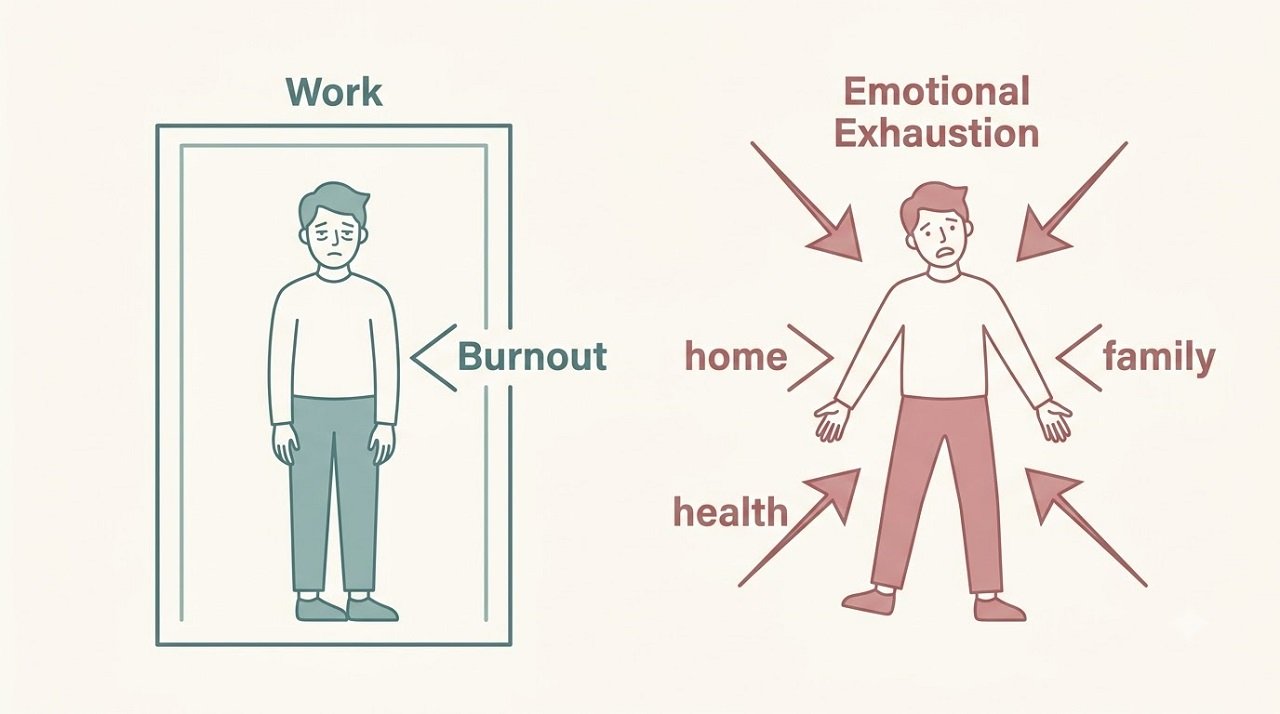
Here is the fact that changes the entire conversation: according to the World Health Organization’s International Classification of Diseases, 11th Revision (ICD-11), burnout is classified under code QD85 as an occupational phenomenon — not a medical condition. The official WHO definition, which came into effect in January 2022, states that burnout is specifically applicable to the workplace and should not be used to describe experiences in other areas of life.
This is not a technicality. It is the central distinction that makes burnout and emotional exhaustion different things.
Burnout — as formally defined by the WHO — can only occur in an occupational context. It arises specifically from chronic workplace stress that has not been successfully managed. It cannot, by definition, be caused by your marriage, your caregiving responsibilities for an aging parent, your chronic illness, or your social isolation. If the source of your depletion is not primarily occupational, what you may be experiencing is emotional exhaustion — which is a broader, non-context-specific state.
According to the WHO’s ICD-11, burnout is a syndrome resulting from chronic workplace stress that has not been successfully managed, characterised by three dimensions: feelings of energy depletion or exhaustion, increased mental distance from one’s job or feelings of negativism or cynicism related to one’s job, and a sense of ineffectiveness and lack of accomplishment (WHO, 2022).
Most people — and many general articles on this topic — use “burnout” as a catch-all for feeling utterly depleted in any domain of life. That usage is understandable. But it blurs a clinically meaningful distinction, and it leads to recovery approaches that don’t address what’s actually driving the problem.
What Is Emotional Exhaustion?
Emotional exhaustion is a state of profound physical, mental, and emotional depletion resulting from sustained, high-demand experience — in any area of life, not just work.
According to ScienceDirect’s clinical overview of emotional exhaustion, it is defined as fatigue or progressive wearing out — physical and mental — resulting from excessive emotional stresses, particularly influenced by work conditions and personal emotional demands. Crucially, unlike burnout, emotional exhaustion is not restricted to the occupational context. It can develop from caregiving responsibilities, relationship stress, chronic illness, grief, financial pressure, or any sustained situation that makes demands on your emotional and physical reserves without adequate recovery.
A 2024 study published in Medical News Today notes that self-care behaviours may make people less prone to burnout and emotional exhaustion, and that while most research links emotional exhaustion to the workplace, it is becoming a growing issue in academic settings including university students.
Emotional exhaustion is also the first and most prominent symptom dimension of burnout itself. This is where the relationship between the two becomes important to understand, and where most competing articles on this keyword get tangled.
How Emotional Exhaustion and Burnout Relate: The Three-Dimensional Model
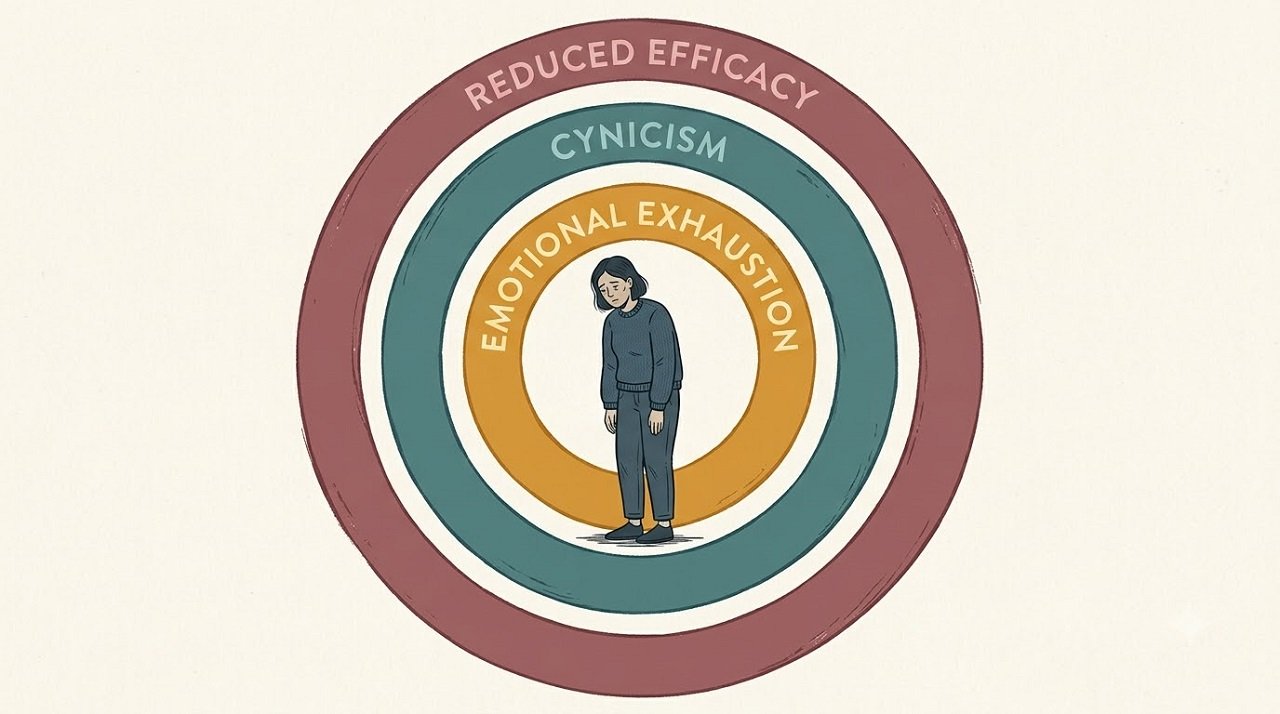
The most widely used clinical framework for measuring and understanding burnout is the Maslach Burnout Inventory (MBI), developed by social psychologist Christina Maslach and published in 1981. The MBI shaped the ICD-11 triadic definition of burnout and remains the gold standard measurement instrument across burnout research globally.
According to Maslach and Jackson’s foundational definition, burnout is a syndrome characterised by emotional exhaustion — feeling emotionally overextended and drained by work — alongside depersonalisation, a negative and excessively detached response toward the people one serves, and lack of personal accomplishment, defined as feelings of incompetence and lack of achievement at work (Maslach & Jackson, 1981).
According to the MBI framework, burnout is not a single symptom — it is a three-dimensional syndrome. And emotional exhaustion is not synonymous with burnout. It is the first and central dimension of burnout, from which the other two dimensions typically develop.
Dimension 1 — Emotional exhaustion: Feeling overextended, drained, and depleted by your work. This is burnout’s core. Research published in Burnout: A Review of Theory and Measurement (PMC, 2022) notes that exhaustion is considered the hallmark of burnout — the feature most consistently present and most strongly associated with impaired functioning. It is both the entry point into burnout and the feature that most closely resembles general emotional exhaustion outside the occupational context.
Dimension 2 — Depersonalisation (cynicism): A distancing response to the depletion. An increasingly detached, negative, or cynical attitude toward your work, your colleagues, or the people you serve. This is not a personality change — it is the nervous system creating emotional distance to manage a resource it can no longer sustain. Research published in PMC notes that burnout syndrome — comprising emotional exhaustion, physical fatigue, and cognitive weariness — is caused by long-term uncontrolled work stressors, and that persistent burnout is associated with increased risk of several medical conditions including mild cognitive impairment, diabetes, and cardiovascular disease (Neuropsychiatric Disease and Treatment, 2022).
Dimension 3 — Reduced personal accomplishment: A growing sense of inefficacy — the feeling that your efforts are not producing meaningful results, that you are less capable than you once were, and that the work no longer has the meaning it once held.
The clinical picture: Emotional exhaustion alone — even severe emotional exhaustion — is not the same as full burnout. Full burnout, in the Maslach framework, requires all three dimensions to be present at meaningful levels. A person who is emotionally depleted but still feels engaged with their work and effective in it is experiencing emotional exhaustion, not necessarily burnout. A person who has all three dimensions — depleted, cynical, and ineffective — is experiencing burnout as clinically defined.
A Practical Distinction: What Causes Each
The sources of emotional exhaustion are broad and life-encompassing. They include occupational stress, but also:
- Primary caregiving for a child, parent, or ill partner
- Chronic illness or pain that demands sustained coping effort
- Prolonged financial stress or housing insecurity
- Relationship conflict, grief, or social isolation
- Sustained high-emotional-demand roles outside work — volunteering, community leadership, activism
- Academic overload, particularly in high-stakes programmes
Burnout, by the WHO’s ICD-11 definition, is specifically and exclusively occupational. The WHO’s ICD-11 is explicit on this point: burnout specifically refers to phenomena in the professional context and should not be applied to describe experiences in other areas of life (WHO, 2022).
This distinction has a practical implication: if you are a stay-at-home caregiver feeling profoundly depleted, emotionally numb, and as though your efforts are invisible and ineffective — that is not burnout in the clinical sense. It may be emotional exhaustion compounded by the isolation and invisibility of caregiving roles. It is real, it is significant, and it warrants the same attention as occupational burnout. But the recovery path is different because the source is different.
Signs of Emotional Exhaustion
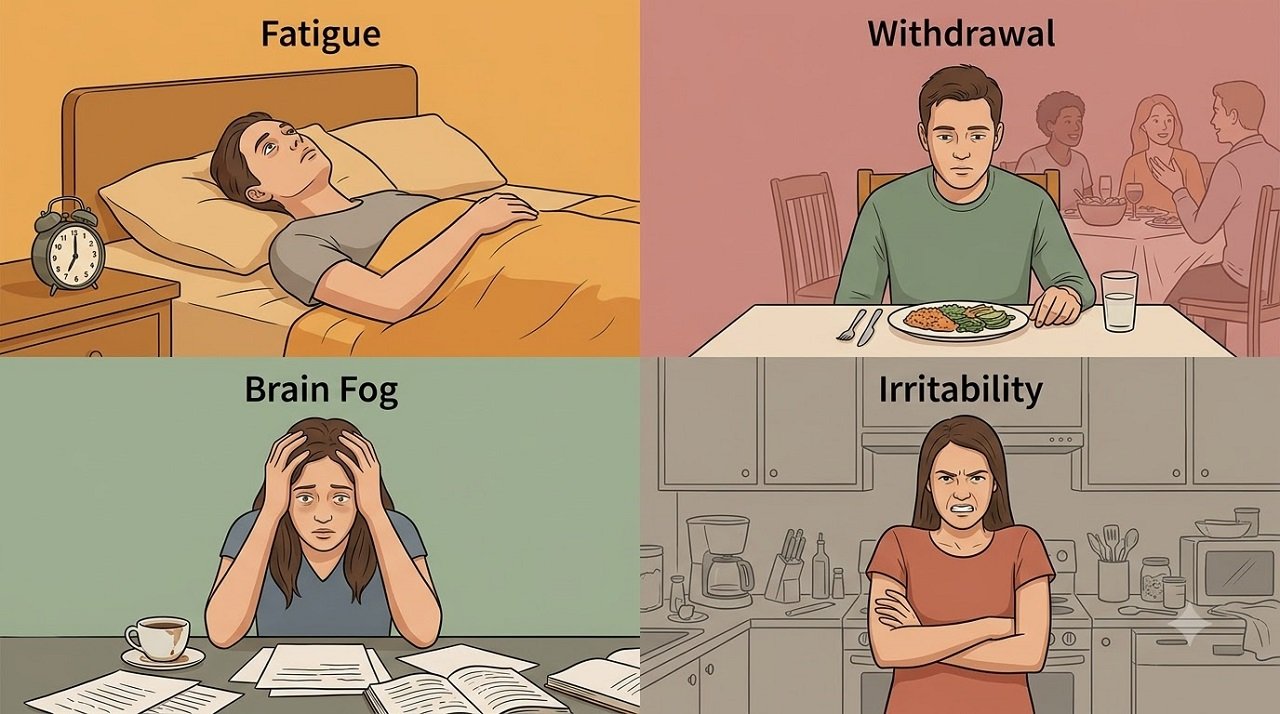
Emotional exhaustion has both physical and psychological features. Unlike burnout, which tends to develop gradually through the three dimensions described above, emotional exhaustion can develop in any demanding context and often presents as an undifferentiated collapse of capacity.
Physical signs:
- Persistent fatigue that doesn’t improve with rest or sleep
- Frequent illness, as chronic stress suppresses immune function
- Headaches, muscle tension, or unexplained physical pain
- Changes in appetite — eating significantly more or less than usual
- Sleep disruption — difficulty falling asleep, staying asleep, or waking unrefreshed
Some of these physical symptoms — particularly the fatigue, muscle tension, and sleep disruption — overlap closely with the physical effects of anxiety. The underlying physiological mechanism is similar: sustained stress hormone activation wearing down the body’s systems. For a detailed explanation of how that process works physically, see our post on what does an anxiety attack feel like physically.
Emotional and cognitive signs:
- A flat, detached quality to daily experience — going through the motions without genuine engagement
- Difficulty feeling positive emotions — happiness, excitement, or anticipation feel muted or absent
- Increased irritability or emotional reactivity over minor triggers
- Difficulty concentrating, making decisions, or retaining information
- Feeling trapped, helpless, or as though nothing you do makes a difference
- A persistent sense of dread about demands that were previously manageable
Relational signs:
- Withdrawing from people you care about because social interaction requires energy you don’t have
- Difficulty being present in conversations — mind wandering, responses slow
- Resentment toward the people or roles making demands on you, even when the resentment feels disproportionate
According to the APA’s 2024 Work in America study, emotional exhaustion affected 25% of workers in the preceding month, with 44% reporting feeling emotionally drained and 51% feeling used up at the end of each workday (APA, 2024).
Signs of Burnout

Burnout shares emotional exhaustion’s features but adds the two additional MBI dimensions. The distinguishing signs are specifically occupational in context:
Energy depletion tied to work: The exhaustion is specifically worse in work-related contexts. The prospect of work triggers the depletion. Weekends or time away from work produce some partial recovery, but it doesn’t last — return to the work environment reinstates the depletion relatively quickly.
Cynicism or emotional distance from work: You have developed a detached, negative, or going-through-the-motions relationship with your work that is markedly different from how you once felt about it. Colleagues, clients, or the work itself provoke negative reactions that feel automatic. This isn’t general cynicism — it is specifically tethered to the occupational context.
Reduced sense of efficacy: You feel less competent, less effective, and less meaningful in your role than you once did. Effort no longer translates into felt accomplishment. Achievements that should feel satisfying don’t register. This is not imposter syndrome — it is a genuine reduction in the felt sense of professional purpose and competence.
According to the APA’s 2024 Work in America Survey, 76% of US workers report experiencing at least some level of burnout, with 53% reporting moderate to severe levels, and 77% reporting work-related stress in the past month (APA, 2024).
Aflac’s 2025 WorkForces Report found 72% of US workers reporting moderate-to-high stress levels — the highest recorded in seven years — while Eagle Hill Consulting’s November 2025 survey found 55% of the US workforce currently experiencing burnout, a six-year high.
The Key Diagnostic Question: Which One Are You Dealing With?
This is the question that determines your recovery path.
Ask yourself: If the primary stressor in your life were removed tomorrow, would the depletion lift?
If your depletion is occupational and you left your job — genuinely left, with no immediate pressure to replace it — would you feel meaningfully better within weeks or months? If yes, what you are dealing with is primarily burnout, driven by unmanaged occupational stress. The source is external and specific. Change the source or your relationship to it, and recovery is possible.
If the depletion would persist regardless of what changes in your external circumstances — if it feels less like a reaction to a specific context and more like a systemic collapse of your emotional and physical resources — what you may be dealing with is deeper emotional exhaustion, potentially compounded by depression or other underlying conditions.
A second question: Is the cynicism and detachment specifically occupational, or has it spread across your whole life?
Burnout’s cynicism is characteristically work-specific, at least in the early and middle stages. You go home and feel the detachment lift somewhat — you can be present with your family, enjoy a meal, feel something. If the detachment is pervasive — across work, relationships, and personal life — emotional exhaustion has likely progressed significantly, and the possibility of depression alongside it warrants attention.
Burnout vs Emotional Exhaustion vs Depression: The Overlap Problem
This is where clinical assessment becomes genuinely important, because these three conditions share features that are difficult to disentangle from the inside.
Research published in Burnout: A Comprehensive Review (Zeitschrift für Arbeitswissenschaft, 2024) notes that existing measurement instruments for burnout often yield scores that overlap with other conditions such as fatigue, anxiety, and depression, making self-assessment inherently limited.
Research notes that although burnout is a distinct phenomenon, there is documented overlap with depressive symptoms, and individuals with severe clinical burnout may develop transient manifestations of depression or subclinical depression (Neuropsychiatric Disease and Treatment, 2022).
The practical guidance from the clinical literature is consistent: if rest and reduction of stressors produce meaningful improvement within a few weeks, depression is less likely to be the primary driver. If the depletion, flatness, and loss of enjoyment persist even when external demands ease, a clinical assessment for depression alongside burnout or emotional exhaustion is appropriate. As discussed in the high-functioning depression post on this site, persistent depressive disorder in particular can coexist with high functioning and is frequently missed in people whose productivity remains intact.
Recovery: Why the Distinction Matters

Recovering from emotional exhaustion requires reducing the overall demand load — across all life domains, not just work — and restoring the basic physiological and psychological conditions for recovery: sleep, nutrition, physical movement, and genuine rest. Emotional exhaustion responds to rest because the nervous system has the capacity to recover once demands are sufficiently reduced. Boundary-setting, reducing emotional labour, and building recovery time into daily routines are the primary tools.
According to Medical News Today (reviewed January 2025), recovery from emotional exhaustion includes reducing or removing nonessential demands where possible, consistent sleep and nourishing meals, light physical movement, setting clear boundaries, and scheduling genuine downtime rather than passive scrolling or numbing. In cases where emotional exhaustion has developed alongside anxiety or depression, professional support including therapy or medication may be required (Medical News Today, 2025).
Recovering from burnout requires addressing the occupational source, not just restoring the individual. Research published in Burnout Research (Salminen et al., 2017) and clinical guidance from HelpGuide (reviewed May 2026) both highlight that individual-level interventions — mindfulness, exercise, sleep — are insufficient for burnout unless combined with meaningful changes to the work environment itself. A research review cited by HelpGuide found that mindfulness-based interventions produced measurable but modest improvements in burnout, and that structural workplace changes — workload reduction, increased autonomy, improved management quality — produced larger and more sustained effects.
According to Gallup’s 2024 State of the Global Workplace report, managers account for 70% of the variance in team engagement, yet only 44% of managers globally have received any formal management training — a deficit the report directly correlates with burnout and disengagement.
This means that if your burnout is primarily driven by a manager who is absent, volatile, or creates an environment of chronic pressure, self-care strategies will provide partial and temporary relief at best. The structural source needs to be addressed — through conversation with the manager, escalation, role change, or in some cases, leaving the role.
Structured psychological therapy — including CBT, Acceptance and Commitment Therapy (ACT), and psychodynamic psychotherapy — has an evidence base for both conditions. A study cited by Baltimore Therapy Group found that structured psychological interventions produce measurable improvements in burnout symptoms and emotional exhaustion in healthcare professionals. Therapy is particularly important when either condition has progressed to the point where self-care strategies are insufficient, or where depression, anxiety, or trauma responses are compounding the presentation.
Side-by-Side Summary
| Feature | Emotional Exhaustion | Burnout (ICD-11/WHO) |
|---|---|---|
| Formal classification | Not formally classified | ICD-11 code QD85 — occupational phenomenon |
| Context | Any life domain | Occupational only |
| Core experience | Profound depletion of emotional and physical resources | Energy depletion + cynicism + reduced efficacy |
| Relationship to work | May be unrelated to work | Specifically and primarily work-driven |
| Cynicism or detachment | May be general | Specifically occupational |
| Sense of efficacy | May be intact | Characteristically reduced |
| Responds to rest | Often yes, meaningfully | Partial — structural change usually also needed |
| Overlaps with depression | Yes | Yes — particularly in severe or prolonged cases |
| Primary recovery lever | Demand reduction, restoration, boundaries | Demand reduction + occupational source addressed |
Frequently Asked Questions
Can you have emotional exhaustion and burnout at the same time? Yes. Burnout’s first dimension is emotional exhaustion — so anyone with full burnout is also experiencing emotional exhaustion. But emotional exhaustion can exist without full burnout (without the cynicism and reduced efficacy dimensions), and it can be driven by non-occupational sources that burnout by definition does not include.
Does burnout ever go away on its own without treatment? Research on burnout longitudinal outcomes suggests that burnout can reduce when occupational conditions improve significantly — a change in manager, a reduction in workload, or a role change. But without addressing the structural source of the chronic stress, individual-level recovery strategies are unlikely to produce lasting improvement. Severe or prolonged burnout also carries a risk of progressing to clinical depression, which requires professional treatment.
How long does recovery from burnout or emotional exhaustion take? There is no reliable universal timeline. Research on burnout recovery (Salminen et al., 2017) found recovery processes unfolding over two years in some cases, depending on severity, the presence of comorbid depression, and whether structural changes to the work environment were made. Emotional exhaustion without the full burnout syndrome can respond more quickly to demand reduction — weeks to a few months — when the source is identified and reduced.
Can physical exercise help with burnout? Yes, with an important caveat. Exercise has a meaningful evidence base for improving mood, sleep, and stress resilience. But adding a demanding exercise routine to an already depleted system can add to rather than relieve the load. During active burnout or emotional exhaustion, gentle, restorative movement — walking, yoga, light stretching — is more consistently helpful than high-intensity training, which makes additional demands on an already stressed nervous system.
Is burnout the same as being stressed? No. Stress is a state of heightened activation — the nervous system is engaged and under pressure. Burnout is what happens when that pressure is sustained long enough that the system depletes. The physiologist and burnout researcher Christina Maslach described it this way: stress is characterised by overengagement, burnout by disengagement. Stressed people feel that they have too much to do; burned-out people feel they have nothing left to give.
Sources & References
- World Health Organization. “Burn-out an ‘Occupational Phenomenon’: International Classification of Diseases.” ICD-11, QD85. WHO, May 2019. who.int/news/item/28-05-2019-burn-out-an-occupational-phenomenon-international-classification-of-diseases
- Maslach C, Jackson SE. “The measurement of experienced burnout.” Journal of Occupational Behaviour, 2(2):99–113, 1981. doi:10.1002/job.4030020205.
- Ahola K, Toppinen-Tanner S, Seppänen J. “Interventions to alleviate burnout symptoms and to support return to work among employees with burnout: systematic review and meta-analysis.” Burnout Research, 4:1–11, 2017. doi:10.1016/j.burn.2017.02.001.
- Pelayo-Terán JM, et al. “ICD-11 Burnout for the psychiatrist: Meaning of the concept and prevalence of the condition.” European Psychiatry, 2024. doi:10.1192/j.eurpsy.2024.321. ncbi.nlm.nih.gov/pmc/articles/PMC11863005
- Salvagioni DAJ, et al. “Physical, psychological and occupational consequences of job burnout: A systematic review of prospective studies.” PLOS ONE, 2017. doi:10.1371/journal.pone.0185781. pmc.ncbi.nlm.nih.gov/articles/PMC5627926
- Bianchi R, Schonfeld IS, Laurent E. “Burnout: Moving beyond the status quo.” International Journal of Stress Management, 26(1):36–45, 2019. ncbi.nlm.nih.gov/pmc/articles/PMC10630726
- Lastovkova A, et al. “Burnout syndrome as an occupational disease in the European Union: an exploratory study.” Industrial Health, 56(2):103–111, 2018. pmc.ncbi.nlm.nih.gov/articles/PMC5889921
- American Psychological Association. “Work in America Survey 2024.” APA, 2024. apa.org/pubs/reports/work-in-america
- Gallup. “State of the Global Workplace Report 2025.” Gallup Press. gallup.com/workplace/349484/state-of-the-global-workplace.aspx
- Medical News Today. “Emotional exhaustion: Causes, symptoms, and recovery.” Reviewed January 2025. medicalnewstoday.com/articles/323441
- ScienceDirect Topics. “Emotional Exhaustion — clinical overview.” sciencedirect.com/topics/nursing-and-health-professions/emotional-exhaustion
- HelpGuide. “Burnout Prevention and Recovery.” Reviewed May 2026. helpguide.org/mental-health/stress/burnout-prevention-and-recovery
- Salminen S, Andreou E, Holma J, Pekkonen M, Mäkikangas A. “Narratives of burnout and recovery from an agency perspective: A two-year longitudinal study.” Burnout Research, 7:1–9, 2017. doi:10.1016/j.burn.2017.06.001.
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If you are in crisis, please contact a mental health crisis helpline or your local emergency services immediately.

PEMF Webinar

Decode Your Digestion Workshop

Meal Sequencing for Early Satiety on GLP-1: Why Protein First Changes Everything
PEMF Webinar

HBOT ( Hyperbaric Oxygen Therapy ) Webinar

The 4-7-8 Breathing Technique: Step-by-Step Guide and What the Research Actually Shows
-
 Events7 hours ago
PEMF Webinar
-
 Events1 month ago
HBOT ( Hyperbaric Oxygen Therapy ) Webinar
-
 Natural Sleep Remedies6 months ago
The 4-7-8 Breathing Technique: Step-by-Step Guide and What the Research Actually Shows
-

 Events6 months ago
The Anti-Cancer Body with Dr. Michael Karlfeldt
-

 Events5 months ago
Why You Can’t Trust Big Pharma
-

 Home Remedies5 months ago
Natural Home Remedies for Restless Legs at Night
-

 Events5 months ago
The Cancer Conversation Your Oncologist Cannot Have in 15 Minutes
-

 Events6 months ago
Beyond the Brain