
Mental Health
What Is Complex PTSD vs PTSD? The Difference That Changes Everything About Treatment

The content on this website – including articles, event announcements, personal experiences, and recommendations – is for informational and educational purposes only and is not medical advice. Always consult a qualified healthcare professional before making any changes to your diet, exercise, supplements, sleep habits, or wellness routines, especially if you are pregnant, nursing, on medication, or have any medical condition.

Published: June 2026 | Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you believe you may have PTSD or Complex PTSD, please consult a qualified mental health professional for a proper evaluation.
Both involve trauma. Both can derail your daily life in ways that are difficult to put into words. But PTSD and Complex PTSD are not the same condition — and the difference between them isn’t just academic. It changes how a diagnosis is made, which diagnostic system your clinician is using, and — most importantly — what kind of treatment is most likely to help.
Here’s what most people searching this question actually need to know: PTSD is recognized in both major diagnostic systems used globally. Complex PTSD is officially recognized in only one of them — and it isn’t the American one. That single fact explains a lot of the confusion, and it’s where this comparison needs to start.
Two Different Diagnostic Systems: Why This Matters

Most people don’t realize there are two major competing systems for classifying mental health conditions, and they don’t agree on Complex PTSD.
The DSM-5 — the Diagnostic and Statistical Manual of Mental Disorders, 5th Edition, published by the American Psychiatric Association (APA) — is the primary system used by clinicians in the United States. The DSM-5 does not include Complex PTSD as a standalone diagnosis. It was considered for inclusion and ultimately not adopted in the 2013 edition or the 2022 text revision (DSM-5-TR).
The ICD-11 — the International Classification of Diseases, 11th Revision, published by the World Health Organization (WHO) — is the diagnostic system used in most of the rest of the world, and increasingly alongside the DSM in international research. Complex PTSD was formally included in ICD-11 in 2022, listed under code 6B41, immediately after the PTSD entry.
This divide has real practical consequences. A psychiatrist in the UK, Australia, or Europe is working from a system that officially recognizes Complex PTSD as distinct from PTSD. A psychiatrist in the US is working from a system that doesn’t — which means the same cluster of symptoms may result in a different diagnosis depending on which country or which clinician framework you encounter. If you’ve been diagnosed with PTSD in the US and feel the diagnosis doesn’t quite fit, the ICD-11 framework may be part of why.
Where Complex PTSD Came From

The concept didn’t emerge from a committee — it came from careful clinical observation of survivors.
Dr. Judith Herman, a Clinical Professor of Psychiatry at Harvard Medical School, first proposed Complex PTSD in a 1992 paper published in the Journal of Traumatic Stress, later expanded in her foundational book Trauma and Recovery: The Aftermath of Violence. Herman’s core observation was that the existing PTSD criteria — developed primarily from studying combat veterans and survivors of single traumatic incidents — failed to capture what happened to people who endured prolonged, repeated trauma, particularly in situations where escape was impossible: childhood abuse, domestic violence, captivity, torture.
As Herman described it in her original formulation, she observed seven domains of disruption in survivors of prolonged trauma that didn’t fit neatly into standard PTSD: alterations in affect regulation, alterations in consciousness (including dissociation), distorted self-perception, altered perceptions of the perpetrator, damaged relationships, somatic symptoms, and changes in meaning systems. The condition she described was not a more severe version of PTSD — it was a different pattern.
Herman’s formulation was not adopted into the DSM when it was considered for DSM-IV, where it was listed tentatively as DESNOS (Disorders of Extreme Stress Not Otherwise Specified). Decades later, it was incorporated into ICD-11 in a form that broadly aligns with her original concept, though with a more structured symptom framework.
PTSD: What It Is and What Causes It
According to the ICD-11, PTSD requires exposure to a traumatic event that was extremely threatening or horrific, followed by three core symptom clusters. The DSM-5 defines the qualifying event somewhat differently — as involving actual or threatened death, serious injury, or sexual violence, experienced directly, witnessed, or learned about happening to a close person.
The three core symptom clusters shared across both systems:
Re-experiencing: The trauma is relived in the present, not just remembered. This includes intrusive memories that appear involuntarily, flashbacks where the person feels as though the event is happening again, and nightmares with content related to the trauma.
Avoidance: Active, deliberate efforts to avoid thoughts, feelings, people, places, or situations that are associated with the traumatic event. This can include emotional numbing as a way of avoiding internal experiences.
A persistent sense of current threat: Hypervigilance, exaggerated startle response, difficulty sleeping, and a constant feeling that danger is near — even in objectively safe situations. In the DSM-5, this category also includes persistent negative changes in thoughts and mood related to the trauma.
PTSD is strongly associated with single-incident traumas: a violent assault, a serious accident, a natural disaster, a combat experience, witnessing a death. According to the National Institute of Mental Health (NIMH), approximately 3.6% of U.S. adults experienced PTSD in the past year, and 6.8% will experience it at some point in their lives. Women are significantly more affected than men — the APA estimates a lifetime prevalence of 10–12% for women compared to 5–6% for men.
Importantly, trauma exposure is common but PTSD is not inevitable. The WHO estimates that while approximately 70% of people globally will experience at least one potentially traumatic event in their lifetime, only about 5.6% of those exposed will go on to develop PTSD.
Complex PTSD: What the ICD-11 Actually Says

Under ICD-11 code 6B41, Complex PTSD requires everything that PTSD requires — the full set of re-experiencing, avoidance, and persistent threat symptoms must be present. But in addition, it requires a second cluster of symptoms called disturbances in self-organization (DSO).
According to the WHO’s ICD-11, these DSO symptoms consist of three domains:
Affect dysregulation: Difficulty managing emotional states, with emotional reactions that are intense, hard to control, or both. This includes emotional numbness — difficulty feeling anything — alongside explosive emotional responses, with little stable middle ground.
Negative self-concept: A deeply ingrained belief that one is diminished, defeated, or worthless, accompanied by persistent feelings of shame, guilt, or failure. This is not ordinary low self-esteem — it’s a fundamental sense of being damaged, broken, or fundamentally different from other people. As Herman’s original clinical notes captured it: people with Complex PTSD often feel as if they have lost themselves entirely.
Disturbances in relationships: Persistent difficulty in forming and maintaining close relationships. This can look like distrust, withdrawal, a pattern of relationships that repeat familiar dynamics of harm, or a simultaneous longing for and fear of closeness.
A 2024 systematic review published in the Journal of Affective Disorders by Kleva and colleagues, involving international clinicians, found that these DSO features were both identifiable and diagnostically distinct — meaning clinicians could reliably differentiate CPTSD from PTSD when trained to look for the DSO cluster specifically. The same review noted that identifying these CPTSD-specific features was necessary for accurate diagnosis, and that missing them led to misclassification.
According to a 2025 study published in the Journal of Affective Disorders using data from an outpatient trauma clinic, CPTSD was generally associated with greater functional impairment, more psychiatric comorbidities, and lower quality of life than PTSD alone.
The Core Difference: Type of Trauma, Not Just Severity

This is probably the most important thing to understand, and the most commonly misrepresented in general articles on this topic.
C-PTSD is not simply a more severe version of PTSD. The distinction isn’t about how bad the trauma was — it’s about the nature and pattern of it.
PTSD more commonly follows a single, bounded traumatic event: even an extraordinarily violent or terrifying one. The trauma had a beginning and an end. The person’s sense of who they are may be shaken, but it was not formed inside the traumatic situation.
Complex PTSD is associated with prolonged, repeated trauma from which escape was difficult or impossible — and which typically occurred within a relationship or system of control. The ICD-11 explicitly lists these as examples: torture, slavery, genocide campaigns, prolonged domestic violence, repeated childhood sexual or physical abuse. In these situations, the trauma wasn’t a disruption to the person’s life — for many survivors, especially those who experienced it in childhood, the trauma was the environment in which their personality, self-image, and relational patterns developed.
That developmental difference is why the DSO symptoms exist in C-PTSD and not in standard PTSD. They aren’t add-on symptoms — they reflect the way prolonged captivity-type trauma reshapes a person’s relationship to themselves, their emotions, and other people at a foundational level.
Side-by-Side Comparison
| Feature | PTSD | Complex PTSD |
|---|---|---|
| Diagnostic system | DSM-5 and ICD-11 | ICD-11 only (not DSM-5) |
| Typical trauma type | Single-incident or bounded trauma | Prolonged, repeated, inescapable trauma |
| Re-experiencing | Yes | Yes |
| Avoidance | Yes | Yes |
| Persistent sense of threat | Yes | Yes |
| Affect dysregulation | Not required | Yes (DSO cluster) |
| Negative self-concept | Not required | Yes (DSO cluster) |
| Relationship disturbances | Not required | Yes (DSO cluster) |
| Sense of self | May be disrupted | Fundamentally altered |
| Treatment approach | Trauma-focused from the start is standard | Often phased approach: stabilization before trauma processing |
What About the DSM-5? How Does It Handle This?
Since the DSM-5 doesn’t include C-PTSD, what does a US clinician do with someone who clearly shows the DSO symptom cluster alongside standard PTSD features?
Several options exist within the DSM framework. The closest available formulation is PTSD with the dissociative subtype — a DSM-5 specifier that captures some of the depersonalization and derealization that often appears in complex trauma survivors. Other clinicians may diagnose the core PTSD plus additional diagnoses for the DSO-related features, such as an emotion regulation disorder or a personality disorder.
The lack of C-PTSD in DSM-5 is a known and debated limitation. Advocates for its inclusion, including many trauma researchers, argue that assigning multiple diagnoses to describe what is essentially one complex condition tied to prolonged trauma is inefficient, potentially stigmatizing, and points toward different (and sometimes less appropriate) treatment pathways than a unified C-PTSD framework would. The debate is ongoing, and it’s possible DSM-6, when it arrives, will address it.
If you are in the US and believe C-PTSD better describes your experience than a standard PTSD diagnosis, it’s a reasonable and evidence-supported thing to raise with your clinician. Some US clinicians are familiar with the ICD-11 framework and will use it alongside DSM-5, particularly for research purposes or in settings with international referral networks.
Does Treatment Differ?

Yes, and this is one of the most clinically significant reasons the distinction matters.
For standard PTSD, the VA/DoD Clinical Practice Guideline (2023) recommends trauma-focused psychotherapy as the first-line treatment, specifically three approaches with the strongest evidence: Prolonged Exposure (PE), Cognitive Processing Therapy (CPT), and Eye Movement Desensitization and Reprocessing (EMDR). These are intensive, trauma-focused approaches that work by helping the person process traumatic memories directly and reduce their emotional charge.
For Complex PTSD, the picture is more nuanced. A 2026 narrative review published in Frontiers in Psychology summarizing psychotherapy for CPTSD found that while trauma-focused approaches including CBT and EMDR are effective at reducing core PTSD symptoms in people with CPTSD, their effects on the DSO symptom cluster — emotion dysregulation, negative self-concept, relational difficulties — are more variable and often smaller.
The International Society for Traumatic Stress Studies (ISTSS) clinical guidelines and many trauma specialists recommend a phased approach for CPTSD:
Phase 1 — Stabilization: Before addressing traumatic memories directly, focus is placed on building emotional safety, developing distress tolerance and regulation skills, establishing a stable therapeutic relationship, and addressing immediate life circumstances. Skills-based interventions such as STAIR (Skills Training in Affective and Interpersonal Regulation) are used in this phase.
Phase 2 — Trauma processing: Once stability is established, trauma-focused work such as EMDR or TF-CBT is introduced. A 2024 RCT cited in the Frontiers in Psychology review found that EMDR or narrative therapy followed by STAIR reduced PTSD symptoms and improved DSO’s affective dysregulation and interpersonal problems in adult survivors of childhood abuse.
Phase 3 — Integration: Consolidating gains, addressing relational patterns, building a sense of self and future.
The phased model is not universally applied — some therapists begin trauma processing earlier where the person is already stable enough — but the general principle that C-PTSD often requires more preparatory work than standard PTSD before diving into trauma processing is well-supported and clinically meaningful.
Frequently Asked Questions
Can you have PTSD and C-PTSD at the same time? Under ICD-11, they are mutually exclusive — a person receives either a PTSD or a C-PTSD diagnosis, not both simultaneously. C-PTSD already includes all PTSD criteria. If the DSO features are present, C-PTSD is the diagnosis. If they are absent, PTSD is the diagnosis. Under DSM-5, which doesn’t have C-PTSD, a clinician might combine a PTSD diagnosis with other diagnoses to capture the full picture.
Does C-PTSD only come from childhood trauma? No — though childhood trauma, particularly prolonged abuse or neglect, is a common cause. The ICD-11 specifies that C-PTSD can develop from any prolonged, repeated traumatic situation from which escape is difficult: domestic violence, torture, captivity, or other prolonged interpersonal harm in adulthood can also lead to C-PTSD.
Why does the DSM-5 not include Complex PTSD? The reasons are partly scientific (debates at the time about whether the evidence was sufficient to establish it as diagnostically distinct) and partly structural (the DSM development process is lengthy and conservative). Many trauma researchers continue to advocate for its inclusion, and the ICD-11’s recognition of C-PTSD has strengthened that case significantly.
Is C-PTSD the same as PTSD with dissociation? No, though they overlap. The DSM-5’s dissociative subtype of PTSD captures some features — specifically depersonalization and derealization — that also appear in many C-PTSD presentations. But the dissociative subtype doesn’t capture the full DSO cluster, particularly the persistent negative self-concept and relationship disturbances. They are related but distinct formulations.
How long does it take to treat C-PTSD compared to PTSD? There’s no reliable universal timeline, but C-PTSD treatment is generally longer than standard PTSD treatment, largely because of the stabilization phase required before trauma processing and because the DSO symptoms — especially the self-concept and relational features — are worked on over a sustained period. Effective treatment is available, but expecting the same timeline as a standard PTSD intervention is unlikely to be realistic.
Sources & References
- World Health Organization. ICD-11: International Classification of Diseases 11th Revision, Code 6B41 — Complex Post Traumatic Stress Disorder. WHO, 2022. icd.who.int
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, 5th Edition, Text Revision (DSM-5-TR). APA Publishing, 2022. psychiatry.org
- Herman JL. “Complex PTSD: A syndrome in survivors of prolonged and repeated trauma.” Journal of Traumatic Stress, 5(3): 377–391, 1992. doi:10.1002/jts.2490050305. pubmed.ncbi.nlm.nih.gov/1427552
- Kleva CS, Keeley JW, Evans SC, et al. “Examining accurate diagnosis of complex PTSD in ICD-11.” Journal of Affective Disorders, 346:110–114, 2024. doi:10.1016/j.jad.2023.10.137. sciencedirect.com
- Brewin CR, Cloitre M, Hyland P, et al. “Complex post-traumatic stress disorder: a new diagnosis in ICD-11.” BJPsych Advances, 26(3):145–152, 2020. doi:10.1192/bja.2019.48. cambridge.org
- National Institute of Mental Health (NIMH). “Post-Traumatic Stress Disorder (PTSD): Statistics.” U.S. Department of Health and Human Services. nimh.nih.gov/health/statistics/post-traumatic-stress-disorder-ptsd
- American Psychological Association. “PTSD Fact Sheet: Prevalence and Characteristics.” APA, 2024. apa.org
- World Health Organization. “Post-traumatic stress disorder: Epidemiology.” WHO, 2024. who.int/news-room/fact-sheets/detail/post-traumatic-stress-disorder
- Veterans Affairs / Department of Defense. “VA/DoD Clinical Practice Guideline for the Management of Posttraumatic Stress Disorder and Acute Stress Reaction.” 2023. ptsd.va.gov/professional/treat/txessentials/overview_therapy.asp
- Amato L, Ciccioli M, Ballerini A. “Psychotherapy for complex post-traumatic stress disorder: efficacy and therapeutic factors.” Frontiers in Psychology, 2026. doi:10.3389/fpsyg.2026.1684921. frontiersin.org
- Knefel M, Lueger-Schuster B. “An evaluation of ICD-11 PTSD and complex PTSD criteria in a sample of adult survivors of childhood institutional abuse.” European Journal of Psychotraumatology, 4(1), 2013. ncbi.nlm.nih.gov/pmc/articles/PMC3851534
- UK Trauma Council. “Post-traumatic stress disorder (PTSD) and Complex PTSD.” uktraumacouncil.org/trauma/ptsd-and-complex-ptsd
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If you are in crisis, please contact a mental health crisis helpline or your local emergency services.













Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you are experiencing persistent physical or emotional symptoms that are significantly affecting your daily life, please consult a qualified healthcare professional.
Both feel like running on empty. Both drain your ability to show up for work, relationships, and yourself. And both are increasingly common in a world where the boundary between productive effort and chronic depletion has become nearly invisible.
But emotional exhaustion and burnout are not the same thing — and that difference matters far more than most articles on this topic acknowledge. Here’s why: the recovery strategies for each are meaningfully different. Approaching burnout with emotional exhaustion strategies, or vice versa, is one of the most common reasons people try to feel better and don’t.
This post draws on the WHO’s official ICD-11 definition of burnout, the Maslach Burnout Inventory — the most widely validated clinical measurement tool for burnout — and current research on emotional exhaustion to explain exactly what each is, how they relate to each other, and how to tell which one you’re actually dealing with.
The Definition Problem Most Articles Skip Entirely
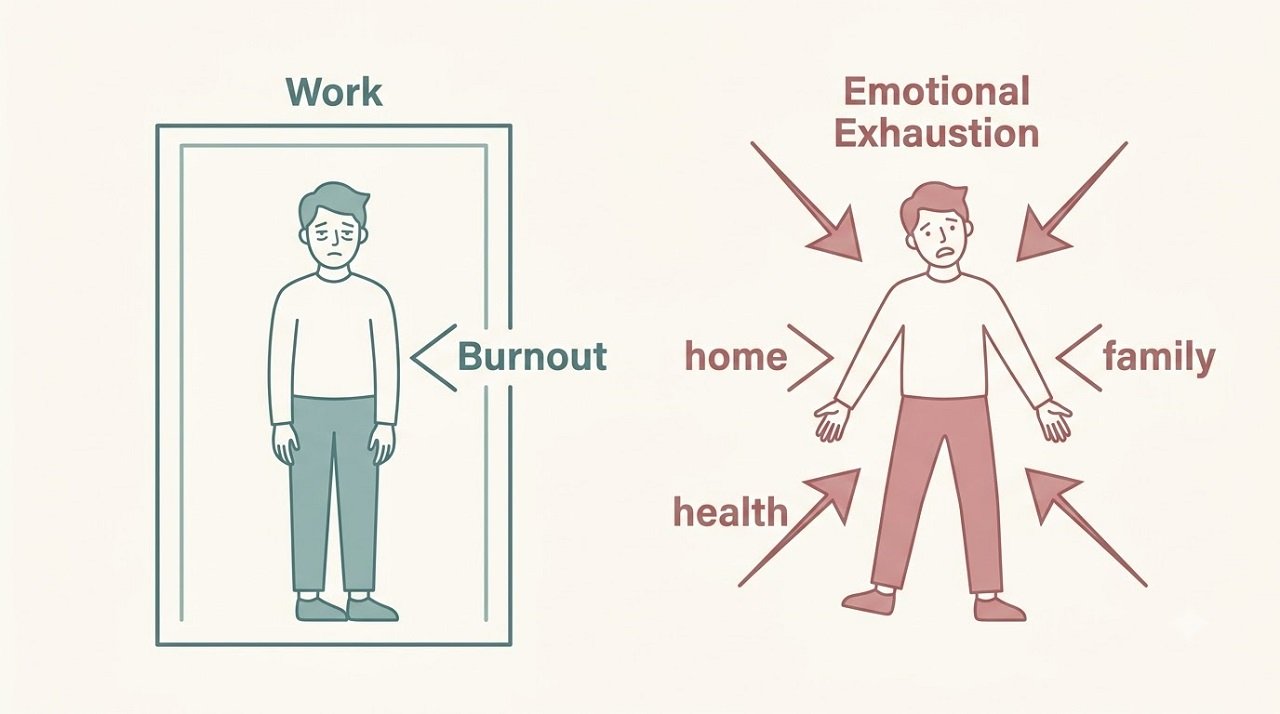
Here is the fact that changes the entire conversation: according to the World Health Organization’s International Classification of Diseases, 11th Revision (ICD-11), burnout is classified under code QD85 as an occupational phenomenon — not a medical condition. The official WHO definition, which came into effect in January 2022, states that burnout is specifically applicable to the workplace and should not be used to describe experiences in other areas of life.
This is not a technicality. It is the central distinction that makes burnout and emotional exhaustion different things.
Burnout — as formally defined by the WHO — can only occur in an occupational context. It arises specifically from chronic workplace stress that has not been successfully managed. It cannot, by definition, be caused by your marriage, your caregiving responsibilities for an aging parent, your chronic illness, or your social isolation. If the source of your depletion is not primarily occupational, what you may be experiencing is emotional exhaustion — which is a broader, non-context-specific state.
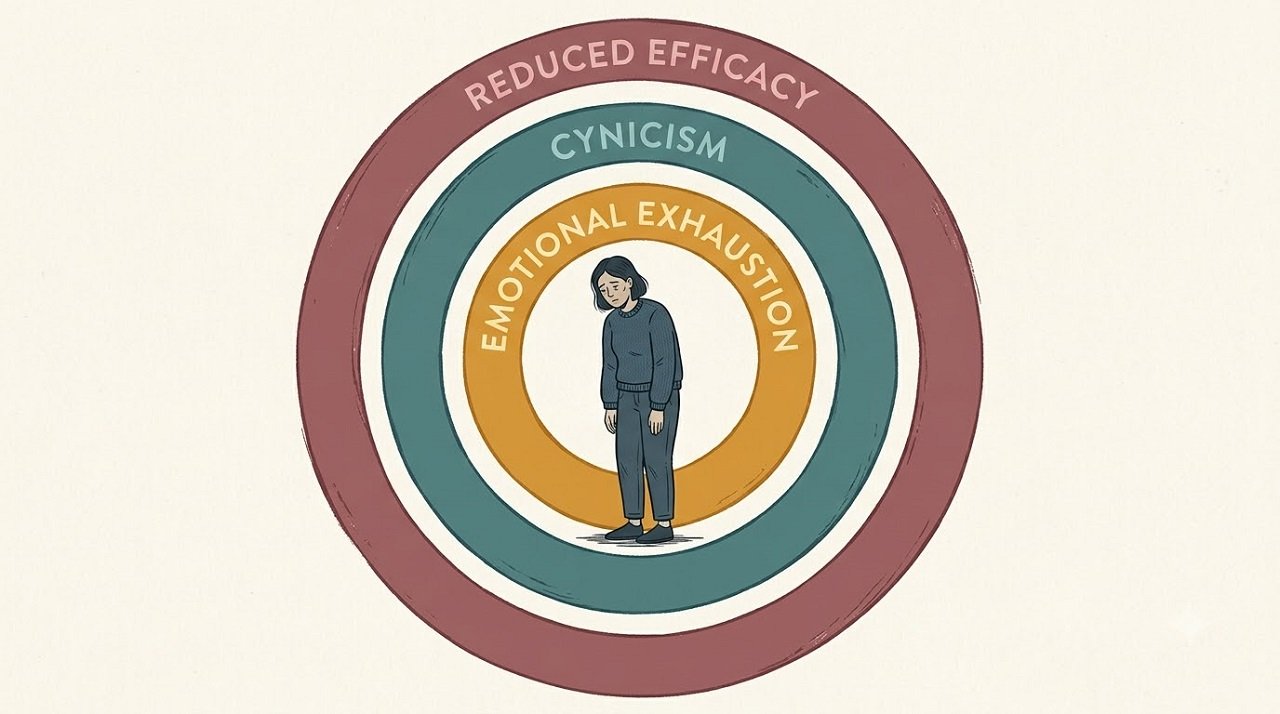
According to the WHO’s ICD-11, burnout is a syndrome resulting from chronic workplace stress that has not been successfully managed, characterised by three dimensions: feelings of energy depletion or exhaustion, increased mental distance from one’s job or feelings of negativism or cynicism related to one’s job, and a sense of ineffectiveness and lack of accomplishment (WHO, 2022).
Most people — and many general articles on this topic — use “burnout” as a catch-all for feeling utterly depleted in any domain of life. That usage is understandable. But it blurs a clinically meaningful distinction, and it leads to recovery approaches that don’t address what’s actually driving the problem.
What Is Emotional Exhaustion?
Emotional exhaustion is a state of profound physical, mental, and emotional depletion resulting from sustained, high-demand experience — in any area of life, not just work.
According to ScienceDirect’s clinical overview of emotional exhaustion, it is defined as fatigue or progressive wearing out — physical and mental — resulting from excessive emotional stresses, particularly influenced by work conditions and personal emotional demands. Crucially, unlike burnout, emotional exhaustion is not restricted to the occupational context. It can develop from caregiving responsibilities, relationship stress, chronic illness, grief, financial pressure, or any sustained situation that makes demands on your emotional and physical reserves without adequate recovery.
A 2024 study published in Medical News Today notes that self-care behaviours may make people less prone to burnout and emotional exhaustion, and that while most research links emotional exhaustion to the workplace, it is becoming a growing issue in academic settings including university students.
Emotional exhaustion is also the first and most prominent symptom dimension of burnout itself. This is where the relationship between the two becomes important to understand, and where most competing articles on this keyword get tangled.
How Emotional Exhaustion and Burnout Relate: The Three-Dimensional Model
The most widely used clinical framework for measuring and understanding burnout is the Maslach Burnout Inventory (MBI), developed by social psychologist Christina Maslach and published in 1981. The MBI shaped the ICD-11 triadic definition of burnout and remains the gold standard measurement instrument across burnout research globally.
According to Maslach and Jackson’s foundational definition, burnout is a syndrome characterised by emotional exhaustion — feeling emotionally overextended and drained by work — alongside depersonalisation, a negative and excessively detached response toward the people one serves, and lack of personal accomplishment, defined as feelings of incompetence and lack of achievement at work (Maslach & Jackson, 1981).
According to the MBI framework, burnout is not a single symptom — it is a three-dimensional syndrome. And emotional exhaustion is not synonymous with burnout. It is the first and central dimension of burnout, from which the other two dimensions typically develop.
Dimension 1 — Emotional exhaustion: Feeling overextended, drained, and depleted by your work. This is burnout’s core. Research published in Burnout: A Review of Theory and Measurement (PMC, 2022) notes that exhaustion is considered the hallmark of burnout — the feature most consistently present and most strongly associated with impaired functioning. It is both the entry point into burnout and the feature that most closely resembles general emotional exhaustion outside the occupational context.
Dimension 2 — Depersonalisation (cynicism): A distancing response to the depletion. An increasingly detached, negative, or cynical attitude toward your work, your colleagues, or the people you serve. This is not a personality change — it is the nervous system creating emotional distance to manage a resource it can no longer sustain. Research published in PMC notes that burnout syndrome — comprising emotional exhaustion, physical fatigue, and cognitive weariness — is caused by long-term uncontrolled work stressors, and that persistent burnout is associated with increased risk of several medical conditions including mild cognitive impairment, diabetes, and cardiovascular disease (Neuropsychiatric Disease and Treatment, 2022).
Dimension 3 — Reduced personal accomplishment: A growing sense of inefficacy — the feeling that your efforts are not producing meaningful results, that you are less capable than you once were, and that the work no longer has the meaning it once held.
The clinical picture: Emotional exhaustion alone — even severe emotional exhaustion — is not the same as full burnout. Full burnout, in the Maslach framework, requires all three dimensions to be present at meaningful levels. A person who is emotionally depleted but still feels engaged with their work and effective in it is experiencing emotional exhaustion, not necessarily burnout. A person who has all three dimensions — depleted, cynical, and ineffective — is experiencing burnout as clinically defined.
A Practical Distinction: What Causes Each
The sources of emotional exhaustion are broad and life-encompassing. They include occupational stress, but also:
- Primary caregiving for a child, parent, or ill partner
- Chronic illness or pain that demands sustained coping effort
- Prolonged financial stress or housing insecurity
- Relationship conflict, grief, or social isolation
- Sustained high-emotional-demand roles outside work — volunteering, community leadership, activism
- Academic overload, particularly in high-stakes programmes
Burnout, by the WHO’s ICD-11 definition, is specifically and exclusively occupational. The WHO’s ICD-11 is explicit on this point: burnout specifically refers to phenomena in the professional context and should not be applied to describe experiences in other areas of life (WHO, 2022).
This distinction has a practical implication: if you are a stay-at-home caregiver feeling profoundly depleted, emotionally numb, and as though your efforts are invisible and ineffective — that is not burnout in the clinical sense. It may be emotional exhaustion compounded by the isolation and invisibility of caregiving roles. It is real, it is significant, and it warrants the same attention as occupational burnout. But the recovery path is different because the source is different.
Signs of Emotional Exhaustion
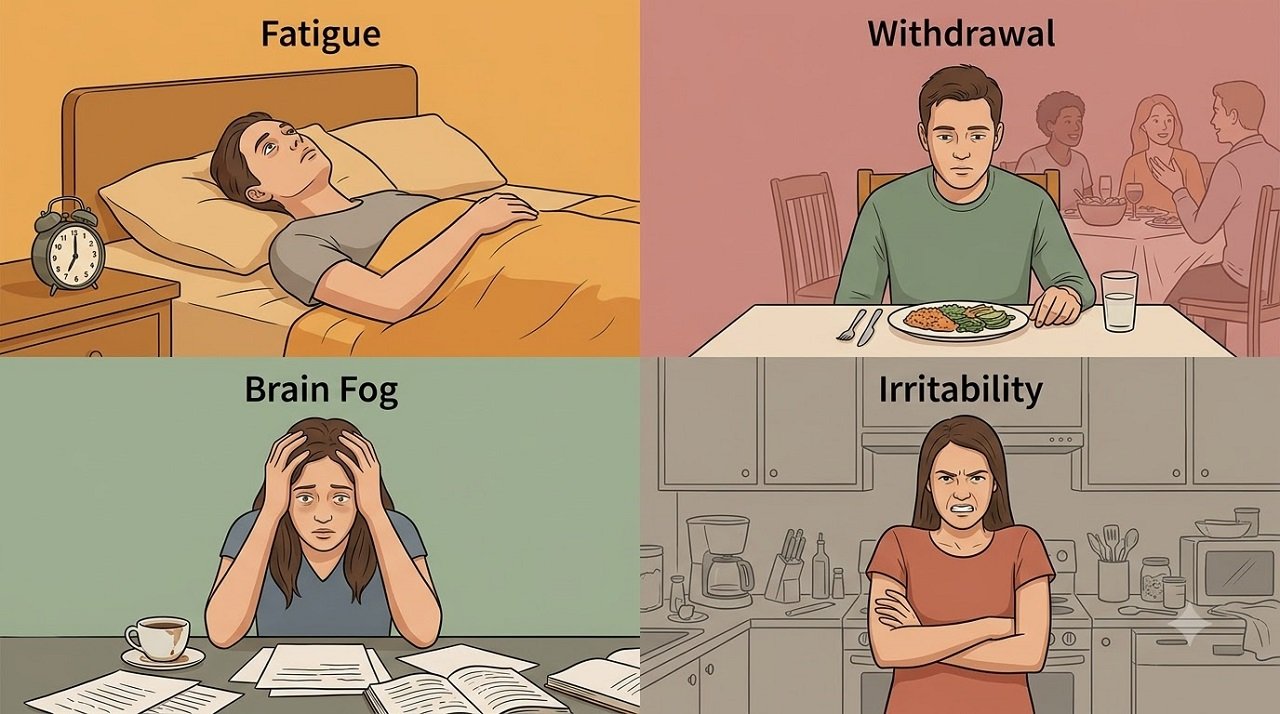
Emotional exhaustion has both physical and psychological features. Unlike burnout, which tends to develop gradually through the three dimensions described above, emotional exhaustion can develop in any demanding context and often presents as an undifferentiated collapse of capacity.
Physical signs:
- Persistent fatigue that doesn’t improve with rest or sleep
- Frequent illness, as chronic stress suppresses immune function
- Headaches, muscle tension, or unexplained physical pain
- Changes in appetite — eating significantly more or less than usual
- Sleep disruption — difficulty falling asleep, staying asleep, or waking unrefreshed
Some of these physical symptoms — particularly the fatigue, muscle tension, and sleep disruption — overlap closely with the physical effects of anxiety. The underlying physiological mechanism is similar: sustained stress hormone activation wearing down the body’s systems. For a detailed explanation of how that process works physically, see our post on what does an anxiety attack feel like physically.
Emotional and cognitive signs:
- A flat, detached quality to daily experience — going through the motions without genuine engagement
- Difficulty feeling positive emotions — happiness, excitement, or anticipation feel muted or absent
- Increased irritability or emotional reactivity over minor triggers
- Difficulty concentrating, making decisions, or retaining information
- Feeling trapped, helpless, or as though nothing you do makes a difference
- A persistent sense of dread about demands that were previously manageable
Relational signs:
- Withdrawing from people you care about because social interaction requires energy you don’t have
- Difficulty being present in conversations — mind wandering, responses slow
- Resentment toward the people or roles making demands on you, even when the resentment feels disproportionate
According to the APA’s 2024 Work in America study, emotional exhaustion affected 25% of workers in the preceding month, with 44% reporting feeling emotionally drained and 51% feeling used up at the end of each workday (APA, 2024).
Signs of Burnout

Burnout shares emotional exhaustion’s features but adds the two additional MBI dimensions. The distinguishing signs are specifically occupational in context:
Energy depletion tied to work: The exhaustion is specifically worse in work-related contexts. The prospect of work triggers the depletion. Weekends or time away from work produce some partial recovery, but it doesn’t last — return to the work environment reinstates the depletion relatively quickly.
Cynicism or emotional distance from work: You have developed a detached, negative, or going-through-the-motions relationship with your work that is markedly different from how you once felt about it. Colleagues, clients, or the work itself provoke negative reactions that feel automatic. This isn’t general cynicism — it is specifically tethered to the occupational context.
Reduced sense of efficacy: You feel less competent, less effective, and less meaningful in your role than you once did. Effort no longer translates into felt accomplishment. Achievements that should feel satisfying don’t register. This is not imposter syndrome — it is a genuine reduction in the felt sense of professional purpose and competence.
According to the APA’s 2024 Work in America Survey, 76% of US workers report experiencing at least some level of burnout, with 53% reporting moderate to severe levels, and 77% reporting work-related stress in the past month (APA, 2024).
Aflac’s 2025 WorkForces Report found 72% of US workers reporting moderate-to-high stress levels — the highest recorded in seven years — while Eagle Hill Consulting’s November 2025 survey found 55% of the US workforce currently experiencing burnout, a six-year high.
The Key Diagnostic Question: Which One Are You Dealing With?
This is the question that determines your recovery path.
Ask yourself: If the primary stressor in your life were removed tomorrow, would the depletion lift?
If your depletion is occupational and you left your job — genuinely left, with no immediate pressure to replace it — would you feel meaningfully better within weeks or months? If yes, what you are dealing with is primarily burnout, driven by unmanaged occupational stress. The source is external and specific. Change the source or your relationship to it, and recovery is possible.
If the depletion would persist regardless of what changes in your external circumstances — if it feels less like a reaction to a specific context and more like a systemic collapse of your emotional and physical resources — what you may be dealing with is deeper emotional exhaustion, potentially compounded by depression or other underlying conditions.
A second question: Is the cynicism and detachment specifically occupational, or has it spread across your whole life?
Burnout’s cynicism is characteristically work-specific, at least in the early and middle stages. You go home and feel the detachment lift somewhat — you can be present with your family, enjoy a meal, feel something. If the detachment is pervasive — across work, relationships, and personal life — emotional exhaustion has likely progressed significantly, and the possibility of depression alongside it warrants attention.
Burnout vs Emotional Exhaustion vs Depression: The Overlap Problem
This is where clinical assessment becomes genuinely important, because these three conditions share features that are difficult to disentangle from the inside.
Research published in Burnout: A Comprehensive Review (Zeitschrift für Arbeitswissenschaft, 2024) notes that existing measurement instruments for burnout often yield scores that overlap with other conditions such as fatigue, anxiety, and depression, making self-assessment inherently limited.
Research notes that although burnout is a distinct phenomenon, there is documented overlap with depressive symptoms, and individuals with severe clinical burnout may develop transient manifestations of depression or subclinical depression (Neuropsychiatric Disease and Treatment, 2022).
The practical guidance from the clinical literature is consistent: if rest and reduction of stressors produce meaningful improvement within a few weeks, depression is less likely to be the primary driver. If the depletion, flatness, and loss of enjoyment persist even when external demands ease, a clinical assessment for depression alongside burnout or emotional exhaustion is appropriate. As discussed in the high-functioning depression post on this site, persistent depressive disorder in particular can coexist with high functioning and is frequently missed in people whose productivity remains intact.
Recovery: Why the Distinction Matters

Recovering from emotional exhaustion requires reducing the overall demand load — across all life domains, not just work — and restoring the basic physiological and psychological conditions for recovery: sleep, nutrition, physical movement, and genuine rest. Emotional exhaustion responds to rest because the nervous system has the capacity to recover once demands are sufficiently reduced. Boundary-setting, reducing emotional labour, and building recovery time into daily routines are the primary tools.
According to Medical News Today (reviewed January 2025), recovery from emotional exhaustion includes reducing or removing nonessential demands where possible, consistent sleep and nourishing meals, light physical movement, setting clear boundaries, and scheduling genuine downtime rather than passive scrolling or numbing. In cases where emotional exhaustion has developed alongside anxiety or depression, professional support including therapy or medication may be required (Medical News Today, 2025).
Recovering from burnout requires addressing the occupational source, not just restoring the individual. Research published in Burnout Research (Salminen et al., 2017) and clinical guidance from HelpGuide (reviewed May 2026) both highlight that individual-level interventions — mindfulness, exercise, sleep — are insufficient for burnout unless combined with meaningful changes to the work environment itself. A research review cited by HelpGuide found that mindfulness-based interventions produced measurable but modest improvements in burnout, and that structural workplace changes — workload reduction, increased autonomy, improved management quality — produced larger and more sustained effects.
According to Gallup’s 2024 State of the Global Workplace report, managers account for 70% of the variance in team engagement, yet only 44% of managers globally have received any formal management training — a deficit the report directly correlates with burnout and disengagement.
This means that if your burnout is primarily driven by a manager who is absent, volatile, or creates an environment of chronic pressure, self-care strategies will provide partial and temporary relief at best. The structural source needs to be addressed — through conversation with the manager, escalation, role change, or in some cases, leaving the role.
Structured psychological therapy — including CBT, Acceptance and Commitment Therapy (ACT), and psychodynamic psychotherapy — has an evidence base for both conditions. A study cited by Baltimore Therapy Group found that structured psychological interventions produce measurable improvements in burnout symptoms and emotional exhaustion in healthcare professionals. Therapy is particularly important when either condition has progressed to the point where self-care strategies are insufficient, or where depression, anxiety, or trauma responses are compounding the presentation.
Side-by-Side Summary
| Feature | Emotional Exhaustion | Burnout (ICD-11/WHO) |
|---|---|---|
| Formal classification | Not formally classified | ICD-11 code QD85 — occupational phenomenon |
| Context | Any life domain | Occupational only |
| Core experience | Profound depletion of emotional and physical resources | Energy depletion + cynicism + reduced efficacy |
| Relationship to work | May be unrelated to work | Specifically and primarily work-driven |
| Cynicism or detachment | May be general | Specifically occupational |
| Sense of efficacy | May be intact | Characteristically reduced |
| Responds to rest | Often yes, meaningfully | Partial — structural change usually also needed |
| Overlaps with depression | Yes | Yes — particularly in severe or prolonged cases |
| Primary recovery lever | Demand reduction, restoration, boundaries | Demand reduction + occupational source addressed |
Frequently Asked Questions
Can you have emotional exhaustion and burnout at the same time? Yes. Burnout’s first dimension is emotional exhaustion — so anyone with full burnout is also experiencing emotional exhaustion. But emotional exhaustion can exist without full burnout (without the cynicism and reduced efficacy dimensions), and it can be driven by non-occupational sources that burnout by definition does not include.
Does burnout ever go away on its own without treatment? Research on burnout longitudinal outcomes suggests that burnout can reduce when occupational conditions improve significantly — a change in manager, a reduction in workload, or a role change. But without addressing the structural source of the chronic stress, individual-level recovery strategies are unlikely to produce lasting improvement. Severe or prolonged burnout also carries a risk of progressing to clinical depression, which requires professional treatment.
How long does recovery from burnout or emotional exhaustion take? There is no reliable universal timeline. Research on burnout recovery (Salminen et al., 2017) found recovery processes unfolding over two years in some cases, depending on severity, the presence of comorbid depression, and whether structural changes to the work environment were made. Emotional exhaustion without the full burnout syndrome can respond more quickly to demand reduction — weeks to a few months — when the source is identified and reduced.
Can physical exercise help with burnout? Yes, with an important caveat. Exercise has a meaningful evidence base for improving mood, sleep, and stress resilience. But adding a demanding exercise routine to an already depleted system can add to rather than relieve the load. During active burnout or emotional exhaustion, gentle, restorative movement — walking, yoga, light stretching — is more consistently helpful than high-intensity training, which makes additional demands on an already stressed nervous system.
Is burnout the same as being stressed? No. Stress is a state of heightened activation — the nervous system is engaged and under pressure. Burnout is what happens when that pressure is sustained long enough that the system depletes. The physiologist and burnout researcher Christina Maslach described it this way: stress is characterised by overengagement, burnout by disengagement. Stressed people feel that they have too much to do; burned-out people feel they have nothing left to give.
Sources & References
- World Health Organization. “Burn-out an ‘Occupational Phenomenon’: International Classification of Diseases.” ICD-11, QD85. WHO, May 2019. who.int/news/item/28-05-2019-burn-out-an-occupational-phenomenon-international-classification-of-diseases
- Maslach C, Jackson SE. “The measurement of experienced burnout.” Journal of Occupational Behaviour, 2(2):99–113, 1981. doi:10.1002/job.4030020205.
- Ahola K, Toppinen-Tanner S, Seppänen J. “Interventions to alleviate burnout symptoms and to support return to work among employees with burnout: systematic review and meta-analysis.” Burnout Research, 4:1–11, 2017. doi:10.1016/j.burn.2017.02.001.
- Pelayo-Terán JM, et al. “ICD-11 Burnout for the psychiatrist: Meaning of the concept and prevalence of the condition.” European Psychiatry, 2024. doi:10.1192/j.eurpsy.2024.321. ncbi.nlm.nih.gov/pmc/articles/PMC11863005
- Salvagioni DAJ, et al. “Physical, psychological and occupational consequences of job burnout: A systematic review of prospective studies.” PLOS ONE, 2017. doi:10.1371/journal.pone.0185781. pmc.ncbi.nlm.nih.gov/articles/PMC5627926
- Bianchi R, Schonfeld IS, Laurent E. “Burnout: Moving beyond the status quo.” International Journal of Stress Management, 26(1):36–45, 2019. ncbi.nlm.nih.gov/pmc/articles/PMC10630726
- Lastovkova A, et al. “Burnout syndrome as an occupational disease in the European Union: an exploratory study.” Industrial Health, 56(2):103–111, 2018. pmc.ncbi.nlm.nih.gov/articles/PMC5889921
- American Psychological Association. “Work in America Survey 2024.” APA, 2024. apa.org/pubs/reports/work-in-america
- Gallup. “State of the Global Workplace Report 2025.” Gallup Press. gallup.com/workplace/349484/state-of-the-global-workplace.aspx
- Medical News Today. “Emotional exhaustion: Causes, symptoms, and recovery.” Reviewed January 2025. medicalnewstoday.com/articles/323441
- ScienceDirect Topics. “Emotional Exhaustion — clinical overview.” sciencedirect.com/topics/nursing-and-health-professions/emotional-exhaustion
- HelpGuide. “Burnout Prevention and Recovery.” Reviewed May 2026. helpguide.org/mental-health/stress/burnout-prevention-and-recovery
- Salminen S, Andreou E, Holma J, Pekkonen M, Mäkikangas A. “Narratives of burnout and recovery from an agency perspective: A two-year longitudinal study.” Burnout Research, 7:1–9, 2017. doi:10.1016/j.burn.2017.06.001.
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If you are in crisis, please contact a mental health crisis helpline or your local emergency services immediately.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you believe you may be experiencing trauma responses that are significantly affecting your daily life, please consult a qualified mental health professional.
The most disorienting thing about trauma responses is that they don’t feel like responses. They feel like personality.
The person who shuts down in conflict doesn’t think “I am having a freeze response.” They think “I am someone who goes quiet when things get difficult.” The person who over-apologises constantly doesn’t recognise a survival strategy — they recognise themselves. The person who works relentlessly and can never sit still doesn’t identify an active flight response. They call it ambition.
Trauma responses are automatic nervous system strategies that were learned — or hardwired — during experiences of threat. The problem is that once they’re wired in, they don’t stay in the past where the threat was. They come forward into the present, running in situations that don’t require them, shaping how you move through relationships, work, and daily life in ways that can be nearly invisible from the inside.
This post explains what the four primary trauma responses actually are, how they show up not in dramatic crisis moments but in ordinary daily patterns, and what the research says about recognising them in yourself.
What Trauma Responses Actually Are

The original model of the stress response was simple: fight or flight. When your body perceived danger, the physiologist Walter Cannon — who chaired the physiology department at Harvard Medical School in the 1920s — observed that the body mobilised for survival through one of two strategies: confront the threat or escape it. The nervous system flooded the bloodstream with adrenaline and cortisol, heart rate accelerated, muscles tensed, and the body prepared for action.
That model explains acute physical danger well. It falls apart when you try to use it to explain what happens to someone who lives for years in an environment that is not quite safe — a volatile household, an abusive relationship, a childhood with an unpredictable caregiver.
Over the following decades, clinicians and researchers expanded the original framework. Freeze was recognised as a third strategy — immobilisation and shutdown when fighting or fleeing isn’t possible. Fawn was added to describe a fourth pattern: appeasement. Rather than confronting, escaping, or going still, some people — particularly those who grew up depending on an unsafe or unpredictable caregiver — learned that the safest available response to threat was to make the threat happy. To agree, accommodate, and disappear into compliance.
Together, fight, flight, freeze, and fawn describe the four primary survival strategies the autonomic nervous system can deploy when it perceives a threat it cannot reason its way through.
The key phrase is the autonomic nervous system. These responses are not conscious choices. According to a paper published in the Harvard Review of Psychiatry in 2015, the defence cascade — the series of biological responses underlying fight, flight, freeze, and related survival behaviours — is mediated by different branches of the autonomic nervous system, activated by different neurochemical cascades, and expressed in different behavioural patterns. What they share is that they all originate below the level of conscious awareness. By the time you notice what’s happening, the response is already running.
That biological reality is why trauma responses are so difficult to recognise from the inside. You don’t decide to go still in conflict. Your nervous system makes that calculation before your conscious mind has registered what’s happening.
The Nervous System Behind the Responses
Understanding the basics of how the nervous system works in a threat response makes the four patterns much easier to recognise in yourself.
The autonomic nervous system has two primary branches: the sympathetic nervous system, responsible for activation and arousal — the accelerator — and the parasympathetic nervous system, responsible for calming and restoration — the brake.
In a perceived threat, the sympathetic branch activates. The amygdala — a small structure deep in the temporal lobe, sometimes called the brain’s alarm system — detects the threat and signals the hypothalamus, which triggers the adrenal glands to release adrenaline and cortisol. Heart rate spikes, breathing accelerates, muscles mobilise, and digestion slows — the same cascade that drives the physical symptoms of an anxiety attack. This is the biological foundation of fight and flight..
Fight and flight are both sympathetic nervous system responses — states of high activation aimed at generating action. Fight mobilises that energy toward confrontation; flight mobilises it toward escape.
Freeze is different. According to the window of tolerance framework developed by psychiatrist Dan Siegel, first outlined in his 1999 book The Developing Mind, freeze involves a drop below what Siegel called the optimal arousal zone — a state of hypoarousal or shutdown, rather than hyper-activation. Research published in the Journal of Psychopharmacology by Corrigan, Fisher, and Nutt in 2011 describes this as the dorsal vagal shutdown response — a collapse or immobilisation state in which the nervous system effectively shuts down to manage an overwhelming threat it cannot otherwise survive. Freeze can co-exist with high fear and high internal activation while externally looking like numbness, blankness, or paralysis.
Fawn operates through a different mechanism again. The fawn response, clinically described and named by therapist Pete Walker and supported by research in polyvagal theory developed by Dr. Stephen Porges, refers to a survival strategy wired into the nervous system through relational trauma — particularly situations where the threat was the caregiver, and where fighting, fleeing, or freezing all carried their own risks. In that context, the most adaptive available strategy was to become agreeable, helpful, and emotionally invisible. To make the threat feel good so it would pass.
The Window of Tolerance: A Self-Recognition Tool
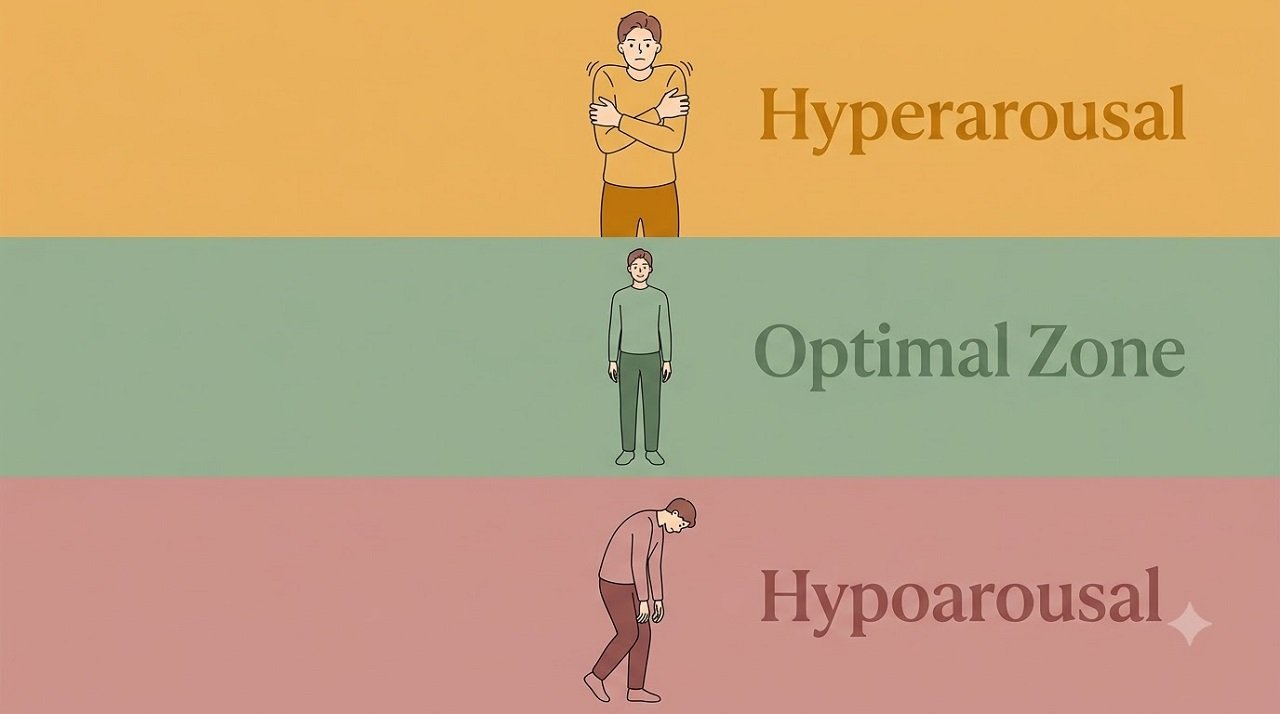
The window of tolerance is one of the most useful frameworks for recognising trauma responses in yourself — not just in clinical settings, but in ordinary daily life.
The concept, developed by Dan Siegel and complemented by Stephen Porges’ polyvagal theory, describes an optimal zone of arousal within which you can function effectively: processing what’s happening, regulating your emotions, staying present in conversations, and recovering from stress without extreme swings in either direction.
Above the window — hyperarousal: Anxiety, panic, rage, hypervigilance, an inability to slow down, racing thoughts, a body that won’t settle. Fight and flight responses live here.
Below the window — hypoarousal: Numbness, shutdown, dissociation, emotional blankness, profound fatigue, a feeling of being cut off from your own experience. Freeze lives here. According to the illuminated thinking clinical guide on window of tolerance, written by a clinical psychologist, hypoarousal is particularly common in people with trauma histories but is frequently misread from the outside — and sometimes from the inside — as laziness, apathy, or high-functioning depression.
The window itself narrows with trauma. According to Psychology Tools’ clinical reference on window of tolerance, trauma-related conditions such as PTSD and C-PTSD are characterised by narrowed or unstable windows, making it difficult to stay within the optimal zone. A narrowed window means that smaller stressors — the kind other people seem to handle without incident — can tip you into hyperarousal or hypoarousal. If you’ve ever had a reaction that felt disproportionate to the situation and couldn’t quite explain why, a narrowed window of tolerance is often part of what’s happening.
How Each Response Shows Up in Daily Life

This is where most articles on trauma responses fall short. They describe the four responses in acute, dramatic terms — a deer in headlights, a soldier’s combat response. What they don’t describe is how these same responses show up on a Tuesday afternoon in an ordinary life.
Fight: Not necessarily anger or aggression, though it can be. In everyday life, fight often shows up as defensiveness triggered faster than the situation calls for, difficulty receiving feedback without feeling attacked, a tendency to control situations, arguments, or outcomes to manage a sense of threat, and an internal experience of being on guard most of the time. The body may feel tense, jaw clenched, ready. People with a dominant fight response sometimes describe feeling like they’re always braced for something.
Flight: The busiest people you know are sometimes running the most active flight responses. Flight in daily life looks like compulsive productivity, difficulty sitting still, chronic over-scheduling, a need to always have the next thing planned, and anxiety that spikes when nothing is happening. It also shows up as avoidance — postponing difficult conversations, leaving relationships before they can go wrong, physically leaving spaces when emotional discomfort arrives. The movement is always away from something, even when the something isn’t consciously identified as a threat.
Freeze: In daily life, freeze looks like going blank mid-conversation when something triggers discomfort, difficulty making decisions under pressure, a tendency to do nothing when action is needed, dissociation or a sense of watching events from a slight remove, and a profound difficulty getting started on tasks that feel threatening. Freeze can also look like compliance — staying in situations that aren’t working because the body can’t mobilise to leave. According to Kozlowska and colleagues’ 2015 paper in the Harvard Review of Psychiatry, freeze is best understood as fight-or-flight put on hold: the body is fully mobilised internally, but the external expression is stillness.
Fawn: This is the response that most consistently gets misread as a personality trait rather than a survival strategy, because it generates positive social feedback. Fawn in daily life looks like difficulty saying no even when you want to, automatic agreement with people who seem upset or powerful, a compulsive monitoring of others’ emotional states to assess whether the environment is safe, over-apologising as a reflex rather than a genuine response to wrongdoing, and a deep discomfort with conflict that goes beyond ordinary social preference. The internal experience of fawn is often exhausting — a constant vigilance about other people’s moods and needs, with your own needs quietly subordinated to maintaining the relationship and avoiding threat.
Recognising Trauma Responses: The Patterns Worth Noticing
Not everyone who experiences trauma develops chronic trauma responses, and not every person with trauma responses has experienced what would conventionally be called trauma. The Adverse Childhood Experiences (ACE) study — conducted by researchers Vincent Felitti and Robert Anda through a partnership between Kaiser Permanente and the CDC, surveying more than 17,000 adult patients — found a graded, dose-response relationship between adverse childhood experiences and adult health outcomes. As the number of ACEs increased, so did the risk of depression, anxiety, and a range of physical health conditions. Critically, the study demonstrated that early and repeated exposure to adversity doesn’t just create psychological symptoms — it measurably rewires the stress response system itself.
A 2015 study published in PLOS ONE by Infurna and colleagues, using a 30-day daily diary study of community-residing adults, found that childhood trauma was associated with greater emotional reactivity to everyday negative events — not just major stressors. Adults with childhood trauma histories showed stronger decreases in well-being when encountering ordinary daily negative events compared to those without such histories. This is the window of tolerance narrowing in action, measured in the data of daily life.
The following patterns, taken together, are worth noticing in yourself:
Reactions that feel disproportionate to the present. You notice afterward that your response — anger, shutdown, people-pleasing, or sudden need to leave — was larger than the situation called for. You can’t always explain why. This gap between the present situation and the size of your response is one of the most consistent signals that a trauma response was active.
Your body reacts before your mind catches up. Racing heart, chest tightness, sudden blankness, or a surge of physical tension before you’ve consciously assessed a situation as threatening. The amygdala’s threat detection is faster than conscious thought — this physical-first quality is a defining feature of trauma responses.
You default to the same response regardless of what the situation actually calls for. The freeze person goes still in conflict even when assertiveness would be more useful. The fawn person agrees even when the situation requires a boundary. The flight person gets busy when sitting with discomfort might produce a better outcome. When a single strategy runs regardless of context, the automaticity of a trauma response rather than a conscious choice is often what’s operating.
The response feels like you, not like a reaction. As described at the opening of this article, the most disorienting feature of chronic trauma responses is that they feel like personality. If you’ve been freezing in conflict since childhood, you don’t experience it as a response — you experience it as introversion, or conflict-avoidance, or just how you are. This self-identification is not wrong, exactly. But it’s incomplete. The response was adaptive once. It was learned for good reason. And it can, with the right support, be updated.
Hybrid Patterns: When You Run More Than One
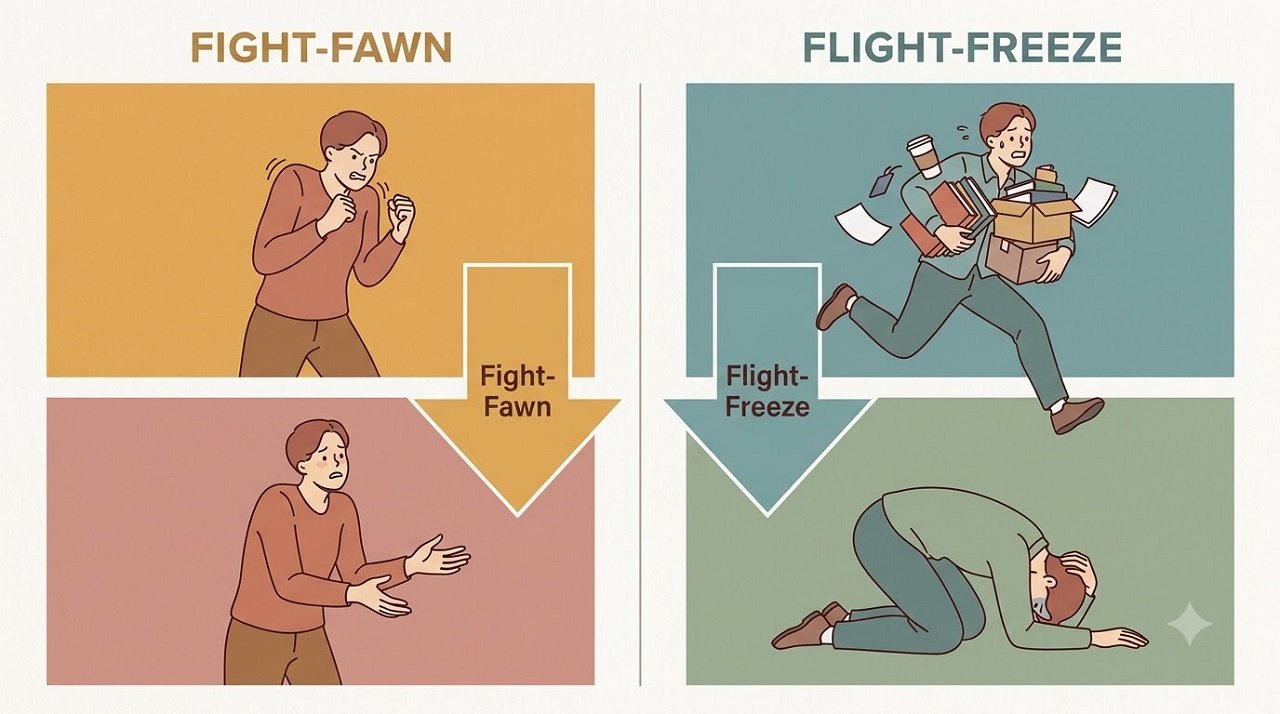
Most people don’t run a single, pure response. Research on complex trauma and attachment — including the foundational attachment research by Main and Hesse (1990) on disorganised attachment — found that when the caregiver was simultaneously the source of comfort and the source of threat, the child’s developing nervous system learned that no single strategy reliably produced safety. The result, in adulthood, is often a shifting between multiple survival modes depending on the relationship or context.
Some common hybrid patterns:
Fight-fawn describes someone who alternates between aggressive boundary enforcement and complete capitulation — holding a hard line one moment, then suddenly appeasing and withdrawing the next. This pattern often confuses the people around them, and frequently confuses the person themselves.
Flight-freeze looks like periods of frantic overactivity followed by crashes of complete shutdown — full engagement and then total withdrawal, cycling in ways that can be misread as inconsistency, unreliability, or in more severe presentations, sometimes misdiagnosed as a mood disorder.
Freeze-fawn is common in people with histories of prolonged relational trauma — particularly childhood abuse — where both immobilisation and appeasement were active strategies. The person goes still in conflict and simultaneously works to make the other person comfortable, often at significant cost to their own wellbeing.
What Trauma Responses Are Not
Before discussing what to do with this recognition, it’s worth naming what trauma responses are not — because the misidentification goes in both directions.
They are not character flaws. The freeze person is not weak. The fawn person is not a pushover. The flight person is not shallow or commitment-avoidant. These are nervous system strategies that were adaptive in the context in which they were learned. The problem is not that they exist — it’s that they keep running past the context that required them.
They are not destiny. The research on trauma treatment, including the work on nervous system regulation drawn from polyvagal theory and applied through somatic therapies, EMDR, and trauma-focused CBT, consistently demonstrates that the nervous system can update. A window of tolerance that has been narrowed by chronic threat can, with appropriate support, be widened. The brain that learned to respond in a certain way can also learn to respond differently.
They are not the same as PTSD. Trauma responses are broader than a PTSD diagnosis. You can carry chronic fight, flight, freeze, or fawn patterns without meeting the clinical criteria for PTSD or complex PTSD — two related but clinically distinct conditions. The absence of a diagnosis doesn’t make the patterns less real, less significant, or less worth addressing.
A Starting Point, Not an Endpoint

Recognising a trauma response in yourself is genuinely useful information. It reframes what might have felt like a personality failing as an adaptive strategy — one that made sense in its original context and has simply not had the opportunity to update.
That reframe alone, while not a treatment, is often where change begins. As the clinical consensus in trauma psychology consistently reflects: you cannot work with something you cannot name.
If these patterns feel strongly familiar, and especially if they’re affecting your relationships, your work, or your sense of who you are, speaking with a trauma-informed therapist is the most effective next step. Trauma-focused approaches including EMDR, Somatic Experiencing, and trauma-focused CBT are all backed by a growing evidence base for helping the nervous system build new responses alongside the old ones — rather than trying to simply override or suppress what it learned.
Frequently Asked Questions
Can you have trauma responses without remembering a specific traumatic event?
Yes. Not all trauma is single-incident or clearly memorable. Chronic low-level threat — growing up in an unpredictable household, prolonged emotional neglect, years in a difficult relationship — can shape the nervous system’s stress response without producing a single defining memory. Research on non-associative fear learning shows that the nervous system can become generally more reactive after prolonged stress, independent of any specific traceable incident. The absence of a clear “traumatic event” doesn’t mean trauma responses aren’t present.
Is the fawn response a real trauma response?
Yes. While fight, flight, and freeze have longer clinical histories, the fawn response — the pattern of appeasing and accommodating to manage threat — is recognised in clinical practice and trauma-informed therapy frameworks. It is most associated with relational and childhood trauma, where the threat was a caregiver and direct confrontation or escape carried its own risks. Pete Walker formally named it in his 2013 clinical work on complex PTSD.
How is a trauma response different from just having a strong personality?
The most useful distinguishing question is: does the response arrive faster than your conscious assessment of the situation, and does it run regardless of what the situation actually calls for? Personality traits are generally flexible and context-responsive. Trauma responses tend to be more rigid — the same pattern running across different situations and relationships, often with a felt sense that the body reacted before the thinking mind had a chance to weigh in.
Can trauma responses get worse over time without treatment?
They can become more entrenched. Without intervention, the nervous system continues to consolidate the patterns it knows — which means responses that were adaptive in childhood can become increasingly automatic and generalised in adulthood. They can also be reactivated or worsened by new stressors or experiences that resemble the original threatening context. This is why the ACE study found a graded relationship: more adverse experiences in childhood corresponded to greater adult difficulties, not because the events themselves grew, but because the nervous system’s accumulated adaptations compounded.
Is it possible to run different trauma responses in different relationships?
Yes, and it’s common. Research on complex trauma and attachment finds that the nervous system learns which strategy was most effective in each specific relational context and deploys accordingly. You may fawn with one family member, freeze with a particular colleague, and fight with a romantic partner — all as context-specific adaptations to the threat landscape as your nervous system originally mapped it.
What’s the difference between a trauma response and anxiety?
They overlap significantly, and anxiety often co-occurs with trauma responses. Flight and fight responses both involve sympathetic nervous system activation that resembles or produces anxiety symptoms. Freeze can resemble depression or dissociation. The distinction that trauma-informed clinicians often draw is that anxiety refers to the emotional experience of anticipated threat, while a trauma response refers to the specific automatic nervous system strategy deployed in response to perceived threat — with or without the subjective experience of fear. In practice, a person can be experiencing both simultaneously.
Sources & References
- Cannon WB. Bodily Changes in Pain, Hunger, Fear and Rage: An Account of Recent Researches into the Function of Emotional Excitement. D. Appleton and Company, 1915. Historical foundational work establishing the fight-or-flight response.
- Kozlowska K, Walker P, McLean L, Carrive P. “Fear and the defense cascade: clinical implications and management.” Harvard Review of Psychiatry, 23(4):263–287, 2015. doi:10.1097/HRP.0000000000000065. pubmed.ncbi.nlm.nih.gov/26062812
- Siegel DJ. The Developing Mind: Toward a Neurobiology of Interpersonal Experience. Guilford Press, 1999. Foundational text introducing the window of tolerance concept.
- Corrigan FM, Fisher J, Nutt D. “Autonomic dysregulation and the Window of Tolerance model of the effects of complex emotional trauma.” Journal of Psychopharmacology, 25(1):17–25, 2011. doi:10.1177/0269881109354930. PMID: 20093318. pubmed.ncbi.nlm.nih.gov/20093318
- Porges SW. The Polyvagal Theory: Neurophysiological Foundations of Emotions, Attachment, Communication, and Self-regulation. W.W. Norton and Company, 2011.
- Infurna FJ, Rivers CT, Reich J, Zautra AJ. “Childhood trauma and personal mastery: their influence on emotional reactivity to everyday events in a community sample of middle-aged adults.” PLOS ONE, 10(4):e0121840, 2015. doi:10.1371/journal.pone.0121840. ncbi.nlm.nih.gov/pmc/articles/PMC4388499
- Felitti VJ, Anda RF, Nordenberg D, et al. “Relationship of childhood abuse and household dysfunction to many of the leading causes of death in adults: The Adverse Childhood Experiences (ACE) Study.” American Journal of Preventive Medicine, 14(4):245–258, 1998. doi:10.1016/S0749-3797(98)00017-8. pubmed.ncbi.nlm.nih.gov/9635069
- Herman JL. Trauma and Recovery: The Aftermath of Violence — From Domestic Abuse to Political Terror. Basic Books, 1992. Original clinical formulation of complex trauma and relational trauma responses.
- Psychology Tools. “Window of Tolerance — Clinical Reference Guide.” psychologytools.com/resource/window-of-tolerance
- Main M, Hesse E. “Parents’ unresolved traumatic experiences are related to infant disorganized attachment status.” In Greenberg MT, Cicchetti D, Cummings EM (eds). Attachment in the Preschool Years: Theory, Research, and Intervention. University of Chicago Press, 1990.
- Walker P. Complex PTSD: From Surviving to Thriving. Azure Coyote Publishing, 2013. Clinical reference for the fawn response in complex trauma contexts.
- Cloitre M, et al. “A ISTSS expert consensus treatment guidelines for complex PTSD in adults.” ISTSS, 2012. istss.org/ISTSS_Main/media/Documents/ISTSS-Expert-Concesnsus-Guidelines-for-Complex-PTSD-Updated-060315.pdf
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If you are in crisis, please contact a mental health crisis helpline or your local emergency services immediately.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. A list of signs cannot diagnose depression. If you recognise yourself in this article, please use it as a starting point for a conversation with a qualified healthcare professional — not as a conclusion.
You get things done. You show up for work, meet your deadlines, maintain your friendships, and look — to everyone around you — like someone who has it together. But underneath all of that, something feels off in a way you can’t quite explain. Not dramatically, not visibly. Just a persistent, low-grade flatness. A sense that you’re going through the motions rather than actually living them.
If that resonates, you may be experiencing what’s commonly called high-functioning depression.
Here’s the first thing you need to know: that term doesn’t appear in any clinical manual. High-functioning depression is not a formal diagnosis in the DSM-5 or the ICD-11. What it describes — and describes accurately — is a real, recognisable presentation that does have clinical names. Understanding those names, and what they actually mean, is the key to getting help for something that too many people spend years dismissing as a personality quirk, an attitude problem, or simply “just how I am.”
What “High-Functioning Depression” Actually Is Clinically

The term high-functioning depression entered clinical discourse in the late twentieth century as an informal descriptor — useful, descriptive, and widely resonant, but not a diagnostic category in its own right.
A 2025 peer-reviewed study published in Cureus (NCBI/PMC) by Joseph and colleagues, which characterised the clinical correlates of high-functioning depression in 120 adult participants aged 18–75, defined it as: experiencing depressive symptoms — fatigue, anhedonia, poor concentration, guilt, restlessness, sleep disturbances, and appetite changes — without experiencing a significant lack of functioning or overt distress. The study found that 60% of participants demonstrated high-functioning depression and 14% demonstrated what the researchers described as “very” high-functioning depression. The same study identified a strong association between high-functioning depression and anhedonia — the inability to feel pleasure — with anhedonia scores significantly predicting overall high-functioning depression severity.
Clinically, the presentation maps most directly onto two diagnostic categories:
Persistent Depressive Disorder (PDD): The DSM-5-TR definition, updated in 2022, describes PDD as a depressed mood occurring for most of the day, more days than not, for at least two years in adults, with symptoms never absent for more than two consecutive months during that period. According to StatPearls (NCBI Bookshelf, updated August 2024), PDD was introduced in DSM-5 to consolidate what were previously two separate diagnoses: chronic major depressive disorder and dysthymic disorder (dysthymia). The DSM-5-TR notes a particularly important clinical observation: because the symptoms become part of the individual’s day-to-day experience, especially in early-onset cases, they may not be reported unless the person is specifically prompted — because the person has often concluded that this is simply how they feel, permanently.
Major Depressive Disorder with maintained functioning: Some people experience full major depressive episodes — meeting the clinical threshold for MDD — without the visible functional collapse that the popular image of depression associates with the condition. They continue working, maintaining relationships, and meeting obligations, while internally experiencing symptoms that fully meet MDD criteria.
Double depression: A third pattern exists where episodes of major depression are superimposed on an underlying PDD — meaning the person carries the chronic low mood of PDD as a baseline, with acute depressive episodes layered on top. Research suggests this combination is common and associated with more significant impairment than either condition alone.
The 12-month prevalence of PDD in the United States is estimated at approximately 1.5–2% of adults, with substantial underdiagnosis precisely because people with this presentation continue to function. According to the National Institute of Mental Health (NIMH), the lifetime prevalence of persistent depressive disorder is 3.6% among US adults.
Why It Stays Hidden — From Others and From You

The invisibility of high-functioning depression is not accidental. It’s structural.
The first layer is external: people with this presentation look fine. They go to work. They smile. They make plans. Nothing in their visible behavior signals distress. This means the people around them — partners, friends, colleagues — have no reliable cue to offer help or ask questions. The person dealing with it rarely receives the social recognition that often comes with more visible forms of mental illness.
The second layer is internal, and it’s harder to navigate. According to the 2025 Joseph et al. study in Cureus, individuals with high-functioning depression often identify strongly with their productivity and capability. Their functioning isn’t just a mask — it’s also a core part of how they understand themselves. Acknowledging depression feels, to many of them, like admitting that the competent, reliable self they’ve presented to the world is false. This creates a powerful psychological barrier to self-recognition.
The DSM-5-TR notes this directly in its description of PDD: the symptoms become so integrated into daily experience, particularly in early-onset cases, that people are often unable to distinguish them from their baseline personality. Chronic low mood that has been present since adolescence doesn’t feel like a condition. It feels like a character trait. “I’ve always been this way” is one of the most common things clinicians hear from people who have had unrecognised PDD for years or decades.
The third layer is the productivity trap. High-functioning depression often coexists with overwork. The busyness is not coincidental — it serves a function. Staying perpetually occupied means less time sitting with the flatness, the emptiness, or the vague sense that something is wrong. Work becomes both a coping mechanism and a proof of adequacy. “I can’t be depressed — look how much I’m getting done.”
Signs of High-Functioning Depression: What to Actually Look For

Most articles on this topic list symptoms that overlap heavily with any depression list. The signs below are specifically framed around the high-functioning presentation — how these symptoms appear when someone is maintaining daily life on the outside while experiencing them on the inside.
You’ve lost enjoyment without losing activity. You still attend social events, pursue hobbies, and keep up your commitments. But the internal experience of those things has changed. You go through the motions because you know you should, not because you genuinely want to. Activities that once felt restorative now feel like obligations. This is anhedonia — the hallmark feature of depression that is most often missed in high-functioning presentations because the person is still showing up. As the 2025 Joseph et al. study found, anhedonia is the strongest predictor of high-functioning depression severity, and it is consistently under-recognised precisely because its outward signal — continued participation — looks like wellness.
Your baseline mood has quietly shifted. Not sadness, exactly. More like a persistent flatness — a grey undertone to daily experience that has been there so long you’ve stopped noticing it distinctly. The DSM-5 notes that in PDD, people often describe feeling as though they’ve “always been this way,” which makes the mood shift almost impossible to detect from the inside. The person who has been mildly depressed for six years doesn’t experience it as six years of depression. They experience it as just how they are.
You feel it physically before you name it emotionally. Fatigue that sleep doesn’t fix. Persistent low energy that makes even simple tasks feel heavier than they should. Unexplained aches, tension, or digestive issues that doctors haven’t found a clear cause for. Depression has well-documented somatic features — physical symptoms that appear without an obvious organic cause — and in high-functioning presentations, these physical signals sometimes arrive before the person has identified anything as depression.
Irritability is the emotion that shows. Because the internal flatness rarely displays outwardly as visible sadness, the emotion that leaks through most often is irritability. A shorter fuse. Disproportionate frustration at small inconveniences. A hair-trigger reaction to interruptions or plans changing. This is especially common in the PDD presentation and is one of the features clinicians look for when the person hasn’t presented with “I feel depressed.”
You’re always almost okay. Not in crisis. Not falling apart. Just not quite right. There’s a sense of functioning slightly below your own capacity — a persistent gap between the life you’re maintaining and a fuller, more alive version of yourself that feels out of reach without a clear reason why. This “almost okay” quality is one of the harder things to bring to a clinician because it doesn’t feel urgent enough to warrant attention.
Perfectionism has become a coping mechanism. Many people with high-functioning depression develop perfectionist patterns — overchecking work, compulsive productivity, difficulty delegating — as a way of managing the internal feeling of inadequacy and keeping the external picture impeccable. The busyness holds the flatness at bay and provides evidence against the internal critic. According to Rolling Out‘s clinical coverage, perfectionist tendencies as a masking strategy are one of the more consistent patterns observed in this presentation.
Sleep is consistently disrupted at one end or the other. Either difficulty getting to sleep or staying there — often accompanied by a restless, overactive mind at night — or sleeping significantly more than needed, using sleep as an escape from a waking experience that feels flat and effortful. The DSM-5-TR criteria for PDD include sleep disturbance as one of its core associated features.
You rely on something to get through the end of the day. Alcohol, food, social media scrolling, compulsive online shopping, binge-watching — not in a catastrophic way, but as a reliable nightly ritual of numbing. The pattern often doesn’t feel like a problem from the inside because the quantities are manageable. It’s the function it serves — consistent emotional escape at the end of a long day of performing normality — that is the signal worth paying attention to.
You find yourself thinking “what’s the point” without any drama. Not suicidal ideation. More like a passive, low-grade pessimism — a background belief that things probably won’t get significantly better, that effort doesn’t really change outcomes, that the future is a flatter version of now. This kind of passive hopelessness is one of the most clinically significant features of chronic depression and one of the least dramatised, because it doesn’t announce itself. It just quietly colours how decisions get made.
High-Functioning Depression vs. Burnout: An Important Distinction
These two conditions overlap in symptom presentation and are frequently confused — including by the people experiencing them.
Both involve fatigue, reduced motivation, difficulty concentrating, emotional detachment, and declining enjoyment of previously satisfying work. The surface presentation can be nearly identical.
The key distinction, supported by clinical literature, is the relationship between the symptoms and work or external stressors.
Burnout is context-specific and recovers with rest. The symptoms are directly tied to occupational overload, and meaningful improvement follows removal from the stressor — a long break, a job change, a significant reduction in demands. The mood and energy recover when the context changes.
High-functioning depression doesn’t resolve when external conditions improve. A person with PDD or masked MDD can take a holiday, change jobs, or significantly reduce their workload and find that the flatness, the fatigue, and the loss of enjoyment remain. The symptoms are internal and persistent, not reactive to circumstance. This is the most reliable distinguishing question: if the stressor were removed tomorrow, would the feeling lift? With burnout, probably yes. With depression, probably not.
A 2025 study published in Cureus by Joseph et al. noted explicitly that symptoms typically associated with burnout — depleted energy and the inability to maintain relationships effectively — are not typically experienced or reported by individuals with high-functioning depression, who specifically maintain these capacities outwardly. The presentations share features but are not the same condition, and they don’t respond to the same interventions.
The Double Depression Risk Nobody Talks About

One pattern worth understanding is double depression — a term used clinically to describe major depressive episodes superimposed on an underlying persistent depressive disorder.
In practical terms: someone with PDD is already carrying a below-the-waterline mood baseline. When a major depressive episode develops on top of that baseline, it represents a significant worsening — but because their starting point was already depressed, neither the person nor those around them necessarily registers the acute episode as a departure from normal. The person has been “a bit flat” for years. This period feels worse, but not dramatically so.
According to StatPearls (NCBI, 2024), PDD often has an early and insidious onset in childhood, adolescence, or early adulthood, and is less likely to fully resolve compared to a major depressive disorder episode. The presence of comorbid anxiety disorders leads to significantly worse long-term outcomes. Research also indicates that people with PDD have higher rates of first-degree relatives with persistent depressive disorder than do people with MDD alone, suggesting a familial component to the chronic presentation.
What Treatment Looks Like for This Presentation

High-functioning depression is treatable. The clinical picture for PDD and related presentations is not hopeless — it’s just slower and requires different expectations than an acute depressive episode.
According to Cleveland Clinic (reviewed September 2024), the most effective treatment for persistent depressive disorder combines medication, psychotherapy, and lifestyle changes, rather than any single approach alone.
Psychotherapy: Cognitive Behavioural Therapy (CBT) is the most widely studied psychological intervention for depression generally. A 2024 systematic review published in Frontiers in Psychiatry found that adding CBT to antidepressant medication more than doubled response rates in patients with treatment-resistant depression, over three-quarters of whom had a chronic depressive episode at baseline.
A therapy specifically designed for chronic depression — the Cognitive Behavioral Analysis System of Psychotherapy (CBASP) — is recommended as first-line psychotherapeutic treatment for PDD in several national and international clinical guidelines, including the European Psychiatric Association. CBASP was developed specifically for the interpersonal patterns and chronic course that characterise PDD. According to a 2021 editorial published in Frontiers in Psychiatry, CBASP is particularly effective for patients with early-onset PDD, significant comorbidity, and a history of trauma.
Medication: Antidepressants, particularly SSRIs and SNRIs, are effective for PDD and are often recommended in combination with psychotherapy rather than as standalone treatment. StatPearls (NCBI, 2024) notes that response to medication is observed, but that the evidence base for medication in PDD specifically is smaller than for MDD, and that combination treatment generally produces better outcomes than medication or therapy alone.
What recovery looks like in practice: For PDD in particular, improvement tends to be gradual rather than dramatic. The goal is not a sudden lifting of mood but a slow broadening of emotional range, increasing energy, and the return of genuine enjoyment in daily activities. Many people describe it less as feeling better and more as noticing, eventually, that the grey undertone has lightened.
Frequently Asked Questions
Is high-functioning depression a real diagnosis?
The term itself is not a formal diagnosis in the DSM-5 or ICD-11. It’s a widely used descriptor for presentations that map clinically onto Persistent Depressive Disorder (PDD), Major Depressive Disorder with maintained functioning, or double depression. A 2025 peer-reviewed study in Cureus formally characterised its clinical correlates, which is a meaningful step toward clinical recognition, but it remains diagnostically informal. A mental health professional evaluating you will use the formal categories when diagnosing.
Can you have high-functioning depression and not feel sad?
Yes. Sadness is not a required feature of the presentation. Anhedonia — the loss of pleasure and interest in things that previously brought enjoyment — is often the more prominent feature, and it can exist without visible or even internally experienced sadness. Irritability, fatigue, and emotional numbness are frequently more prominent than overt low mood.
How long does high-functioning depression typically last?
Research cited by Bridges to Recovery indicates that adults with high-functioning depression experience symptoms for an average of five years. PDD, by definition, requires at least two years of symptoms for diagnosis. Left untreated, the chronic course of PDD means it can persist for a decade or longer.
Could it be burnout instead?
It could be either, or both. The distinguishing question is whether symptoms persist independently of external stressors and don’t resolve meaningfully with rest. Burnout improves when the occupational overload is removed. Depression typically doesn’t. If you’ve had sustained periods of rest and the flatness remains, that’s worth bringing to a professional.
Can someone with high-functioning depression get worse suddenly?
Yes. The double depression pattern — where a major depressive episode develops on top of an existing PDD baseline — is a recognised risk. Because the person is already used to functioning with a depressed baseline, they may not immediately identify the worsening as a clinical escalation. This is one reason prompt evaluation is important rather than waiting to see if it resolves on its own.
Sources & References
- Joseph JF, Tural U, Joseph ND, et al. “Understanding High-Functioning Depression in Adults.” Cureus, 17(2): e78891, 2025. doi:10.7759/cureus.78891. ncbi.nlm.nih.gov/pmc/articles/PMC11831407
- Patel RK, Rose GM. “Persistent Depressive Disorder.” StatPearls [Internet]. NCBI Bookshelf. Updated August 2024. ncbi.nlm.nih.gov/books/NBK541052
- American Psychiatric Association. “Persistent Depressive Disorder.” DSM-5-TR Update Bulletin, 2022. APA Publishing. psychiatry.org/getmedia/fd3dfaad
- National Institute of Mental Health (NIMH). “Persistent Depressive Disorder (Dysthymic Disorder): Statistics.” U.S. Department of Health and Human Services. nimh.nih.gov/health/statistics/persistent-depressive-disorder-dysthymic-disorder
- Cleveland Clinic. “Persistent Depressive Disorder (PDD): Symptoms and Treatment.” Reviewed September 2024. my.clevelandclinic.org/health/diseases/9292-persistent-depressive-disorder-pdd
- Wiersma J, Klein P, Schramm E, Furukawa T, Favorite T. “Editorial: CBASP in the Treatment of Persistent Depressive Disorder.” Frontiers in Psychiatry, 2021. doi:10.3389/fpsyt.2021.804602. ncbi.nlm.nih.gov/pmc/articles/PMC8716920
- Voderholzer U, et al. “Enduring effects of psychotherapy, antidepressants and their combination for depression: a systematic review and meta-analysis.” Frontiers in Psychiatry, 2024. doi:10.3389/fpsyt.2024.1415905. ncbi.nlm.nih.gov/pmc/articles/PMC11632389
- Open University. “Exploring Depression: The Diagnosis of Depression.” OpenLearn. open.edu/openlearn/science-maths-technology/exploring-depression
- Bridges to Recovery. “High-Functioning Depression.” bridgestorecovery.com/high-functioning-depression
- Olanrewaju J, et al. “High-functioning depression: a hidden burden demanding clinical recognition.” ResearchGate, 2025. researchgate.net/publication/388925250
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If you are in crisis or experiencing thoughts of self-harm, please contact a mental health crisis helpline or your local emergency services immediately.


From Leaky Gut to Resilience: The Beta Glucan Breakthrough

Chamomile Tea for Sleep: How Much to Drink (And When)

Instant Relief for Trapped Gas Pain: Why Direction Matters More Than the Pose

PEMF Webinar

Why You Can’t Trust Big Pharma

The Anti-Cancer Body with Dr. Michael Karlfeldt
-
 Events2 months ago
PEMF Webinar
-
 Events3 months ago
Why You Can’t Trust Big Pharma
-
 Events4 months ago
The Anti-Cancer Body with Dr. Michael Karlfeldt
-

 Events3 months ago
The Cancer Conversation Your Oncologist Cannot Have in 15 Minutes
-

 Natural Sleep Remedies4 months ago
The 4-7-8 Breathing Technique: Step-by-Step Guide and What the Research Actually Shows
-

 Events5 months ago
Beyond the Brain
-

 Events4 weeks ago
HBOT ( Hyperbaric Oxygen Therapy ) Webinar
-

 Gut Health3 months ago
Unlock Incredible Gut Health Hacks and Transform Your Well-being Today!