
Mental Health
Natural Remedies for ADHD: What the Evidence Actually Says

The content on this website – including articles, event announcements, personal experiences, and recommendations – is for informational and educational purposes only and is not medical advice. Always consult a qualified healthcare professional before making any changes to your diet, exercise, supplements, sleep habits, or wellness routines, especially if you are pregnant, nursing, on medication, or have any medical condition.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. ADHD is a clinically diagnosed neurodevelopmental condition. The approaches covered here are evidence-based lifestyle and complementary strategies — they are not substitutes for professional evaluation, diagnosis, or treatment. If you or your child have ADHD, please work with a qualified healthcare professional before making changes to any treatment plan.
If you search “natural remedies for ADHD,” you will find a spectrum of content — everything from rigorous clinical research to frankly implausible claims involving essential oils and herbal supplements that have no meaningful evidence behind them. The gap between those two ends of the spectrum is enormous, and for anyone managing ADHD or supporting someone who does, that gap matters.
This article cuts through the noise. It covers what actually has research behind it, what the evidence says specifically (not just “this may help”), what the evidence doesn’t support, and how these approaches fit alongside — not instead of — the clinical care that ADHD requires.
Key Takeaways
- ADHD is a neurodevelopmental condition with established, evidence-based treatments. The lifestyle approaches covered here are adjuncts — they can meaningfully support symptom management, but they are not replacements for professional diagnosis or treatment.
- Exercise has the strongest non-pharmacological evidence base. A 2025 meta-analysis found medium effect sizes for inhibitory control and working memory in children with ADHD. The mechanism is real: aerobic exercise raises dopamine and norepinephrine — the same neurotransmitters targeted by ADHD medication, via a different route.
- Omega-3 supplementation shows the most benefit in people who are actually deficient. A 2026 meta-analysis found that children with low baseline omega-3 levels showed moderate symptom improvement; those with normal or high levels showed no measurable benefit. Getting tested before supplementing makes sense.
- Mindfulness-based interventions show promising results in adults particularly — reduced inattention, improved executive function, better emotional regulation — but research quality is still generally poor and clinical recommendations for children are premature.
- Sleep is a critical but underappreciated lever. The relationship between ADHD and sleep is bidirectional: ADHD disrupts sleep, and poor sleep reliably worsens ADHD symptoms. Improving sleep hygiene is one of the highest-impact things you can do regardless of anything else.
- Essential oils, most herbal supplements (ginkgo biloba, St. John’s wort), and CBD oil do not have meaningful clinical evidence for ADHD symptom management. Including them in this article without noting that would be a disservice.
- If you are currently on ADHD medication, do not adjust or stop it based on anything in this article. Talk to your prescribing doctor.
First: What “Natural” Should and Shouldn’t Mean Here
The word “natural” in the context of health content can mean almost anything. For the purposes of this article, it means: non-pharmacological, lifestyle-based, or supplementary approaches with peer-reviewed research examining their effect on ADHD symptoms.
That definition excludes things with no research. It also means being honest about effect sizes — a “statistically significant improvement” in a clinical trial does not always mean “this will transform daily life.” The interventions below are genuinely useful, particularly in combination. They tend to be most effective when layered on top of a care plan that includes professional support, not in place of one.
ADHD — formally Attention-Deficit/Hyperactivity Disorder — is diagnosed according to DSM-5 criteria and affects an estimated 8.4% of children and 2.5% of adults in the US, according to the American Psychiatric Association. If you are still at the stage of wondering whether what you are experiencing is ADHD, our article on adult ADHD symptoms in women walks through the clinical picture in detail.
1. Exercise: The Strongest Non-Pharmacological Evidence

If there is one lifestyle intervention backed by consistent, mechanistically plausible research for ADHD, it is aerobic exercise. And the reason it works is not mysterious: it operates through the same neurochemical pathways that ADHD medication targets.
ADHD involves dysregulation of dopamine and norepinephrine in the prefrontal cortex — the brain region responsible for executive function, working memory, attention regulation, and impulse control. Stimulant medications (methylphenidate, amphetamines) work primarily by increasing the availability of these neurotransmitters. Aerobic exercise does the same thing — through a different mechanism, at a lower magnitude, but through the same fundamental pathway.
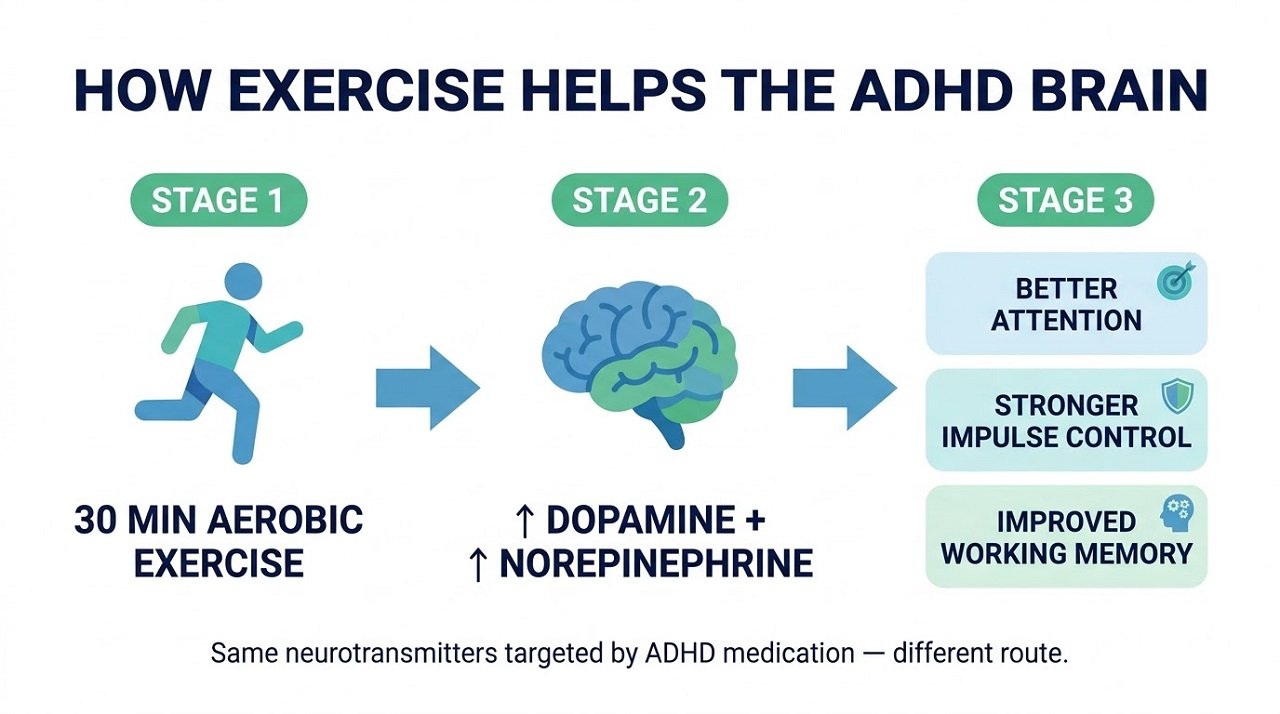
A 2025 meta-analysis published in BMC Public Health (Liu et al.), pooling randomised controlled trials of school-age children with ADHD, found:
- Medium effect sizes for inhibitory control under both positive and reverse scoring
- Medium effect sizes for working memory under both scoring methods
- Small to medium effect sizes for cognitive flexibility, significant under reverse scoring
The FITKids randomised controlled trial, published in Pediatrics, found that approximately 30 minutes of daily aerobic activity improved mood and reduced ADHD symptoms in children. Studies in adults, while fewer, also point toward improvements in motivation, impulse control, and emotional symptoms.
What type of exercise? The research covers aerobic exercise most extensively — running, cycling, swimming, dancing — but emerging evidence suggests that activities combining physical and cognitive demands (martial arts, team sports, gymnastics) may offer additional benefits by engaging the prefrontal cortex more directly. Even a brisk 20–30 minute walk appears to produce acute improvements in attention that last several hours afterward.
Practically: Exercise is not a replacement for medication or behavioural therapy. It is, however, one of the most accessible, side-effect-free, and well-evidenced tools available. Building consistent daily movement into the routine — particularly aerobic activity — is one of the most useful things anyone with ADHD can do.
2. Sleep: The Lever Most People Underestimate

The relationship between ADHD and sleep is one of the most important and least-discussed aspects of managing the condition day to day.
Research consistently shows that sleep difficulties are significantly more common in people with ADHD than in the general population — with estimates suggesting that up to 70-80% of children with ADHD experience some form of sleep disturbance. The problems include difficulty falling asleep (delayed sleep phase is particularly common), restless sleep, difficulty waking, and daytime drowsiness.
The relationship is bidirectional and self-reinforcing: ADHD symptoms — including an overactive mind, difficulty winding down, and hyperfocus on evening activities — make sleep harder. And poor sleep reliably worsens ADHD symptoms the following day: attention, working memory, impulse control, and emotional regulation all deteriorate significantly with sleep loss. The result is a cycle that, left unaddressed, keeps both sleep and ADHD symptoms at their worst.
“The physiological stress this cycle places on the body — and how chronic sleep disruption affects multiple body systems — is covered in detail in our article on physical symptoms of stress and anxiety.”
Importantly, sleep deprivation can also cause or worsen symptoms that look like ADHD in both children and adults — meaning that poor sleep hygiene may sometimes be misread as ADHD severity when it is actually a primary contributor. Improving sleep is therefore both a treatment target in its own right and a tool for getting a clearer picture of underlying ADHD.
Practical sleep hygiene for ADHD:
- Consistent sleep and wake times — including weekends, which is particularly hard for people with ADHD but particularly important
- A screen-free wind-down window of at least 30–60 minutes before bed; blue light and dopaminergic screen content (social media, gaming) are especially activating for ADHD brains
- A predictable pre-bed routine to signal transition; ADHD brains often struggle with self-initiated transitions, and an external routine reduces the cognitive load of that shift
- Melatonin may help with sleep onset specifically (the evidence for this is reasonable) but has no documented effect on ADHD symptoms themselves; it is a sleep aid, not an ADHD intervention
For more on what helps when the mind won’t settle at night, our article on how to stop overthinking before bed covers evidence-based techniques in detail.
3. Omega-3 Fatty Acids: Useful — But Only for Some

Omega-3 supplementation is one of the most researched nutritional interventions for ADHD, and the evidence is more nuanced than most summaries suggest.
A 2026 biomarker-stratified meta-analysis published in Frontiers in Public Health (Xiao Fu, Ling Feng, Mingyan Jiang, and Jinrong Li) pooled seven randomised controlled trials covering 654 children with ADHD. The key finding — and the one almost universally missing from popular coverage:
- Children with low baseline omega-3 levels showed moderate symptom improvement with supplementation (four trials, 369 children)
- Children with normal or high baseline omega-3 levels showed no measurable improvement (six trials, 559 children)
In plain terms: omega-3 supplementation appears to help people who are actually deficient. For those whose omega-3 status is already adequate, supplementation does not appear to add meaningful benefit for ADHD symptoms.
This matters practically. Rather than simply starting omega-3 supplements because you have read they might help, it makes sense to have omega-3 status checked first — either through a healthcare provider or a home test. If deficiency is present, supplementation becomes a meaningfully supported intervention. If levels are adequate, the money and effort are better spent elsewhere.
The researchers note caveats worth flagging: the evidence rests on only seven trials, baseline omega-3 was defined differently across studies, and some subgroup comparisons were post-hoc. The authors describe their findings as hypothesis-generating rather than conclusive. The evidence is promising, not settled.
Food-first approach: Oily fish (salmon, sardines, mackerel), walnuts, flaxseed, and chia seeds are dietary sources of omega-3. For those who don’t eat fish regularly, a quality EPA/DHA supplement (not ALA-only) is the form with the most direct evidence.
4. Mindfulness-Based Interventions: Promising for Adults
Mindfulness-based approaches — including Mindfulness-Based Stress Reduction (MBSR) and mindfulness-based cognitive therapy adapted for ADHD — have an emerging but carefully caveated evidence base.
A systematic review and meta-analysis by Kretschmer, Göz Tebrizcik, and Dommett (2022), pooling 22 studies across 1,237 individuals with ADHD (ages 7–65), found:
- Reduced inattentive symptoms in both adults and children
- Improved executive function in adults (less consistent in children)
- Improved emotional regulation across groups
- Better quality of life and self-compassion in adults
- Reduced anxiety and depression symptoms in adults with ADHD
The limitations are significant and the authors are explicit about them: study quality was generally poor, samples were small, randomisation and blinding were often inadequate, and high heterogeneity meant meta-analyses could not always be run. The authors conclude that better-designed trials are needed before clinical recommendations can be made — particularly for children.
For adults with ADHD specifically, the picture is more encouraging. Mindfulness practices that build present-moment awareness, slow intentional responding, and self-compassion address the impulsivity, emotional dysregulation, and self-criticism that often accompany ADHD in adults at a mechanistic level. The practice of deliberately noticing when attention has wandered and returning it — the core skill of mindfulness meditation — is essentially a training protocol for the same cognitive function ADHD disrupts.
A realistic starting point: 10–15 minutes of guided mindfulness daily (apps like Headspace or Insight Timer, or MBSR-structured programmes) over at least 8 weeks is what most research protocols use. Informal mindfulness throughout the day — paying deliberate attention during meals, during walking, during conversations — may also contribute.
5. Diet and Nutrients: What the Evidence Supports (and Doesn’t)
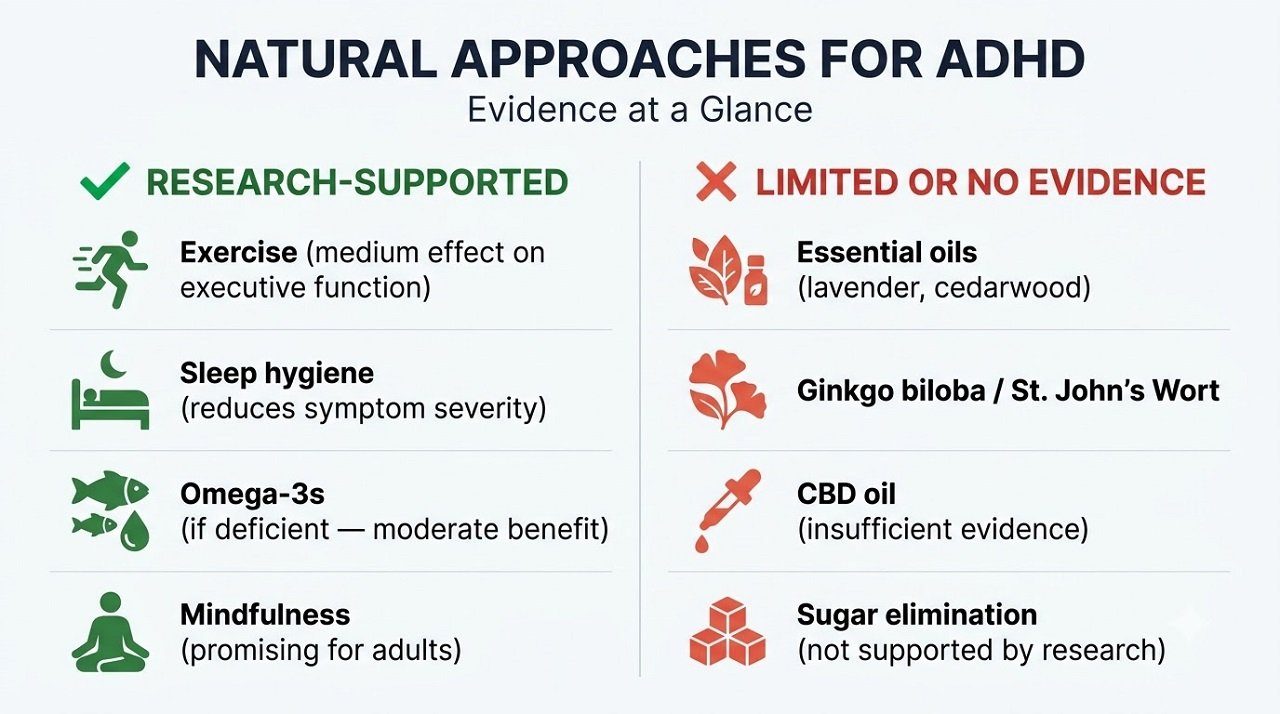
The sugar myth: Despite its persistence in popular belief, research has not shown a consistent link between sugar consumption and ADHD symptom severity. Multiple controlled studies have examined this. The perception may partly reflect the excitement loop — high-stimulation environments (like birthday parties) where sugary food appears — rather than the sugar itself.
Elimination diets: The evidence for restricting artificial food colourings (the “Feingold diet” and its variants) in children with ADHD shows some effect in a subset of children who appear sensitive to specific additives — but it is not a universal finding, the effects tend to be modest, and highly restrictive elimination diets carry their own nutritional risks in growing children. The European Food Safety Authority has flagged certain artificial food colourings as potentially worsening hyperactivity in sensitive children, which has influenced UK food labelling. If you observe consistent symptom patterns after specific foods in your child, that is worth discussing with a paediatrician.
Minerals — zinc, iron, magnesium: Research does suggest a link between deficiency in these minerals and ADHD symptom severity. A review published in Child and Adolescent Psychiatric Clinics of North America found that supplementation may help in cases of documented deficiency. The operative word is deficiency: supplementing minerals at levels already adequate does not appear to add benefit and can cause harm in some cases (iron toxicity, for example, is a real risk in children). A blood panel to check levels before supplementing is the right approach.
What to skip: Essential oils (lavender, cedarwood, vetiver), most herbal remedies (ginkgo biloba, St. John’s wort, French maritime pine bark), and CBD oil do not have meaningful clinical evidence for ADHD symptom management. St. John’s wort also has real drug interaction risks — it affects the metabolism of numerous medications including some ADHD medications. Using it without medical supervision is not advisable.
What These Approaches Can and Cannot Do
The lifestyle interventions covered above — regular aerobic exercise, good sleep hygiene, targeted supplementation based on documented deficiency, mindfulness practice — are not alternative treatments for ADHD. They are genuinely useful adjuncts that the clinical literature supports.
What they cannot reliably do is replicate the effect of appropriate pharmacological treatment in moderate to severe ADHD. Medication for ADHD — when correctly prescribed and monitored — has a well-documented evidence base and is recommended as first-line treatment for adults and many children by NICE (UK), the American Academy of Pediatrics, and the American Psychiatric Association. Lifestyle approaches work best as additions to, not replacements for, that level of care.
The question to ask is not “natural or medication” — it is “what combination of approaches gives this person the best quality of life?” For many people with ADHD, the answer involves multiple layers: professional support, possibly medication, and the kind of consistent lifestyle foundations covered here.
When to Seek Professional Help
If ADHD has not been formally assessed, start there. The lifestyle approaches in this article may help with attention, mood, and energy regardless of ADHD diagnosis — but accurate diagnosis shapes what kind of support is most appropriate.
Seek professional support promptly if:
- ADHD symptoms are significantly affecting school, work, or relationships
- There are co-occurring symptoms of anxiety or depression (common in ADHD)
- Sleep difficulties are severe or persistent despite good sleep hygiene
- A child is falling behind academically or showing distress
ADHD often co-occurs with anxiety, depression, and learning differences — including conditions like complex PTSD, whose overlap with ADHD presentations can complicate diagnosis. A thorough professional assessment is the foundation everything else builds on.
Frequently Asked Questions
Can ADHD be managed without medication?
Some people with mild to moderate ADHD manage effectively with a combination of behavioural strategies, lifestyle modifications, and appropriate support — without medication. Others find that medication is necessary to reach a functional baseline on which everything else can build. The decision is individual and should involve a clinician who knows the full picture. What the research does not support is the idea that lifestyle changes alone are reliably equivalent to medication for moderate to severe ADHD.
Do omega-3 supplements help with ADHD in adults?
Most of the omega-3 research has been conducted in children. The 2026 meta-analysis (Fu et al., Frontiers in Public Health) covered paediatric populations specifically. Adult data is limited. The same logic applies — if omega-3 levels are low, supplementation may be beneficial; if levels are already adequate, the evidence for additional benefit is thin.
Is exercise as effective as medication for ADHD?
No — the effect sizes for exercise, while meaningful, are smaller than those documented for stimulant medication. Exercise is an important adjunct with strong supporting evidence, particularly for executive function and mood. It is not a clinical equivalent of medication for most people with ADHD. The framing of “exercise versus medication” is a false binary; for many people, both are part of an effective approach.
Can diet cause ADHD?
No. ADHD is a neurodevelopmental condition with strong genetic and neurological components. Diet does not cause ADHD. Some dietary factors — particularly omega-3 deficiency and deficiency of certain minerals — may worsen symptoms, and improving these may modestly reduce symptom severity. That is a different claim from diet being a cause.
How long does it take to see results from lifestyle changes?
Exercise can produce acute improvements in attention within a single session, with cumulative gains building over weeks of consistent practice. Sleep improvements typically produce noticeable symptom benefits within days of consistent better sleep. Omega-3 supplementation, in those who are deficient, typically shows effects over 4–12 weeks. Mindfulness effects in research studies build over 8-week protocols. None of these are overnight changes — consistent practice over weeks to months is the realistic timeframe.
Sources & References
- American Psychiatric Association. What Is ADHD? https://www.psychiatry.org/patients-families/adhd/what-is-adhd
- Liu et al. Meta-analysis of exercise interventions and executive function in children with ADHD. BMC Public Health. 2025. Referenced at: https://adhdevidence.org/blog/meta-analysis-reports-executive-function-gains-from-exercise-interventions-for-adhd
- Fu X, Feng L, Jiang M, Li J. Baseline omega-3 nutritional status and supplementation response in pediatric ADHD: a systematic review and biomarker-stratified meta-analysis. Frontiers in Public Health. 2026. Referenced at: https://adhdevidence.org/blog/new-research-on-omega-3s-and-adhd
- Kretschmer A, Göz Tebrizcik A, Dommett EJ. Mindfulness-based interventions for ADHD: systematic review and meta-analysis. 2022. Referenced at: https://www.simplypsychology.org/?p=55616
- WebMD. ADHD natural remedies. https://www.webmd.com/add-adhd/adhd-natural-remedies
- ADDitude Magazine / ADAA. ADHD and sleep disturbances. Referenced at: https://www.betterhelp.com/advice/sleep/why-do-people-with-adhd-have-trouble-sleeping-adhd-symptoms-and-sleep-disorders
- National Institute of Mental Health (NIMH). Attention-Deficit/Hyperactivity Disorder. https://www.nimh.nih.gov/health/topics/attention-deficit-hyperactivity-disorder-adhd
This article is for informational and educational purposes only. It does not constitute medical advice and should not replace consultation with a qualified healthcare professional. ADHD diagnosis and treatment decisions should always be made in collaboration with a clinician.












Mental Health
How to Know If You Have Social Anxiety or Just Shy: The Difference That Actually Matters

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Only a qualified mental health professional can diagnose social anxiety disorder. If you recognise yourself in this article, use it as a starting point for a professional conversation, not a conclusion.
Most people have felt nervous in a social situation. Job interviews, first dates, speaking in front of a group — that discomfort is common, normal, and not what this article is about.
The question this article is about is a more persistent one: Is what I feel in social situations a personality trait I was born with — or is it a clinical condition that is quietly limiting my life?
The answer changes everything about what you should do next. Shyness doesn’t require treatment. Social anxiety disorder does — and it responds well to treatment that most people with it never seek, often because they’ve spent years telling themselves they’re just shy.
Here is how to tell the difference.
What Shyness Actually Is

Shyness is a personality trait — a normal variation in temperament, not a clinical condition. According to established personality research, shyness is categorised as a stable personality characteristic involving consistent patterns of behaviour, thought, and emotion across various social contexts. Psychological research distinguishes between two types: state shyness, a temporary response to an unfamiliar situation, and trait shyness, a long-term and stable personality characteristic.
Key features of shyness as a personality trait:
- It fades with familiarity. Shy people typically feel most uncomfortable in new or unfamiliar social situations and warm up as the situation becomes familiar. The nervousness is situationally bound and time-limited within that situation.
- It doesn’t necessarily involve fear. Shyness is characterised more by inhibition and hesitation than by intense fear. Many shy people enjoy social interactions once they feel comfortable; they are simply slower to get there.
- It doesn’t prevent functioning. A shy person may avoid going first, may hang back at parties, may take time to open up — but shyness does not typically prevent them from attending, from performing when required, or from maintaining meaningful relationships.
- It can improve naturally with experience. Research cited by UNSW notes that shyness may improve with age and accumulated social experience, without any clinical intervention.
Importantly, shyness is not a prerequisite for social anxiety disorder. According to the Social Anxiety Institute, only about half of people diagnosed with social anxiety disorder report having been shy. Social anxiety is about fear of judgment — it is not a personality type, and it is not exclusively the domain of introverts or quiet people. Outgoing, extroverted individuals can and do have social anxiety disorder.
What Social Anxiety Disorder Actually Is

Social anxiety disorder (SAD), also known as social phobia, is a diagnosable mental health condition listed in the DSM-5 under code 300.23. It is one of the most common anxiety disorders.
According to the DSM-5-TR, social anxiety disorder is defined as a marked fear or anxiety about one or more social situations in which the individual is exposed to possible scrutiny by others. The individual fears that they will act in a way, or show anxiety symptoms, that will be negatively evaluated — that they will be judged, humiliated, rejected, or embarrassed.
The DSM-5 diagnostic criteria require all of the following to be present:
- Marked, persistent fear or anxiety about social situations involving scrutiny
- The social situations almost always provoke fear or anxiety
- The fear or anxiety is disproportionate to the actual threat posed
- Social situations are avoided or endured with intense fear or anxiety
- The fear, anxiety, or avoidance causes clinically significant distress or impairment in social, occupational, or other important areas of functioning
- The fear, anxiety, or avoidance is persistent, typically lasting six months or more
According to NIMH data from the National Comorbidity Survey Replication, social anxiety disorder affects approximately 7% of US adults in any given year, with a lifetime prevalence of 12.1%. Women are more affected than men — the past-year prevalence is 8.0% for females versus 6.1% for males. Among adolescents, NIMH reports a lifetime prevalence of 9.1%, with females (11.2%) significantly more affected than males (7.0%).
The Merck Manual Professional Edition notes that the median age of onset is 13, with 75% of cases presenting between ages 8 and 15 — which means many adults with social anxiety disorder have been living with it since childhood, often without a diagnosis.
The Five Questions That Tell Them Apart

The distinction between shyness and social anxiety disorder, when distilled to its clinical core, comes down to five questions. Clinicians assessing for SAD are essentially asking these five things.
1. How intense is the fear, and does it arrive before the situation even starts?
Shyness: mild to moderate discomfort that tends to arrive in the moment and fade as you settle in.
Social anxiety: fear that begins well before the event. A meeting scheduled for Friday may generate significant dread from Monday onward. The anticipatory anxiety can be as debilitating as the event itself — and sometimes more so. People with social anxiety often spend weeks or even months dreading an event before it happens.
2. How long does the discomfort last after the situation ends?
Shyness: the discomfort ends when the situation does. Once you’ve left the party or the meeting, you move on.
Social anxiety: the discomfort continues afterward in the form of post-event processing — replaying the interaction in detail, cataloguing what you said that might have come across wrong, what your face did, how your voice sounded, what people must be thinking now. This rumination loop — anticipatory anxiety before, hypervigilance during, and post-event analysis after — is a defining cognitive pattern of SAD that is entirely absent from typical shyness.
3. Does the discomfort lead you to avoid situations you’d otherwise want or need to be part of?
Shyness: shy people may participate reluctantly or with some effort, but they generally participate.
Social anxiety: avoidance is one of the DSM-5 diagnostic criteria. People with SAD often turn down opportunities — professionally, socially, romantically — to avoid the feared situation. The avoidance provides temporary relief and sustains the anxiety long-term, because the feared situation is never encountered in a way that could update the fear. Each avoided situation makes the next one feel more threatening.
4. Are there physical symptoms — and do they arrive in anticipation rather than only in the moment?
Shyness: some mild physical discomfort is possible, but it is generally not intense or disabling.
Social anxiety: physical symptoms are a core clinical feature. According to research on prevalence and severity of SAD, physiological symptoms during anxiety in social situations include restlessness, stomach aches, blushing, palpitations, muscle tension, and sweating. These can appear before the situation begins — in the hallway on the way to a meeting, in the car on the way to an event — in a pattern that is closer to a full anxiety response than to ordinary social discomfort. Our article on what an anxiety attack feels like physically covers how the body activates under that kind of threat-perceived stress in detail.
5. Is the discomfort significantly affecting your functioning — your career, your relationships, your daily life?
This is the clinically decisive question. The DSM-5 requires clinically significant distress or impairment in social, occupational, or other important areas of functioning for a diagnosis of SAD. Without this criterion, the symptoms alone do not reach the diagnostic threshold.
Shyness: does not significantly interfere with functioning. A shy person may prefer smaller gatherings and take longer to open up, but their career advancement, relationship maintenance, and daily life are not substantially impaired by the discomfort.
Social anxiety: the impairment is measurable. It may show up as passing on a deserved promotion because it involves presenting, avoiding romantic relationships because the initial anxiety is unbearable, losing friendships through gradual withdrawal, underperforming academically because the classroom feels like a stage. According to Cleveland Clinic, social anxiety disorder generally doesn’t go away on its own — unlike shyness, it typically worsens without treatment.
The Rumination Loop: What Social Anxiety Looks Like From the Inside
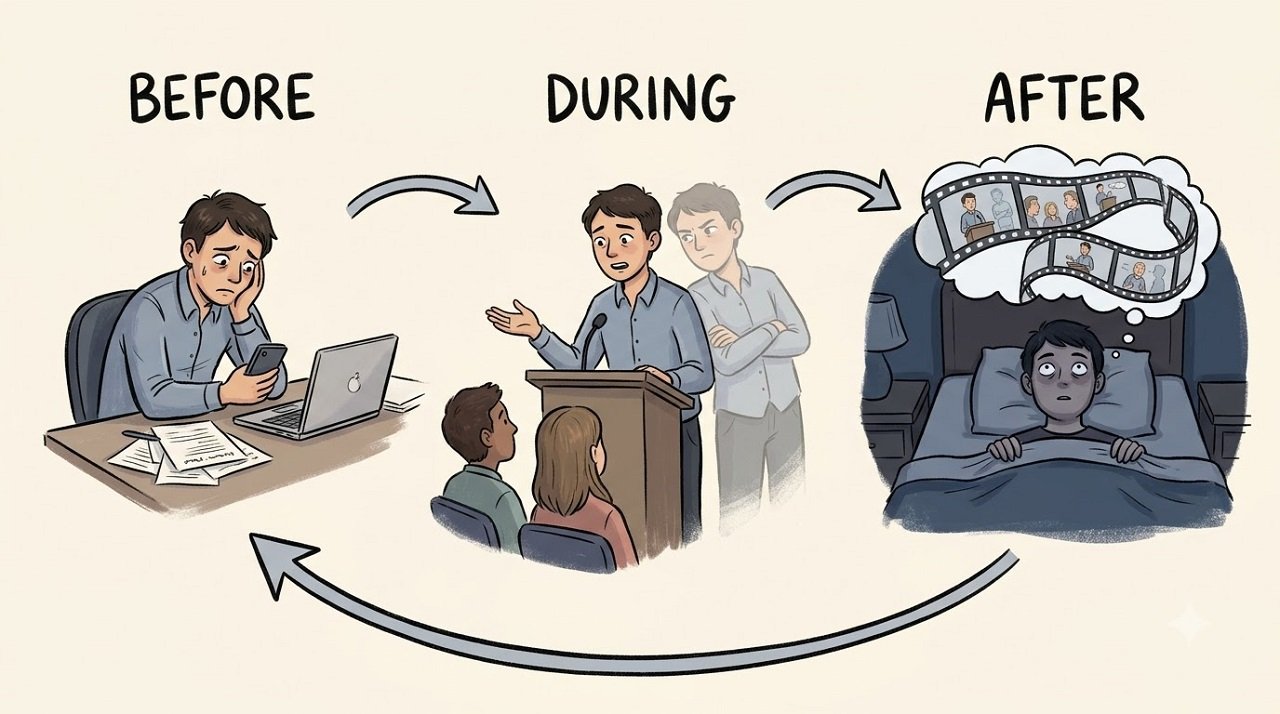
The three-phase cognitive cycle of social anxiety — anticipatory anxiety, in-situation hypervigilance, and post-event processing — is the feature most people with SAD recognise most viscerally but find hardest to name. Understanding it is one of the most useful things you can do with this information, because it distinguishes SAD clearly from anything that shyness produces.
Before: You know a social situation is coming. Rather than ordinary mild anticipation, you experience sustained dread — imagining everything that could go wrong, rehearsing what you’ll say, catastrophising about how you’ll be perceived. This can begin days or weeks in advance for significant events.
During: You are present in the situation but operating on two levels simultaneously. One part of you is participating; another part is monitoring continuously — watching yourself from the outside, assessing how you’re coming across, detecting signs that others are judging you, adjusting your behaviour in real time to manage the perceived impression. This dual processing is exhausting and interferes directly with the quality of your social interaction.
After: The situation has ended. For most people, so has the social discomfort. For someone with SAD, a new phase begins: replaying the interaction, often in detail, identifying the moments that felt wrong, inferring what people thought, feeling shame or embarrassment about things that happened or might have been perceived a certain way. This post-event processing can last hours, days, or longer.
This three-phase pattern is absent from shyness. It is a cognitive signature of social anxiety disorder, and it is one of the primary targets of CBT treatment.
You Don’t Have to Be Shy to Have Social Anxiety

This is the content gap most articles on this keyword miss entirely, and it matters enough to warrant its own section.
It is widely assumed that social anxiety is simply extreme shyness, and that quiet, introverted, or reserved people are the ones who have it. The clinical picture is more nuanced.
According to the Social Anxiety Institute, only about half of those diagnosed with social anxiety disorder report having been shy. Approximately half were not particularly shy — they were simply afraid of specific social situations in a way that was disproportionate, persistent, and impairing.
People with social anxiety disorder desire social contact and want to participate in social situations — their anxiety can become unbearable, but the desire to connect is there. This is fundamentally different from introversion (a preference for less social stimulation) or shyness (hesitation and inhibition in social situations). Outgoing people can have social anxiety. Extroverts can have social anxiety. People who appear confident can have social anxiety — particularly in the performance-only specifier.
The DSM-5 performance-only specifier is worth understanding here. Social anxiety disorder can be limited specifically to performance situations — public speaking, presentations, performing in front of an audience — without generalising to other social situations. A person who is comfortable at parties, in one-on-one conversations, and in daily social interactions but experiences debilitating fear specifically when performing or presenting may meet criteria for SAD with the performance-only specifier. This presentation is frequently missed because it doesn’t fit the stereotype of the shy, withdrawn person.
Side-By-Side Comparison
| Feature | Shyness | Social Anxiety Disorder |
|---|---|---|
| Clinical status | Personality trait — not a disorder | DSM-5 diagnosable condition (300.23) |
| Core experience | Hesitation, inhibition, discomfort | Intense fear of negative evaluation and judgment |
| Timing | Discomfort in the moment | Before, during, and after social situations |
| Physical symptoms | Mild | Often significant — palpitations, sweating, trembling, nausea |
| Avoidance | Minimal | Characteristic and progressive |
| Post-event | Ends with the situation | Rumination and post-event analysis |
| Impact on functioning | Minimal | Clinically significant distress or impairment |
| Duration | Situational | Persistent — 6 months or more by DSM-5 criteria |
| Trajectory without intervention | May improve with experience | Typically worsens |
| Requires clinical treatment | No | Yes — and responds well to it |
Does Social Anxiety Disorder Overlap With Other Conditions?
Yes, significantly — and this is one reason it stays undiagnosed. According to a PMC narrative review on SAD’s associated conditions and therapeutic approaches, social anxiety disorder commonly co-occurs with depression, other anxiety disorders, and in some cases high-functioning depression, where the social withdrawal driven by SAD can compound persistent low mood to the point where both conditions are present and interacting.
The relationship between social anxiety and trauma responses is also worth noting. The hypervigilance of the fawn response — the constant monitoring of others’ emotional states and reactions — can closely resemble the in-situation monitoring phase of social anxiety. They are distinct in origin and mechanism, but they can coexist and reinforce each other.
What Treatment Looks Like for Social Anxiety Disorder

Social anxiety disorder is highly treatable. The evidence base is stronger and more consistent than for most anxiety conditions.
A 2024 systematic review and Bayesian network meta-analysis comparing six psychotherapies across 92 studies and 90 randomised controlled trials found that cognitive behavioural therapy (CBT) is the most effective psychological intervention for SAD, recommended as first-line treatment in clinical guidelines internationally. The pooled between-group effect size for CBT was large at post-treatment.
Importantly, treatment gains from CBT for social anxiety continue to improve after therapy ends. According to Cleveland Clinic, one study found CBT for SAD reduces symptoms for 12 months or longer after therapy concludes. Research drawing on longitudinal data found that 48% of people no longer met diagnostic criteria for SAD five years after completing internet-based CBT.
A 2026 network meta-analysis published in Frontiers in Psychology comparing non-pharmacological interventions found that CBT ranked highest in effectiveness with an SUCRA value of 86.4%, ahead of combination therapy (71.7%) and psychotherapy generally (70.7%). The same review found virtual reality exposure therapy and attention training also showing beneficial effects.
Medication — primarily SSRIs and SNRIs — is used alongside CBT when symptoms are severe or when therapy alone produces partial improvement. The combination of CBT and medication generally produces better outcomes than either alone in moderate to severe presentations.
The fact that social anxiety disorder responds well to structured treatment is one of the most important pieces of information for people who have been labelling their experience as shyness for years. The discomfort isn’t a personality defect to push through. It is a clinical condition that can be substantially reduced with the right intervention.
Frequently Asked Questions
What is the key difference between being shy and having social anxiety?
Shyness is a personality trait characterised by hesitation and discomfort in social situations that fades with familiarity. Social anxiety disorder is a DSM-5 diagnosable clinical condition characterised by persistent, intense fear of negative evaluation in social situations, avoidance behaviours, physical symptoms, and clinically significant impairment in daily functioning. The critical clinical distinction is functional impairment: shyness does not significantly impair daily life; social anxiety disorder, by definition, does.
Can you have social anxiety without being shy?
Yes. According to the Social Anxiety Institute, approximately half of people diagnosed with social anxiety disorder were not particularly shy. Social anxiety is about fear of judgment and negative evaluation — it is not a personality type. Extroverted and outgoing individuals can have social anxiety disorder, particularly in the performance-only specifier.
At what age does social anxiety disorder usually start?
According to the DSM-5, the median age of onset is 13, with 75% of cases beginning between ages 8 and 15. Many adults with social anxiety disorder have been living with it since adolescence without a diagnosis, often because they attributed their experience to shyness or introversion.
Does social anxiety go away on its own?
Unlike shyness, which may improve with experience and familiarity, social anxiety disorder typically worsens without treatment. The avoidance behaviour that provides short-term relief sustains and strengthens the anxiety long-term. Cleveland Clinic states clearly that social anxiety disorder generally doesn’t go away on its own — but it does respond well to evidence-based treatment, particularly CBT.
Is social anxiety the same as introversion?
No. Introversion is a preference for less social stimulation — introverts find large amounts of social interaction draining rather than energising. It is a temperament, not a disorder, and it does not involve fear. Social anxiety disorder involves fear of negative evaluation and judgment, not a preference for solitude. An introvert can be entirely comfortable in social situations they choose to be in. A person with social anxiety disorder experiences fear in social situations regardless of whether they’ve chosen to be there.
Sources & References
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, 5th Edition, Text Revision (DSM-5-TR). APA Publishing, 2022. psychiatry.org
- National Institute of Mental Health (NIMH). “Social Anxiety Disorder: Statistics.” U.S. Department of Health and Human Services. nimh.nih.gov
- Merck Manual Professional Edition. “Social Anxiety Disorder.” Reviewed 2024. merckmanuals.com
- Cleveland Clinic. “Social Anxiety Disorder: Symptoms and Treatment.” Reviewed 2024. my.clevelandclinic.org
- Social Anxiety Institute. “Shyness or Social Anxiety Disorder?” socialanxietyinstitute.org
- Talkiatry. “Shyness vs Social Anxiety: Are They the Same?” March 2024. talkiatry.com
- UNSW Sydney. “What’s the Difference Between Shyness and Social Anxiety?” 2024. unsw.edu.au
- Prevalence and Severity of Social Anxiety Symptoms. PMC, 2024. doi:10.3389/fpsyg.2024. pmc.ncbi.nlm.nih.gov/articles/PMC10909235
- Iimori M, et al. “Comparative effectiveness of non-pharmacological interventions for social anxiety disorder in adults: a systematic review and meta-analysis.” Frontiers in Psychology, 2026. doi:10.3389/fpsyg.2026.1787151. frontiersin.org
- Nordmo M, et al. “Cognitive behaviour therapy for social anxiety disorder: a systematic review and meta-analysis investigating different treatment formats.” Australian Psychologist, 2024. doi:10.1080/00050067.2024.2356804. tandfonline.com
- Bayesian Network Meta-Analysis on psychotherapies for SAD. Journal of Affective Disorders, 2024. sciencedirect.com
- Social Anxiety Disorder: Associated Conditions and Therapeutic Approaches. PMC, 2023. doi:10.3390/ijerph20010036. ncbi.nlm.nih.gov/pmc/articles/PMC9847330
- Wikipedia. “Shyness.” en.wikipedia.org/wiki/Shyness
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to self-diagnose or replace consultation with a qualified mental health or medical professional. If social anxiety is significantly affecting your daily life, speaking with a GP or mental health professional is the most effective next step.

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Paternal postpartum depression is a clinical condition that requires professional assessment. If you recognise yourself or a loved one in this article, use it as a starting point for a conversation with a qualified healthcare professional — not as a conclusion.
When people talk about postpartum depression, the image that typically comes to mind is a new mother — tearful, overwhelmed, struggling to bond with her baby. What that picture leaves out entirely is the father sitting next to her who has barely spoken in three weeks, who snaps at the smallest inconvenience, and who wonders why he feels nothing when he holds his newborn.
Paternal postpartum depression is real, it is common, and it looks almost nothing like the maternal version most of us learned to recognize.
Research published in JAMA — a landmark meta-analysis by James Paulson and Sharnail Bazemore reviewing data from nearly 28,000 fathers — found that roughly 1 in 10 new fathers experiences significant depression in the first year after their baby is born. That rate is approximately twice the background depression rate for men in the general population. Among fathers whose partners are also experiencing postpartum depression, the number climbs to roughly 1 in 4.
Those are not small numbers. They represent millions of men every year who are struggling in silence — and whose struggles rarely get named, screened for, or treated.
Key Takeaways
- 1 in 10 new fathers develops postpartum depression in the first year after birth — roughly twice the background depression rate for men in the general population (Paulson & Bazemore, JAMA).
- If your partner has PPD, your risk rises to roughly 1 in 4. A partner’s postpartum depression is the single strongest predictor of paternal PPD.
- Paternal PPD does not look like maternal PPD. Fathers are more likely to show externalising symptoms — irritability, anger, emotional withdrawal, increased alcohol use, throwing themselves into work — rather than the sadness and tearfulness most people associate with depression.
- It is not a separate DSM-5 diagnosis. Clinically, it maps onto Major Depressive Disorder (MDD) or adjustment disorder — the same categories used for depression in any other context.
- Hormones play a role. Testosterone decreases in actively involved fathers, and some research links a sharper testosterone drop to greater depression risk.
- It almost always goes unrecognised. There are no universal screening guidelines for new fathers, the most common screening tool (the EPDS) was designed for women, and cultural expectations push men to stay silent.
- The impact extends to children. Untreated paternal PPD is independently associated with behavioural difficulties, language delays, and emotional dysregulation in early childhood.
- It is treatable. CBT, interpersonal therapy, and antidepressant medication all show effectiveness — the same approaches that work for other forms of depression work here too.
- Only 3.2% of new fathers with depression actually seek help. If you recognise these signs in yourself or your partner, naming it is the first step.
What Is Paternal Postpartum Depression?
Paternal postpartum depression (sometimes abbreviated PPPD) is not a separate, distinct diagnosis in the DSM-5-TR. Clinically, it maps onto Major Depressive Disorder (MDD) or, in milder cases, adjustment disorder — the same diagnostic categories used for anyone experiencing a significant depressive episode.
The “postpartum” part simply reflects timing: symptoms that emerge during a partner’s pregnancy or in the months following birth, tied to the enormous physical, emotional, relational, and financial disruption that becoming a parent creates.
That lack of a standalone DSM-5 category has real-world consequences. It means there are no universal screening guidelines for fathers at postnatal or pediatric visits, no standard protocol that asks new dads how they are actually doing, and no clinical consensus on exactly which assessment tool to use. Most existing screening instruments — including the widely used Edinburgh Postnatal Depression Scale (EPDS) — were originally designed and validated for mothers, and adapted versions for fathers are still making their way into routine practice.
Why It Looks Different in Dads
This is the piece most online articles miss entirely, and it is the most important thing to understand.
Depression in men and women frequently presents differently — and nowhere is that gap wider than in the postpartum period. Maternal postpartum depression tends toward internalizing symptoms: sadness, tearfulness, hopelessness, difficulty bonding, withdrawal into quietness. It fits the cultural image of depression well enough that it gets recognized.
Paternal postpartum depression tends toward externalizing symptoms: irritability, anger, restlessness, throwing oneself into work, increased alcohol or substance use, emotional detachment, and risky behaviors. These don’t look like depression to most people — including to the fathers experiencing them. They look like stress, like personality, like being a workaholic, like “that’s just how he handles things.”
According to research published in Frontiers in Psychology (2024), men may also underreport or mask depressive symptoms on standard self-report measures — meaning even when screened, paternal depression is likely being undercounted.
The clinical language for this distinction is useful: fathers are more likely to show externalizing presentations while mothers more commonly show internalizing presentations. Both are depression. Only one gets recognized as such.
Signs of Postpartum Depression in New Dads

The following signs, particularly when they cluster together or represent a clear change from the father’s usual baseline, warrant attention.
Irritability and Anger Out of Proportion
One of the most consistently reported signs. The baby crying becomes intolerable. A minor household disagreement escalates. A partner’s casual comment lands like a criticism. This isn’t a temper problem — it’s an emotional regulation problem driven by an underlying depressive state. In men, irritability is frequently the surface expression of the sadness that goes unreported.
Emotional Numbness or Detachment from the Baby
Many fathers with postpartum depression describe feeling “nothing” when they hold their newborn — no surge of love, no fierce protectiveness, no joy. They expected to feel overwhelmed with warmth. Instead, they feel like they are holding a stranger. This absence of expected feeling is deeply distressing and rarely talked about because admitting it feels like a confession of bad fatherhood.
This kind of detachment is not a reflection of character or love. It is a symptom, and it responds to treatment.
Withdrawing from the Family
Spending longer hours at work. More time in front of screens. Disappearing into hobbies, the garage, the gym — anywhere that isn’t the shared domestic space where the pressure concentrates. This withdrawal can look like avoidance of responsibility, but it often reflects an inability to tolerate the emotional overwhelm of the home environment when the nervous system is already at its limit.
Increased Alcohol or Substance Use
Self-medication is a common but often invisible coping strategy. A few beers each evening that gradually became six. Smoking more. Relying on cannabis to feel calm. These patterns frequently emerge in the postpartum period among fathers and rarely get connected to the depression driving them.
Physical Complaints Without a Clear Cause
Depression in men frequently manifests somatically. New fathers with PPPD commonly report persistent fatigue (beyond ordinary sleep deprivation), headaches, digestive problems, back and muscle tension, and a general physical flatness. When a man visits a doctor about these symptoms, the underlying depression may not come up at all.
Loss of Interest in Things That Used to Matter
The sport he followed obsessively, the music he played, the friends he kept up with — all of it feels distant and hollow. This anhedonia (the clinical term for loss of pleasure in previously enjoyable activities) is one of the core diagnostic criteria for MDD, and it’s just as present in paternal depression as in any other form.
Sleep Problems Unrelated to Infant Waking
Sleep deprivation with a newborn is universal. But fathers with PPPD often describe an inability to sleep even when the baby is not waking them — lying awake with looping, anxious thoughts, or waking hours too early with a sense of dread. This goes beyond ordinary new-parent exhaustion and reflects a disrupted sleep architecture characteristic of clinical depression.
Anxiety, Hypervigilance, or Obsessive Worry
Some fathers experience the postpartum period primarily through anxiety: constant catastrophizing about the baby’s health, obsessive checking behaviors, terror about something going wrong, or a vague, unshakeable sense of impending disaster. This anxious presentation often co-occurs with depression and is frequently missed because it reads as “concerned parenting” rather than a clinical anxiety-depression picture.
Relationship Conflict and Emotional Distance from Partner
PPPD consistently correlates with increased marital stress. The father pulls away emotionally. Arguments become more frequent or more intense. Intimacy disappears — not just physically but in the small moments of connection that hold relationships together. Partners often describe feeling like they are parenting alone even when he is physically present.
The Hormonal Piece
Postpartum hormonal shifts are not only a maternal story. Research shows that testosterone levels decrease in actively involved fathers, particularly those who take on hands-on caregiving. While this hormonal shift appears to support pair bonding and parental investment, some studies — including work published in Frontiers in Psychology — suggest that men who experience a sharper testosterone drop may be more vulnerable to depressive symptoms.
Oxytocin, the bonding hormone, also changes in new fathers, and how those changes unfold appears to interact with depression risk. The hormonal picture in paternal postpartum depression is still being mapped — but the idea that fathers are biologically unaffected by the arrival of a new baby is simply wrong.
Risk Factors: Who Is Most Vulnerable
No single risk factor predicts paternal postpartum depression, but several raise the probability significantly.
Partner’s postpartum depression is the strongest predictor in the research literature. A father whose partner is experiencing PPD has roughly a 50% chance of developing depression himself — more than twice the baseline risk. This bidirectional relationship means that failing to identify and treat PPPD in either parent puts both at greater risk.
Other well-established risk factors include:
- Prior history of depression or anxiety — the strongest individual-level predictor
- Sleep deprivation — not just from infant care but disrupted, non-restorative sleep
- Financial stress — the economic pressure of a growing family, particularly if income has changed
- Relationship conflict — poor partner communication before or during the postpartum period
- Feeling excluded from the infant-mother bond — a specific and underacknowledged source of distress for fathers
- Lack of social support — social isolation amplifies all other risk factors
- Unplanned or complicated pregnancy — additional stressors during the perinatal period
- Limited involvement in infant care — counterintuitively, fathers with less hands-on engagement may lose a key buffer against depression
Why It Goes Unrecognized
The gap between how many fathers experience postpartum depression and how few receive help is striking. Research cited in Psychology Today found that only about 3.2% of new fathers actually use mental health services in the postpartum period — a number that reflects systemic failures, not a low prevalence.
Several forces converge to keep paternal PPD invisible:
Cultural scripts about fatherhood and masculinity. Men are expected to be steady, functional, and supportive — the strong one when the mother is struggling. Admitting depression can feel like a betrayal of that role. Many fathers describe feeling they have “no right” to their distress when it is the mother who just went through pregnancy and birth.
Symptom mismatch. The cultural image of depression — sadness, crying, visible suffering — does not match the irritability, numbness, and withdrawal that characterize PPPD. Many fathers genuinely do not recognize their experience as depression.
No formal screening. Mothers receive Edinburgh Postnatal Depression Scale screening at obstetric and pediatric visits. Fathers are rarely in those rooms, and when they are, the screening almost never extends to them.
The baby’s needs absorb all attention. In the blur of early parenthood, everyone — including the father himself — tends to focus on the infant and the mother. A father who is quietly struggling often remains invisible until the family is in crisis.
The Impact on Children
Paternal postpartum depression is not only a father’s problem. Research consistently shows that PPPD affects children’s outcomes independently of maternal PPD. Fathers with untreated depression show less warm, responsive, and engaged parenting — and early paternal engagement is a significant predictor of cognitive and emotional development. Children whose fathers experienced postpartum depression show elevated rates of behavioral problems, language delays, and emotional dysregulation in early childhood.
This is not about blame. It is about the stakes — and about why identifying and treating PPPD matters for the whole family.
When to Seek Help

If you recognize several of these signs in yourself — or in your partner — treat it the same way you would treat any other medical concern: with directness, without waiting for a crisis.
If symptoms have persisted for two weeks or more, if they are getting in the way of work, relationships, or daily function, or if you are having thoughts of harming yourself or someone else, those are clear signals to reach out now. A GP or primary care physician is a reasonable first contact; they can screen formally, rule out any physical contributors (thyroid function, for instance), and make a referral to a mental health professional.
Paternal postpartum depression responds well to the same treatments that work for other forms of depression: cognitive behavioral therapy (CBT), interpersonal therapy (IPT), and in some cases antidepressant medication. Peer support groups — including those specifically for new fathers — also show promising outcomes, particularly because they work around the barrier of one-to-one clinical settings that many men avoid.
A father who recognizes himself in any of the signs above and finds himself wondering if this is more than ordinary stress might find it useful to read about high-functioning depression — the form of depression that allows a person to appear fully operational while privately struggling — because that masked quality is precisely how paternal PPD often presents.
If the picture feels more acute — if it has crossed from persistent low mood into something that feels like a breaking point — the post on signs of a nervous breakdown covers the specific threshold markers that should prompt immediate professional contact.
And if the dominant experience is less about mood and more about total depletion — running on nothing, unable to recover no matter how much you sleep — it may be worth reading about emotional exhaustion vs. burnout to understand whether what you’re experiencing is burnout layered on top of depression, which is common in the postpartum period.
Frequently Asked Questions
How long does paternal postpartum depression last?
Without treatment, paternal postpartum depression can persist for months or even years. Research suggests symptoms often peak between three and six months after birth, but untreated depression does not reliably resolve on its own. With appropriate treatment — therapy, medication, or a combination — most men see significant improvement within weeks to months.
Can fathers get postpartum depression even if they weren’t present at the birth?
Yes. Paternal postpartum depression is driven by the cumulative stress, sleep deprivation, relational disruption, hormonal changes, and identity upheaval of new parenthood — not by the birth experience itself. Fathers who were absent at birth, adoptive fathers, and fathers in same-sex partnerships where no partner was pregnant have all been documented to experience postpartum depression.
What is the difference between paternal postpartum depression and baby blues in dads?
Baby blues — a brief period of tearfulness, emotional reactivity, and mood fluctuation in the first week or two after birth — are common in both mothers and fathers and typically resolve on their own within two weeks. Paternal postpartum depression is distinguished by duration (two weeks or more), functional impairment, and the cluster of clinical symptoms described above. If the low mood, irritability, or withdrawal persists past the two-week mark and is affecting daily life, that is no longer baby blues.
Is there a screening test for paternal postpartum depression?
The Edinburgh Postnatal Depression Scale (EPDS), originally designed for mothers, is the most widely used tool and has adapted versions validated for use with fathers. Some researchers advocate for the Paternal Postnatal Depression Questionnaire (PPDQ) or the Beck Depression Inventory (BDI-II) as complementary tools. However, no universal, standardized screening protocol currently exists for fathers in most clinical settings — which is one of the main reasons PPPD goes undetected.
Does paternal postpartum depression affect the baby?
Research consistently shows that untreated paternal postpartum depression affects children’s development independently of maternal PPD. Children of depressed fathers show elevated rates of behavioral difficulties, language delays, and emotional regulation problems in early childhood. Early identification and treatment of PPPD protects not only the father’s wellbeing but the long-term outcomes of the whole family.
The Bottom Line
Postpartum depression does not check whether you are the parent who gave birth. It affects roughly 1 in 10 new fathers — showing up not as the sadness and crying that most people picture, but as irritability, emotional numbness, withdrawal, and a quiet inability to feel the joy that everyone else seems to be expecting.
The silence around paternal postpartum depression costs families enormously. It costs fathers their wellbeing, partners their support, and children a present, engaged dad during a period of development that shapes them for life.
If this sounds like something you — or someone you know — might be going through, the most useful next step is also the simplest one: name it, without minimizing it, and talk to someone. The same clinical tools that treat depression in every other context work here too. You don’t have to wait until it gets worse.
Sources:
- Paulson JF, Bazemore SD. Prenatal and postpartum depression in fathers and its association with maternal depression: a meta-analysis. JAMA. 2010;303(19):1961–1969. https://jamanetwork.com/journals/jama/fullarticle/185844
- Kotov A, Corpuz M. Paternal postpartum depression: risk factors and relationship to maternal postpartum depression. Frontiers in Psychology. 2024;15:1348031. https://www.frontiersin.org/journals/psychology/articles/10.3389/fpsyg.2024.1348031/full
- National Institutes of Health / PMC. Paternal perinatal depression — PMC11453120. https://pmc.ncbi.nlm.nih.gov/articles/PMC11453120/
- Anderson S. Can Fathers Suffer From Postpartum Depression? Psychology Today. April 2024. https://www.psychologytoday.com/ca/blog/preparing-for-parenthood/202404/can-fathers-suffer-from-postpartum-depression
- American Psychological Association. Paternal postpartum depression. https://www.apa.org/monitor/2019/07-08/paternal-depression
- National Institute of Mental Health (NIMH). Depression. https://www.nimh.nih.gov/health/topics/depression
- Postpartum Depression. org. Depression in New Fathers. https://www.postpartumdepression.org/postpartum-depression/depression-in-fathers/

Informational purposes only — not a substitute for medical advice
Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you are experiencing unexplained or severe physical symptoms, please consult a qualified healthcare professional to rule out other conditions.
The headache that won’t lift. The knot in your stomach before a difficult conversation. The way your heart races when your inbox fills up. These aren’t coincidences — and they’re not weakness. They are the predictable, well-documented result of biological systems doing exactly what they were designed to do, just in a context those systems weren’t designed for.
According to the American Psychological Association’s research on stress and the body, stress affects every major organ system — cardiovascular, respiratory, musculoskeletal, gastrointestinal, endocrine, reproductive, and immune. The APA reports that approximately 75% of Americans experience physical or emotional symptoms they associate with stress. Gallup’s 2023 Global Emotions Report puts daily significant stress at around 49% of US adults.
These are not trivial numbers. And the symptoms they produce are not trivial either.
This article covers what stress and anxiety actually do to your body, system by system, with the physiological mechanisms explained — because understanding why something is happening is often the first step toward addressing it.
The Two-System Response: What’s Actually Happening
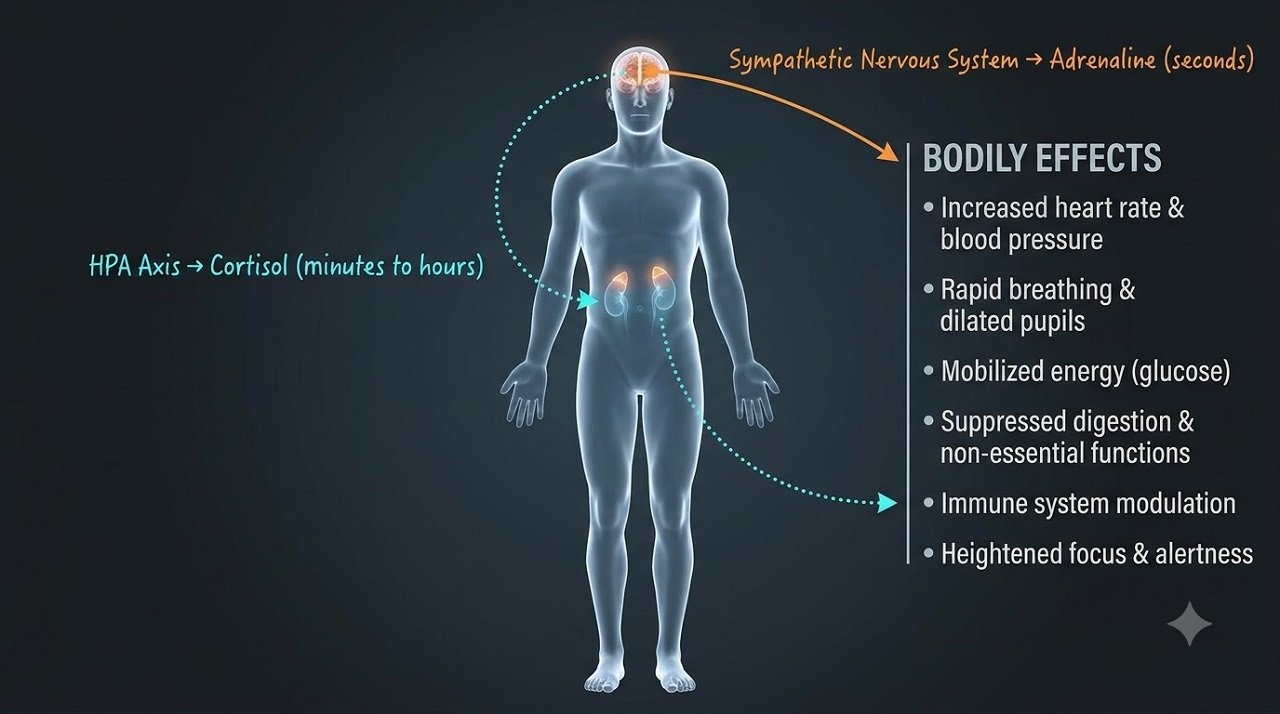
Before diving into symptoms by body system, it helps to understand the two biological systems driving them.
The sympathetic nervous system (SNS) — the fast response. When you perceive a threat — a deadline, a confrontation, a frightening piece of news — your brain’s amygdala fires an alarm signal. Your hypothalamus activates the sympathetic nervous system within milliseconds, flooding your body with adrenaline (epinephrine) and noradrenaline. Heart rate accelerates. Blood is diverted away from non-essential systems (digestion, reproduction, immune activity) toward the muscles and lungs. Your pupils dilate. Your liver dumps glucose into your bloodstream. This is the fight-or-flight response, and it is fast, powerful, and non-discriminating — it cannot tell the difference between a tiger and an unread email.
The HPA axis — the sustained response. Seconds later, the hypothalamic-pituitary-adrenal (HPA) axis activates. Your hypothalamus signals the pituitary gland, which signals the adrenal glands to release cortisol — the primary stress hormone. Unlike adrenaline, which spikes and fades, cortisol lingers. Its job is to sustain the stress response and mobilise energy over a longer period. According to the APA, cortisol normally drops once the stressor resolves. In chronic stress, it does not — and this sustained cortisol elevation is where most of the long-term physical damage originates.
Anxiety operates through the same systems. The difference is that anxiety is often triggered by perceived or anticipated threats rather than immediate ones — which means the stress response can fire repeatedly in the absence of a concrete danger, and the body pays the same physiological price regardless.
Cardiovascular System: Heart, Blood Pressure, Circulation

Acute response: During the immediate stress response, your heart beats faster and harder. Blood pressure rises. Blood is redirected to large muscles to support physical action.
Chronic impact: When the stress response activates frequently and stays activated, the cardiovascular system bears a disproportionate share of the cost. According to the APA, chronic stress is associated with higher risk of hypertension, inflammation in the coronary arteries, heart attack, and stroke. The mechanism involves sustained SNS activation increasing arterial pressure, while elevated cortisol promotes inflammatory processes that can contribute to arterial plaque.
Anxiety adds another layer. The palpitations, racing heart, and chest tightness that accompany acute anxiety — which are covered in detail in our article on what an anxiety attack feels like physically — activate the same cardiovascular pathways. When anxiety is persistent, those pathways stay activated.
What you may notice:
- Racing or irregular heartbeat (palpitations)
- Chest tightness or pressure
- A pounding sensation in the chest, neck, or temples
- Elevated resting heart rate
- Cold hands and feet (blood diverted from extremities)
- Elevated blood pressure readings
Musculoskeletal System: Tension, Pain, Headaches
Muscle tension is one of the most immediate and universal physical responses to stress. According to the APA, the body’s protective reflex under threat is to tighten muscles — a preparation for impact or physical action. In a genuinely physical emergency, this makes sense. Sustained under chronic stress, it produces a state of near-constant guarding that most people don’t consciously register until it produces pain.
The APA notes that job-related stress in particular is linked to tension-type headaches and low back and upper limb pain. The pathway is direct: sustained contraction of the neck, scalp, and shoulder muscles restricts blood flow and irritates surrounding tissue, producing the characteristic band-like pressure of a tension headache. Jaw clenching and teeth grinding (bruxism) — often occurring unconsciously during sleep — are closely associated with chronic stress and anxiety and can cause jaw pain, dental damage, and morning headaches.
What you may notice:
- Tension headaches — a band of pressure across the forehead or around the skull
- Neck and shoulder stiffness or aching
- Jaw soreness, especially in the morning
- Upper or lower back pain without a clear physical cause
- A general feeling of physical heaviness or fatigue
Respiratory System: Breathing, Chest, Asthma
Stress and anxiety constrict the airways. According to the APA, this constriction can cause shortness of breath and rapid breathing, and can trigger or worsen asthma and COPD in people who have those conditions.
For people with anxiety specifically, respiratory symptoms are a core physical feature — and they operate in a loop. Rapid shallow breathing (hyperventilation) reduces carbon dioxide levels in the blood, which produces tingling, dizziness, and a sense of unreality. This heightened bodily awareness then feeds back into anxiety, intensifying the breath-focused symptoms. The APA notes that stress-driven hyperventilation can trigger panic attacks in people who are prone to them.
What you may notice:
- Shortness of breath at rest or with mild exertion
- A feeling of not being able to get a full breath
- Rapid, shallow breathing
- Chest tightness
- Sighing frequently
- Dizziness or light-headedness
- Tingling in the hands, feet, or face
Gastrointestinal System: The Gut-Brain Axis

This is the body system where stress and anxiety produce the broadest range of symptoms — and the one where the physiological mechanism is most underappreciated.
The gut contains more nerve endings than the spinal cord and is sometimes called the “second brain” because of its dense neural network (the enteric nervous system). The gut and brain are in continuous, bidirectional communication via the vagus nerve — a direct highway connecting the two. This connection is why anxiety produces stomach symptoms before a presentation, and why gastrointestinal disease often worsens mental health.
According to the APA, stress can intensify pain, bloating, and nausea; change appetite; worsen heartburn and acid reflux; cause diarrhoea or constipation; produce bowel spasms; and weaken the intestinal barrier. The APA explicitly notes that stress does not cause stomach ulcers — those are caused by bacterial infection — but it can make ulcers more painful and harder to heal.
Irritable bowel syndrome (IBS) is particularly closely linked to stress and anxiety. Research in Nutrients and multiple PMC reviews confirms that the HPA axis dysregulation seen in chronic stress directly disrupts gut motility, alters the gut microbiome, and increases intestinal permeability — all of which can trigger or worsen IBS symptoms. The University of Michigan’s Digestive Health program notes that the gut-brain connection is bidirectional: stress worsens gut symptoms, and gut symptoms in turn worsen stress and anxiety.
What you may notice:
- Nausea or stomach cramps before or during stressful events
- Appetite changes — eating much more or much less than usual
- Constipation, diarrhoea, or alternating patterns
- Heartburn or acid reflux flares
- Bloating or gas
- IBS flares with no obvious dietary trigger
Immune System: Illness, Inflammation, Slow Healing
Cortisol is both an anti-inflammatory and an immune suppressant. In the short term, this is adaptive — it prevents the immune system from over-responding to the immediate stressor. Over the long term, chronically elevated cortisol impairs the immune system’s ability to respond normally to threats.
According to the APA, impaired HPA axis communication — a hallmark of chronic stress — has been linked to more frequent illness, chronic fatigue, metabolic disorders including diabetes and obesity, and immune disorders. Research published in JAMA Psychiatry found that prolonged high stress doubled the likelihood of developing metabolic syndrome. The cumulative biological cost of chronic stress on the body’s regulatory systems is sometimes described as allostatic load — a concept developed by neuroscientist Bruce McEwen at Rockefeller University to quantify the wear and tear chronic stress places on the body’s regulatory systems.
Wound healing is also impaired under stress. The PMC review published in 2026 on stress and skin conditions found that stress reduces collagen production and delays tissue repair, and that preoperative fear and anxiety are associated with impaired wound recovery.
What you may notice:
- Getting sick more often — colds, infections, minor illnesses
- Taking longer to recover from illness
- Feeling run-down even when not actively unwell
- Slow healing of minor cuts or skin irritation
- Chronic low-grade inflammation
Skin: The Visible Signal of Internal Stress
Skin is one of the most responsive organs to stress, because it has its own local HPA-like system that mirrors the systemic stress response. The 2026 PMC narrative review on psychological stress and skin conditions confirms that the HPA axis elevation seen under stress increases cortisol at both systemic and local levels, which reduces skin hydration, impairs the skin barrier, promotes inflammatory skin responses, and raises ACTH — which increases melanin production and can cause hyperpigmentation.
Specific dermatological conditions strongly linked to stress include psoriasis, atopic dermatitis (eczema), acne, alopecia areata (patchy hair loss), urticaria (hives), and seborrheic dermatitis. The review also documents a separate mechanism — catecholamines and neuropeptides released by nerve fibres near the skin triggering mast cell activation and neurogenic inflammation, which drives itch, redness, and barrier changes.
Telogen effluvium — diffuse hair shedding typically occurring two to three months after an acute stressor — is also well documented. It is caused by the stress response prematurely pushing hair follicles from the growth phase into the resting phase.
What you may notice:
- Acne flares not obviously linked to diet or hormones
- Eczema or psoriasis worsening during stressful periods
- Hives or unexplained skin redness
- Increased skin sensitivity
- Hair thinning or shedding two to three months after an intense stressor
- Slow healing of skin conditions
Sleep: Cortisol’s Most Disruptive Effect

Cortisol and sleep are on opposite schedules in a healthy system. Cortisol peaks in the morning to prepare you for the day and falls through the evening to allow sleep to occur. Chronic stress disrupts this rhythm — keeping cortisol elevated into the evening, which delays sleep onset, reduces deep sleep, and can cause early-morning waking (the body’s misread attempt to mobilise for a day that hasn’t started).
According to Henry Ford Health’s 2026 overview of stress and the body, trouble sleeping is one of the most common chronic stress symptoms, alongside headaches, digestive problems, high blood pressure, and hives.
Anxiety adds its own sleep disruption: racing thoughts, physical tension, and hypervigilance around sleep itself (the anxious monitoring of whether sleep is coming) can create a feedback loop where anxiety causes poor sleep, and poor sleep worsens anxiety.
What you may notice:
- Difficulty falling asleep despite feeling tired
- Waking in the early hours and being unable to return to sleep
- Unrefreshing sleep — waking more tired than when you went to bed
- Vivid or disturbing dreams
- Racing thoughts at bedtime
Endocrine and Metabolic System: The Long-Term Cost
The HPA axis is the body’s central stress management system, but it does not operate in isolation. Prolonged HPA activation disrupts blood sugar regulation (cortisol raises blood glucose to fuel the fight-or-flight response), thyroid function, and the balance of reproductive hormones.
The APA notes that chronic HPA dysregulation has been linked to metabolic disorders including type 2 diabetes and obesity — consistent with the JAMA Psychiatry finding that prolonged high stress doubled the likelihood of metabolic syndrome. The mechanism involves sustained cortisol elevation promoting insulin resistance and visceral fat accumulation over time.
Reproductive System
In men: According to the APA, chronic stress can reduce testosterone production, lowering libido and potentially causing erectile dysfunction. One cited study found that men who experienced two or more stressful life events in the past year had lower sperm motility and a lower percentage of normal-morphology sperm than men who had not.
In women: The APA reports that stress may cause absent or irregular menstrual cycles, more painful periods, and changes in cycle length. It can reduce sexual desire, affect fertility, and worsen premenstrual symptoms and menopausal hot flashes. Conditions such as PCOS may also be worsened by chronic stress-related hormonal dysregulation.
The Anxiety Symptom Loop
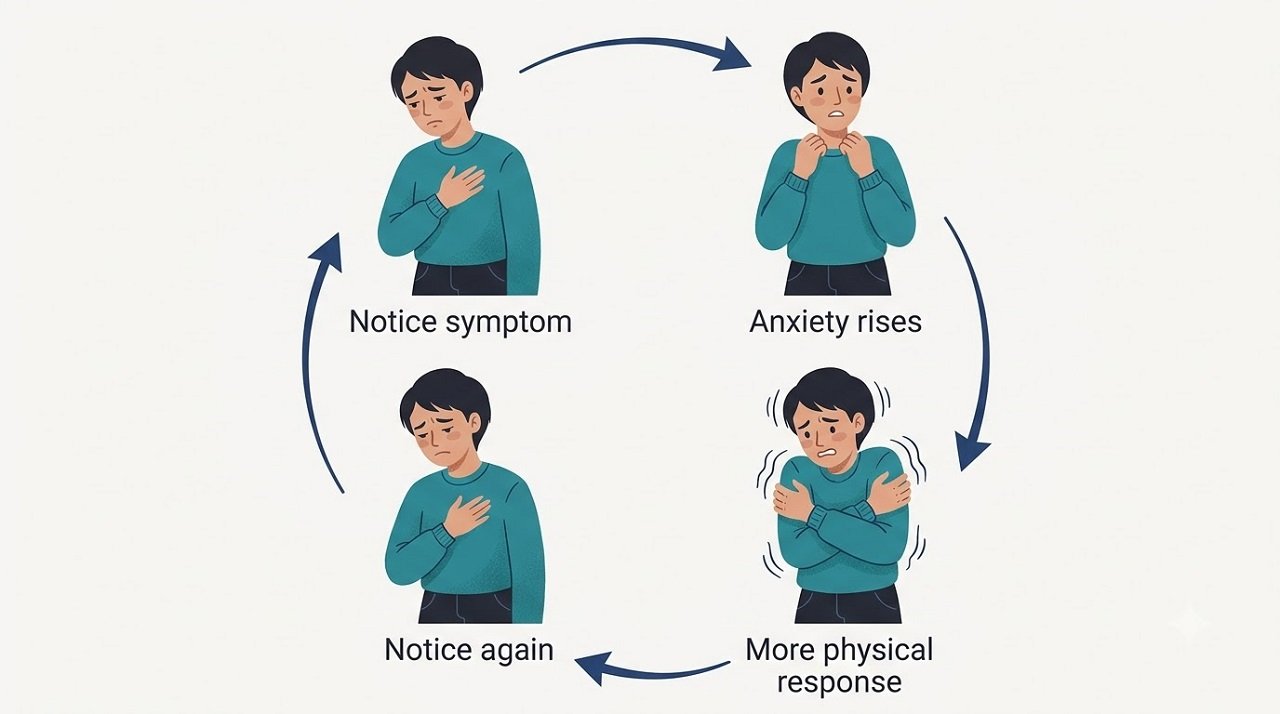
One feature of anxiety-related physical symptoms that sets them apart from stress symptoms is a feedback mechanism — sometimes called interoceptive amplification — where the physical symptom itself becomes a new source of anxiety.
You notice your heart beating harder. That noticing activates the threat-detection system, which increases the heart rate further. You notice the increased heart rate, which increases anxiety, which increases heart rate. The same loop can run with breathing, with dizziness, with gut symptoms. This is why anxiety physical symptoms can feel as though they escalate from nowhere — because the body’s own monitoring of its symptoms becomes the stressor.
Understanding this loop is important because it changes the intervention. Trying to suppress the symptom directly often makes the loop worse. Evidence-based approaches to anxiety — particularly CBT and exposure-based therapy — work in part by reducing the threat value of the bodily sensation rather than eliminating the sensation itself.
This connection between physical stress symptoms and trauma responses is also worth understanding. The fight/flight/freeze physiology that underlies trauma responses uses the same HPA and ANS pathways, and the physical symptoms can be nearly identical.
When Physical Stress Symptoms Become Chronic: Allostatic Load
Most stress responses are designed to be temporary. The body activates, the stressor resolves, and the system returns to baseline. The problem in modern life is that many stressors — work pressure, financial strain, relationship conflict, ongoing health concerns — do not resolve quickly. The stress response activates repeatedly, and the recovery periods become shorter.
This accumulation of physiological wear is what neuroscientist Bruce McEwen called allostatic load — the cumulative cost on the body’s regulatory systems from repeated or chronic stress. High allostatic load is associated with earlier onset of cardiovascular disease, metabolic disorders, immune dysfunction, and cognitive decline.
Our article on what emotional exhaustion and burnout actually are covers how this chronic activation plays out in the context of sustained life demands — it is worth reading alongside this one.
When to See a Doctor

Most physical symptoms of stress and anxiety are real — not imagined, not invented, not “just in your head” — and many resolve or significantly improve when the underlying stress is addressed. However, because stress and anxiety symptoms overlap with symptoms of conditions that need medical attention, certain presentations warrant a medical evaluation:
- Chest pain, particularly with shortness of breath, pain radiating to the arm or jaw, or sweating — these require urgent evaluation to rule out cardiac causes
- Heart palpitations that are irregular, sustained, or accompanied by dizziness or fainting
- Unexplained weight loss alongside other symptoms
- GI symptoms that are new, persistent, include blood, or cause significant weight loss
- Skin changes that don’t improve or appear to be worsening
- Severe or new headache unlike previous headaches
- Neurological symptoms — persistent numbness, vision changes, weakness in a limb
A GP or healthcare provider can assess whether symptoms are stress-related or require further investigation, and can also refer to mental health support if appropriate.
Frequently Asked Questions
Can stress and anxiety cause real physical symptoms?
Yes — completely. Physical symptoms of stress and anxiety have well-documented physiological mechanisms. They are produced by the same nervous system and hormonal pathways (HPA axis, sympathetic nervous system, cortisol) that evolved to handle physical threats. According to the APA, stress affects every major organ system in the body — cardiovascular, respiratory, gastrointestinal, musculoskeletal, endocrine, immune, and reproductive.
What are the most common physical symptoms of stress?
According to the APA and clinical literature, the most commonly reported physical symptoms of stress include headaches (particularly tension headaches), muscle tension (especially neck and shoulders), fatigue, GI problems (nausea, stomach aches, changes in bowel habits), sleep disturbance, and cardiovascular symptoms including elevated heart rate and blood pressure. Skin conditions including acne and eczema flares are also well documented.
Why does stress cause stomach problems?
The gut and brain are connected by the vagus nerve through the gut-brain axis. The gut contains its own dense neural network (the enteric nervous system), and stress activates the HPA axis, which directly disrupts gut motility, alters the intestinal barrier, and changes gut microbiome composition. The result is GI symptoms including nausea, cramping, bloating, diarrhoea, or constipation — even without any gastrointestinal disease present.
Can stress cause hair loss?
Yes. Telogen effluvium — diffuse hair shedding — is a well-documented response to significant acute stress. It occurs because stress hormones push hair follicles prematurely from the growth (anagen) phase into the resting (telogen) phase. The shedding typically appears two to three months after the stressful event, which is why the connection is often not made. In most cases, once the stressor resolves and is managed, hair regrowth follows.
How do I know if my physical symptoms are from stress or something else?
Physical symptoms that appear or worsen during stressful periods and improve when stress reduces are likely stress-related. However, because stress symptoms overlap with symptoms of several conditions requiring medical attention (heart disease, thyroid disorders, GI conditions, etc.), symptoms that are new, severe, persistent, or accompanied by red flags like chest pain with shortness of breath, unexplained weight loss, or blood in stool warrant medical evaluation. A GP can help determine the cause and, if appropriate, refer to mental health support alongside any medical treatment.
Sources & References
- American Psychological Association. “Stress Effects on the Body.” APA Help Center. apa.org/topics/stress/body
- Henry Ford Health. “How Stress Shows Up in the Body.” July 2026. henryford.com/blog/2026/07/how-stress-shows-up-in-the-body
- American Institute of Stress / Gallup. “What the Latest Reports Say About Stress in America.” Stress.org. stress.org/news/what-the-latest-reports-say-about-stress-in-america
- Gallup. 2023 Global Emotions Report. gallup.com/analytics/349280/gallup-global-emotions-report.aspx
- JAMA Psychiatry. “Prolonged High Stress and Metabolic Syndrome Risk.” 2022. jamanetwork.com/journals/jamapsychiatry
- Teo JX, et al. “Psychological Stress and Skin Conditions: A Comprehensive Narrative Review.” PMC, 2026. pmc.ncbi.nlm.nih.gov/articles/PMC12681996
- University of Michigan Digestive Health. “Gut-Brain Axis and IBS.” med.umich.edu/pdf/digestive/Gut-Brain-Axis-and-IBS.pdf
- National Institute of Mental Health (NIMH). “I’m So Stressed Out! Fact Sheet.” nimh.nih.gov/health/publications/so-stressed-out-fact-sheet
- McEwen BS. “Allostasis and Allostatic Load: Implications for Neuropsychopharmacology.” Neuropsychopharmacology, 2000. Rockefeller University. doi.org/10.1016/S0893-133X(99)00129-3
- Orlando Health. “Five Health Risks of Stress.” orlandohealth.com/content-hub/five-health-risks-of-stress
This article is for informational and educational purposes only. It does not constitute medical advice and should not be used to replace consultation with a qualified healthcare or mental health professional. If you are experiencing physical symptoms that concern you, please speak with a doctor.

Health Tips for Night Shift Workers: The Long-Term Survival Guide

Natural Remedies for ADHD: What the Evidence Actually Says

Soft Protein Foods for GLP-1 Dose Increase Day: What to Eat When Your Stomach Is Sensitive

PEMF Webinar

HBOT ( Hyperbaric Oxygen Therapy ) Webinar

The 4-7-8 Breathing Technique: Step-by-Step Guide and What the Research Actually Shows
-
 Events6 days ago
PEMF Webinar
-
 Events2 months ago
HBOT ( Hyperbaric Oxygen Therapy ) Webinar
-
 Natural Sleep Remedies6 months ago
The 4-7-8 Breathing Technique: Step-by-Step Guide and What the Research Actually Shows
-

 Events5 months ago
Why You Can’t Trust Big Pharma
-

 Events6 months ago
The Anti-Cancer Body with Dr. Michael Karlfeldt
-

 Home Remedies6 months ago
Natural Home Remedies for Restless Legs at Night
-

 Events5 months ago
The Cancer Conversation Your Oncologist Cannot Have in 15 Minutes
-

 Events7 months ago
Beyond the Brain